Related Experiment Video
Updated: Aug 19, 2026
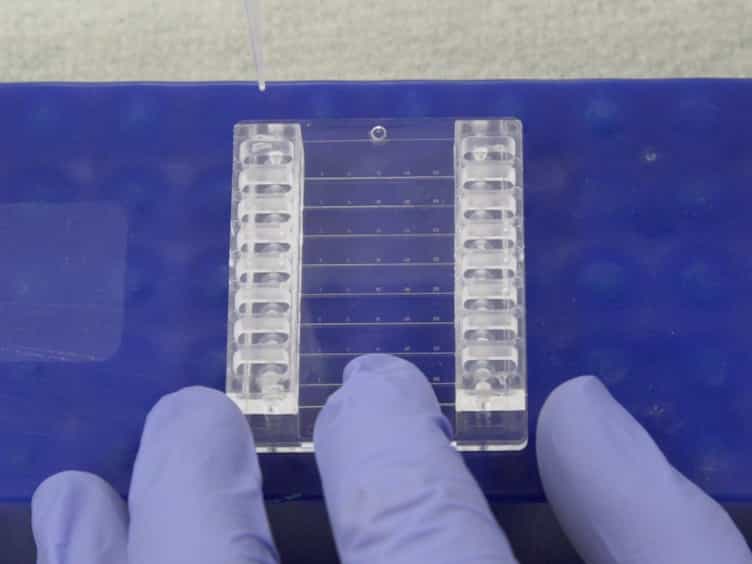
A Microfluidic Flow Chamber Model for Platelet Transfusion and Hemostasis Measures Platelet Deposition and Fibrin Formation in Real-time
Published on: February 14, 2017
Systemic and transcardiac platelet activity in acute myocardial infarction in man: resistance to prostacyclin

There is increasing evidence that platelets play an important role in the pathogenesis of acute ischemic heart disease. Therefore an understanding of factors that influence platelet performance is important. This study was undertaken (1) to characterize during evolving myocardial infarction platelet activity in the peripheral circulation and across the ischemic/infarcting myocardial compartment, the locus of presumed platelet hyperactivity, and (2) to evaluate the effects of prostacyclin (PGI2), a most potent antiplatelet agent and vasodilator. A total of 59 patients with evolving myocardial infarction were studied. Twenty-two patients were instrumented with arterial and coronary sinus catheters and received intravenous infusion of PGI2, 13 +/- 4.5 ng/kg/min (mean +/- SD), for 90 min. In 15 patients with anterior myocardial infarction, transcardiac platelet function and response to PGI2 were studied. Plasma levels of beta-thromboglobulin (beta-TG) and of thromboxane B2 (TxB2), in vivo measures of platelet activity, were elevated three- and 10-fold. 6-Keto-prostaglandin F 1 alpha, the stable end product of PGI2, was less than 10 pg/ml, reflecting a leftward shift of the TxB2/PGI2 ratio. Platelets circulating during evolving myocardial infarction ("ischemic platelets") were hyperaggregable in response to ADP and relatively resistant to PGI2, both in vivo and in vitro. Concentrations of platelet cyclic AMP and the cyclic AMP response to PGI2 were diminished. The platelet hyperreactivity, expressed by plasma beta-TG, platelet aggregation, and PGI2-induced inhibition of aggregation, was most intense early during infarct evolution and decreased with time. The increased platelet performance resulted in "platelet fatigue," indicated by decreased contents of beta-TG of the ischemic platelet and decreased TxA2 production in response to collagen. However, the ischemic platelet produced twice normal TxA2 in response to arachidonic acid (stimulus and substrate), demonstrating a heightened metabolic capacity. TxA2 was produced across the ischemic/infarcting compartment in 10 of 15 patients with anterior myocardial infarction. The antiplatelet effect of PGI2 was greatly diminished. In summary, the data define an abnormal pattern of platelet behavior during evolving myocardial infarction, characterized by a proaggregatory environment, heightened platelet reactivity in both the peripheral and coronary circulation, and relative resistance to PGI2. The clinical consequences of the data are that the patient in the acute phase of myocardial infarction may benefit from suppression of platelet function and requires significantly greater doses of PGI2 than normal subjects.(ABSTRACT TRUNCATED AT 400 WORDS)
There is increasing evidence that platelets play an important role in the pathogenesis of acute ischemic heart disease. Therefore an understanding of factors that influence platelet performance is important. This study was undertaken (1) to characterize during evolving myocardial infarction platelet activity in the peripheral circulation and across the ischemic/infarcting myocardial compartment, the locus of presumed platelet hyperactivity, and (2) to evaluate the effects of prostacyclin (PGI2), a most potent antiplatelet agent and vasodilator. A total of 59 patients with evolving myocardial infarction were studied. Twenty-two patients were instrumented with arterial and coronary sinus catheters and received intravenous infusion of PGI2, 13 +/- 4.5 ng/kg/min (mean +/- SD), for 90 min. In 15 patients with anterior myocardial infarction, transcardiac platelet function and response to PGI2 were studied. Plasma levels of beta-thromboglobulin (beta-TG) and of thromboxane B2 (TxB2), in vivo measures of platelet activity, were elevated three- and 10-fold. 6-Keto-prostaglandin F 1 alpha, the stable end product of PGI2, was less than 10 pg/ml, reflecting a leftward shift of the TxB2/PGI2 ratio. Platelets circulating during evolving myocardial infarction ("ischemic platelets") were hyperaggregable in response to ADP and relatively resistant to PGI2, both in vivo and in vitro. Concentrations of platelet cyclic AMP and the cyclic AMP response to PGI2 were diminished. The platelet hyperreactivity, expressed by plasma beta-TG, platelet aggregation, and PGI2-induced inhibition of aggregation, was most intense early during infarct evolution and decreased with time. The increased platelet performance resulted in "platelet fatigue," indicated by decreased contents of beta-TG of the ischemic platelet and decreased TxA2 production in response to collagen. However, the ischemic platelet produced twice normal TxA2 in response to arachidonic acid (stimulus and substrate), demonstrating a heightened metabolic capacity. TxA2 was produced across the ischemic/infarcting compartment in 10 of 15 patients with anterior myocardial infarction. The antiplatelet effect of PGI2 was greatly diminished. In summary, the data define an abnormal pattern of platelet behavior during evolving myocardial infarction, characterized by a proaggregatory environment, heightened platelet reactivity in both the peripheral and coronary circulation, and relative resistance to PGI2. The clinical consequences of the data are that the patient in the acute phase of myocardial infarction may benefit from suppression of platelet function and requires significantly greater doses of PGI2 than normal subjects.(ABSTRACT TRUNCATED AT 400 WORDS)


Related Concept Videos
 01:22
Formation of the Platelet Plug
As the injured blood vessel contracts, endothelial cells undergo contraction, revealing collagen fibers in the basement membrane and underlying connective tissue. Furthermore, the plasma membrane of endothelial cells becomes adhesive, preparing the site for platelet adhesion. Platelets...
 01:16
Clot Retraction and Fibrinolysis
 01:23
Treatment for Pulmonary Arterial Hypertension: Prostacyclin Receptor Agonists
These agonists bind to the IPR receptor situated on the plasma membrane of the pulmonary artery smooth muscle cells. This binding triggers a cascade of reactions known as the GS-AC-cAMP-PKA pathway. This pathway results in the relaxation of smooth muscle...
 01:26
Coronary Artery Disease II: Pathophysiology
 01:30
Acute Coronary Syndrome I: Introduction