Related Experiment Video
Updated: Feb 15, 2026


Modeling Spontaneous Metastatic Renal Cell Carcinoma mRCC in Mice Following Nephrectomy
Published on: April 29, 2014
Overview of Current and Future First-Line Systemic Therapy for Metastatic Clear Cell Renal Cell Carcinoma
David M Gill1,2, Andrew W Hahn3, Peter Hale3
1Department of Oncology, Huntsman Cancer Institute, Salt Lake City, UT, USA.

Opinion Statement:
Treatment of metastatic clear cell renal cancer (mccRCC) has seen substantial progress over the last 20 years, with many regulatory approvals since 2006 culminating in a substantial increase to overall survival (OS). Six therapies are currently available for first-line use, with additional treatments currently being tested in this setting, some of which are expected to be approved soon based on new data from the CABOSUN and CheckMate-214 trials. Based on the available evidence, we strongly believe that vascular endothelial growth factor tyrosine kinase inhibitor (VEGF-TKI) therapy over mechanistic target or rapamycin (mTOR; formerly known as mammalian target of rapamycin) inhibitor therapy is the most effective first-line option regardless of risk category assignment. High-dose interleukin-2 (HDIL-2) therapy remains a reasonable treatment option in patients with Eastern Cooperative Oncology Group (ECOG) performance status 0-1 and have minimal comorbid conditions. In the near future, these agents are likely to be surpassed by cabozantinib and by combination immune checkpoint inhibitor therapy with nivolumab and ipilimumab. Independent review has recently confirmed superiority of first-line cabozantinib over sunitinib in a phase 2 trial of 157 patients with intermediate or poor risk mccRCC (progression-free survival [PFS] 8.6 vs 5.3 months, hazard ratio [HR] 0.48, p = 0.0008). In a separate study of 1096 patients treated with either upfront sunitinib or the combination of nivolumab and ipilimumab, those with intermediate and poor risk had significant improvement in both PFS (11.6 vs 8.4 months, HR 0.82, p = 0.0331) and OS (not reached vs 26 months, p < 0.0001). Responses were greater in patients with positive programmed death receptor ligand-1 (PD-L1) tumor staining, and pending regulatory approval may become standard of care in untreated patients with intermediate to poor risk disease with positive PD-L1 status. This likely represents the beginning of additional novel immunotherapy combinations for the first-line treatment of mccRCC.
More Related Videos
 05:36
Comparing Metastatic Clear Cell Renal Cell Carcinoma Model Established in Mouse Kidney and on Chicken Chorioallantoic Membrane
Published on: February 8, 2020
 06:38
A Syngeneic Mouse Model of Metastatic Renal Cell Carcinoma for Quantitative and Longitudinal Assessment of Preclinical Therapies
Published on: April 12, 2017
Related Concept Videos
 01:30
Continuous Renal Replacement Therapy
 01:27
Controlled-Current Coulometry: Overview
 01:11
Overview of Systemic Arteries
Systemic circulation is the part of the cardiovascular system that carries oxygenated blood away from the heart to the body's tissues and returns deoxygenated blood back to the...
 01:11
Overview of Systemic Veins
The coronary sinus, the heart's principal vein, resides in the coronary sulcus on the heart's posterior aspect. This broad venous channel receives nearly all venous blood from the myocardium, the heart muscle. It is fed by three primary veins: the great cardiac vein, the...
 01:15
Renal Drug Excretion: Overview
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...
 01:06
Renal Drug Clearance: Overview
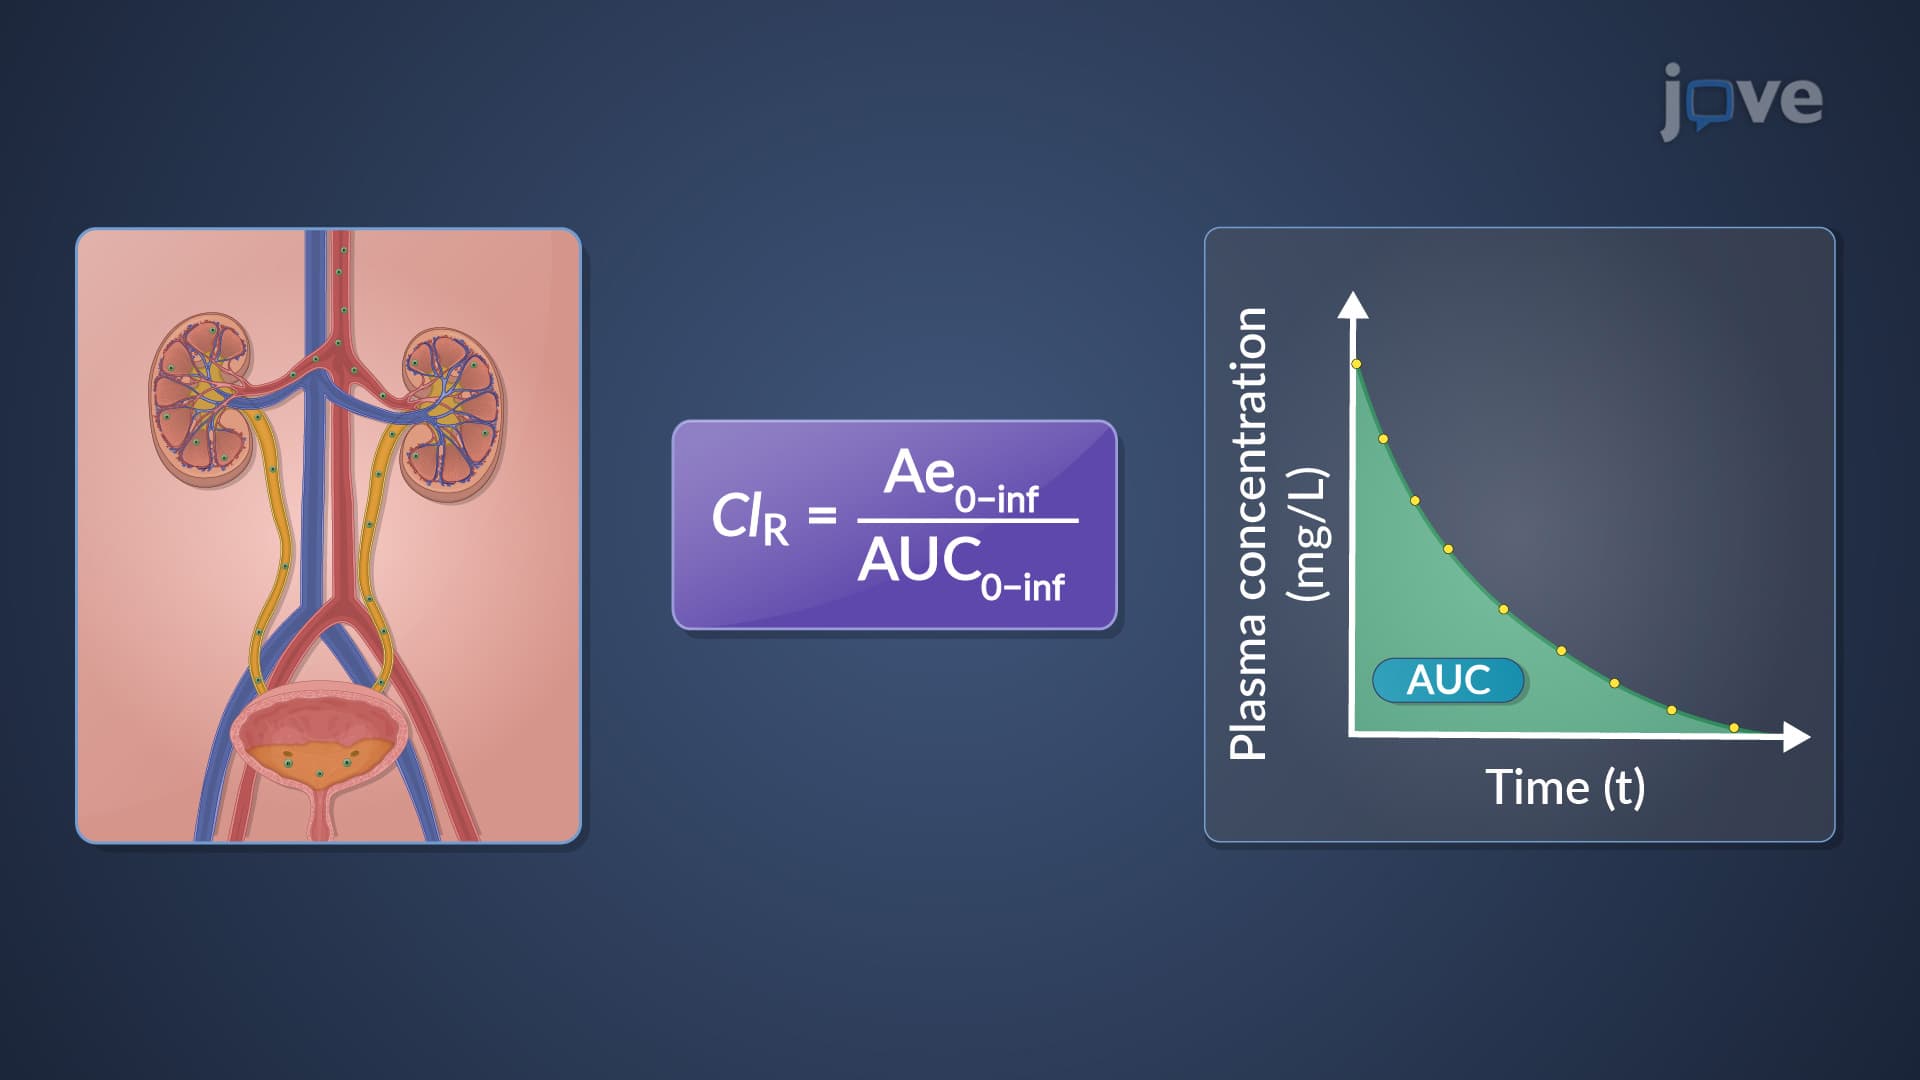
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...