Related Experiment Video
Updated: Feb 15, 2026


Measuring and Mapping Patterns of Soil Erosion and Deposition Related to Soil Carbonate Concentrations Under Agricultural Management
Published on: September 12, 2017
How Is Rectal Cancer Managed: a Survey Exploring Current Practice Patterns in Canada
A Crawford1,2, J Firtell3, A Caycedo-Marulanda4,5,6
1Northern Ontario School of Medicine, Sudbury, ON, Canada.

Introduction:
Locally advanced rectal cancers are most often treated with neoadjuvant chemoradiation followed by surgical resection. However, there are differing opinions surrounding management of rectal cancer, including a lack of consensus on the optimal time interval between chemoradiation and surgery, and the management of patients with complete clinical response following neoadjuvant therapy. This study seeks to summarize management trends for rectal cancer among a sample of Canadian surgeons.
Methods:
A 14-question survey was distributed to surgeons across Canada managing rectal cancer. Surgeons were identified from the membership lists of the Canadian Association of General Surgeons and the Canadian Society of Colon and Rectal Surgeons. Web-based questionnaires were distributed by email.
Results:
A total of 115 surgeons were emailed the survey with a response rate of 38.4%. Approximately 50% of surgeon responders had been in practice for more than 10 years, with the majority practicing in academic centers. Half were considered high-volume rectal cancer surgeons with more than 20 cases per year. All surgeons used magnetic resonance imaging for staging of rectal cancer, but only 50% presented all rectal cancer cases at multidisciplinary cancer conferences. The majority of surgeons applied minimally invasive techniques for surgical resection, including the utilization of transanal endoscopic microsurgery (TEMs) and transanal minimally invasive surgery (TAMIS); however, only a small fraction performed high-volume transanal total mesorectal excision (taTME). Regarding the management of complete clinical response (cCR) following neoadjuvant chemoradiation, less than 5% chose the watch and wait management strategy for all patients and 40% did not use it at all. The majority of surgeons reported waiting between eight and 10 weeks between chemoradiation and surgery, and 40% made that decision regardless of patient or tumor factors.
Conclusion:
The majority of surveyed surgeons use MRI for pelvic staging and discuss rectal cancer cases at multidisciplinary cancer conference. Many are using minimally invasive techniques; however, the use of taTME is not yet widespread. Surgeons currently favor longer intervals from neoadjuvant chemoradiation to surgery, and the management strategy for patients with complete clinical response remains controversial. Great variability exists in rectal cancer management, thus presenting an opportunity for improvements by adopting standardization and centralization of rectal cancer management.
More Related Videos
 07:43
Methods for Image-based Surveys of Benthic Macroinvertebrates and Their Habitat Exemplified by the Drop Camera Survey for the Atlantic Sea Scallop
Published on: July 2, 2018
 10:35
Best Current Practice for Obtaining High Quality EEG Data During Simultaneous fMRI
Published on: June 3, 2013
Related Concept Videos
 02:16
Surveys
 01:27
Introduction to Surveying, Plane Surveying and Geodetic Surveys
 01:27
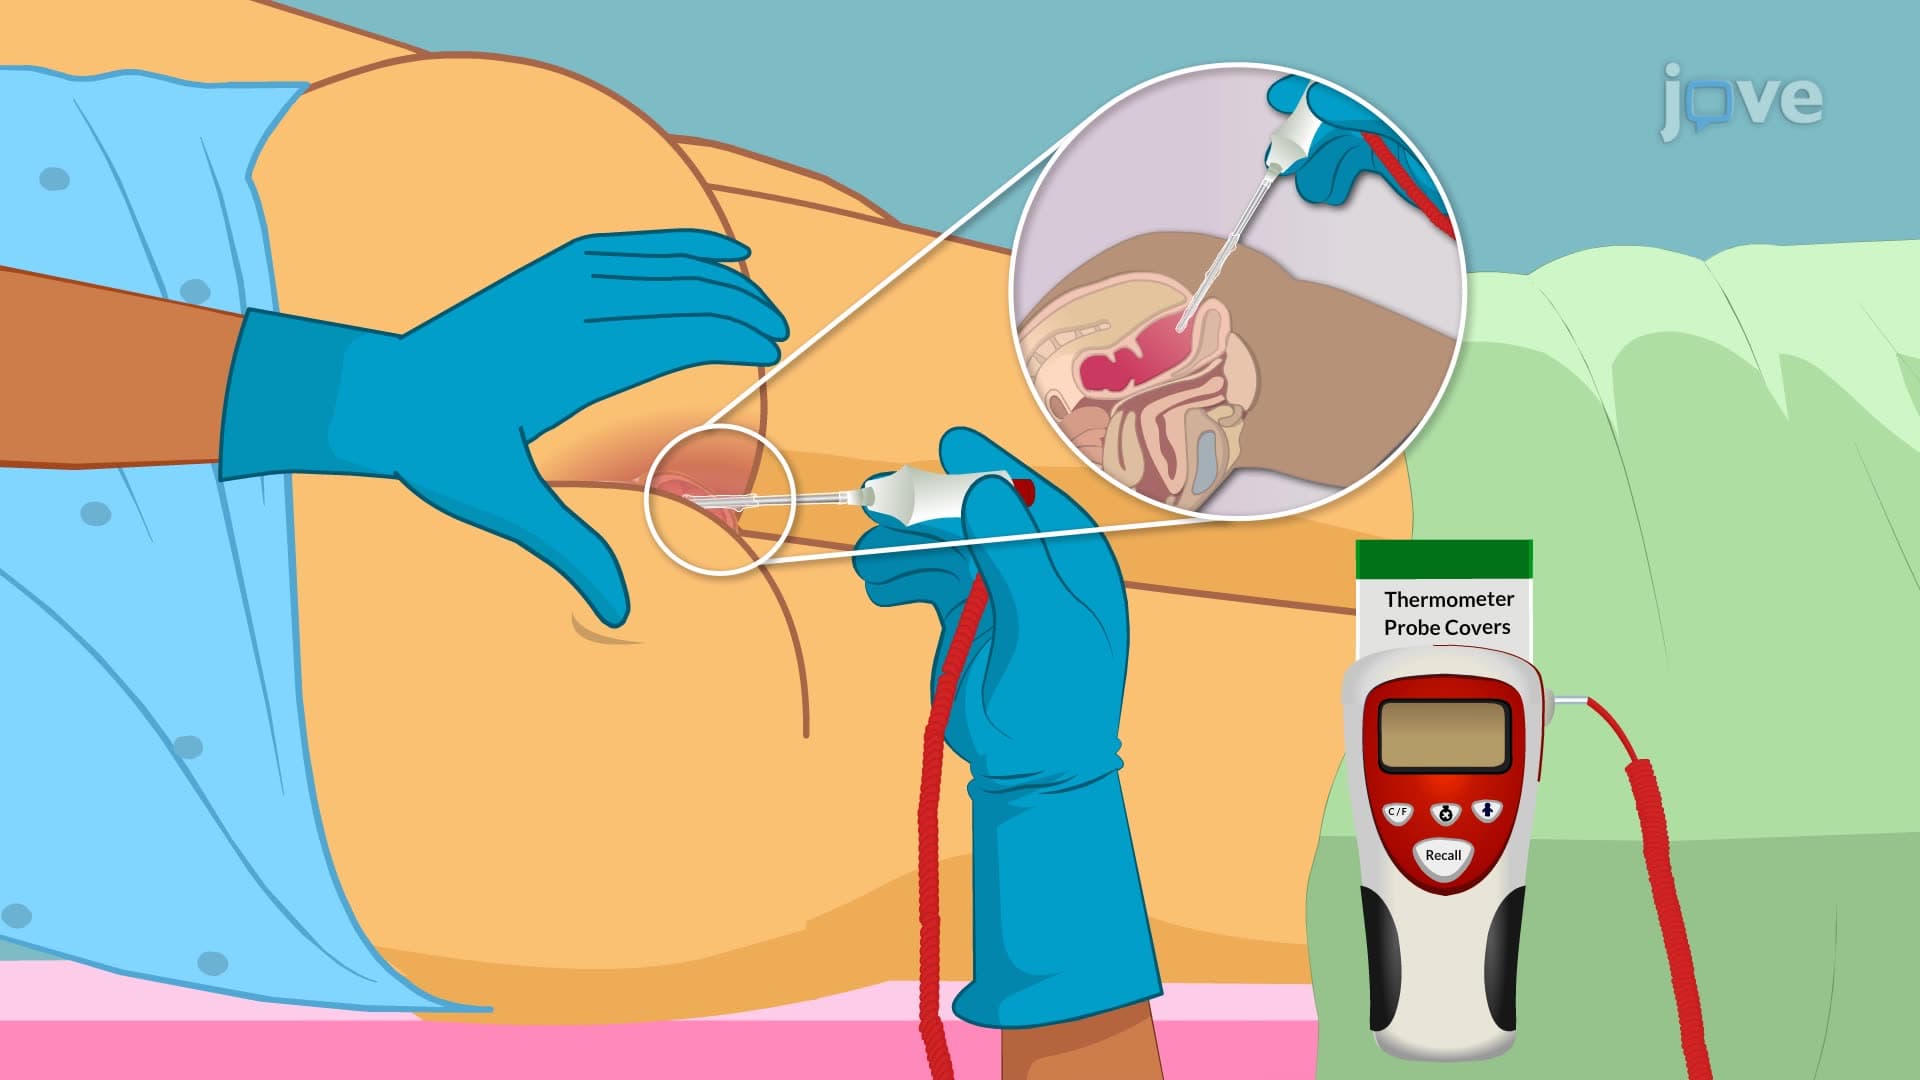
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 01:19
Errors and Mistakes in Surveying
 01:27
Types of Surveys
 01:28
Survey Safety