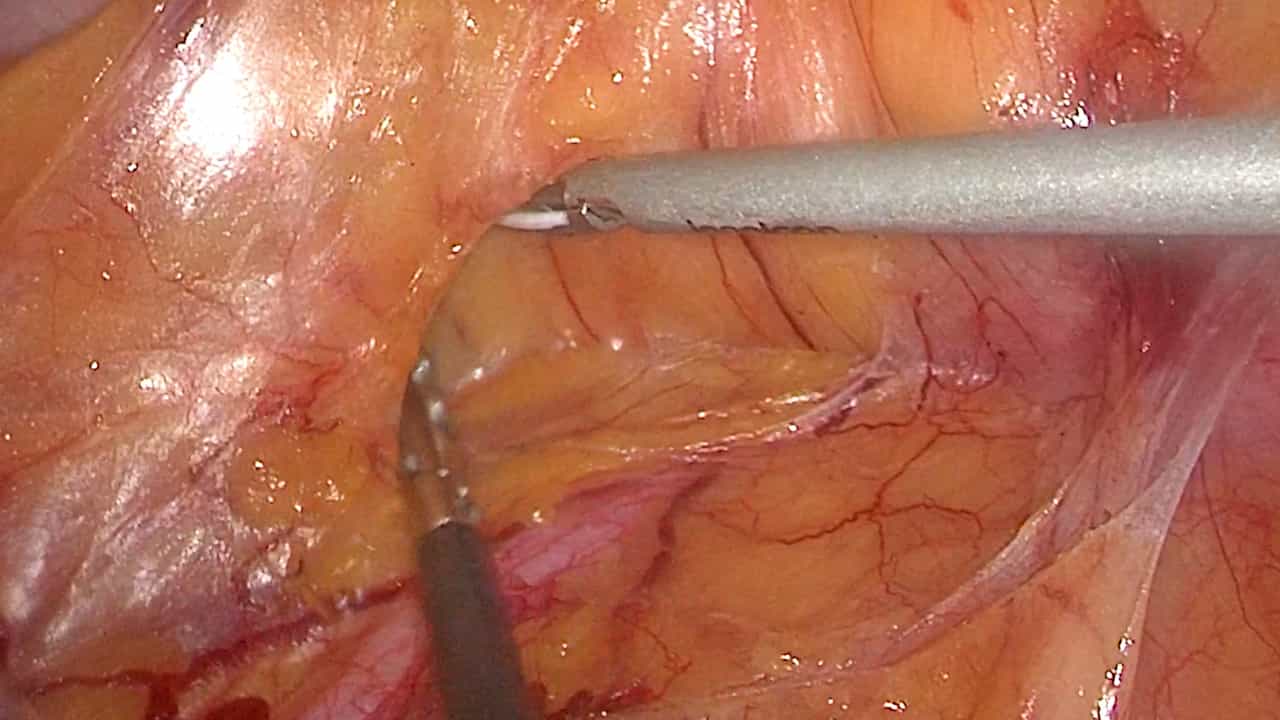
Related Experiment Video
Updated: Sep 9, 2026


Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Evidence Gap in Managing Lateral Pelvic Lymph Nodes in Rectal Cancer: a Systematic Review of Radiation Boost
Sedat Alp Pinar1, Tin-Ning Wong2, Timothy Mitchell3
1Academic Unit of Surgery, Glasgow Royal Infirmary and University of Glasgow, 8-16 Alexandra Parade, Glasgow, G31 2ER, United Kingdom. sedatalp.pinar@nhs.scot.

Purpose:
Lateral pelvic lymph node (LPLN) involvement is a significant predictor of local recurrence in patients with locally advanced rectal cancer (LARC). While lateral pelvic lymph node dissection (LPLND) is routinely used in some countries to manage suspicious nodes, it is associated with increased morbidity and is not widely adopted in Western practice. Radiation boost (dose escalation) to involved LPLNs during neoadjuvant chemoradiotherapy (nCRT) has emerged as a potential non-surgical alternative. Despite increasing adoption of radiation boost to clinically involved LPLNs, there remains limited evidence defining its safety, oncologic benefit, and role relative to LPLND.
Methods:
A systematic search of MEDLINE, EMBASE, ClinicalTrials.gov, and Cochrane databases was conducted following PRISMA guidelines. Studies were included if they reported outcomes of radiation dose escalation specifically targeting radiologically suspicious LPLNs in the context of nCRT.
Results:
Ten retrospective cohort studies encompassing 482 radiation boosted patients were included. Boost doses ranged from 35.0 to 60.2 Gy. Rates of Grade 2-3 toxicity ranged from 28.0% to 39.3% across individual studies, with only one study reporting a single Grade 4 adverse event. Across individual studies, reported nodal response rates ranged from 62.3% to 100%. Comparative studies suggest that radiation boost may improve local control and reduce LPLN recurrence.
Conclusion:
Current retrospective evidence suggests that radiation dose escalation to involved LPLNs is a promising treatment strategy; however, the available data are limited by retrospective study designs and substantial clinical heterogeneity. Given the absence of prospective evidence and lack of consensus in current guidelines, an important evidence gap remains. Well-designed prospective trials are warranted to define the role of LPLN boost relative to LPLND.