Related Experiment Video
Updated: Feb 15, 2026


Postconditioning with Lactate-enriched Blood for Cardioprotection in ST-segment Elevation Myocardial Infarction
Published on: May 28, 2019
Early myocardial surgical revascularization after ST-segment elevation myocardial infarction in multivessel coronary
Maria V Polito1, Stefania Asparago1, Gennaro Galasso1
1Department of Medicine and Surgery, University of Salerno.

Insights
This study on ST-segment elevation myocardial infarction (STEMI) patients with multivessel disease found that early staged coronary artery bypass grafting (CABG) after percutaneous coronary intervention (PCI) is safe and effective when patients are carefully selected. No adverse events were observed during follow-up.
Area of Science:
- Cardiology
- Cardiovascular Surgery
Background:
- Many ST-segment elevation myocardial infarction (STEMI) patients present with multivessel disease, requiring initial percutaneous coronary intervention (PCI) of the culprit lesion followed by potential coronary artery bypass grafting (CABG) of nonculprit vessels.
- Optimal strategies, timing, and antiplatelet therapy management for staged revascularization in STEMI patients with multivessel disease remain controversial.
Purpose of the Study:
- To evaluate the safety and outcomes of early staged CABG in STEMI patients with multivessel disease who initially underwent PCI of the culprit vessel only.
- To assess the feasibility of performing CABG using a bridge therapy strategy after STEMI and PCI.
Main Methods:
- A retrospective registry analysis of 21 STEMI patients with multivessel disease who underwent PCI of the culprit vessel followed by CABG.
- Data collected included demographics, clinical characteristics, echocardiography, angiography, preoperative scores, surgical details, and postoperative complications.
- Follow-up for death, reinfarction, and cardiovascular/noncardiovascular events was recorded at a mean of 21.6 months.
Main Results:
- Patients were 62 ± 9 years old with good ejection fraction; the culprit lesion was most commonly the right coronary artery (76%).
- High SYNTAX scores (31.6 ± 7.4) and low logistic EuroSCORE II (1.46 ± 1.01) indicated suitability for CABG.
- Off-pump CABG was performed 7.2 ± 3.2 days after PCI using intravenous tirofiban as bridge therapy, with no reported deaths, reinfarctions, or other adverse events during follow-up.
Conclusions:
- Careful preoperative patient selection is crucial for successful postoperative outcomes and long-term survival in STEMI patients undergoing staged revascularization.
- Early-staged CABG, even after STEMI and initial PCI, can be safely performed utilizing a bridge therapy approach.
Background:
Many ST-segment elevation myocardial infarction (STEMI) patients have a multivessel disease that initially require percutaneous coronary intervention (PCI) of the culprit vessel but subsequently may require coronary artery bypass graft (CABG) of nonculprit vessels. Evidence supports staged revascularization, but the identification of optimal strategies (percutaneous or surgical), the timing and the management of antiplatelet therapy after recent PCI with stenting are matters of great controversies.
Methods:
In our retrospective registry, we have enrolled 21 patients presenting with STEMI and multivessel disease, who underwent PCI of the culprit vessel only and then CABG of nonculprit vessels. Demographic, clinical, echocardiographic, angiographic findings, preoperative score, surgical data and postoperative complications were collected. At 21.6 ± 15.6 months follow-up death, reinfarction and/or cardiovascular and noncardiovascular events were recorded.
Results:
Patients were 62 ± 9 years old and had in the most cases a good ejection fraction. At angiography, the culprit lesion was right coronary artery in 16 patients (76%). Angiographic characteristics excluded a staged PCI (SYNTAX score = 31.6 ± 7.4) and European System for Cardiac Operative Risk Evaluation II resulted low (1.46 ± 1.01). Following the indication to cardiac surgery after Heart Team discussion, the withdrawal of oral P2Y12 inhibitor was planned and tirofiban intravenous was started. Off-pump CABG was performed after 7.2 ± 3.2 days. No death, reinfarction and/or cardiovascular and noncardiovascular events occurred at follow-up.
Conclusion:
We can conclude that a careful preoperative selection is mandatory for a good postoperative course and long-term survival and that early-staged CABG can, however, be performed using bridge therapy, also after STEMI.


Related Concept Videos
 01:30
Coronary Artery Disease I: Introduction
 01:26
Coronary Artery Disease II: Pathophysiology
 01:27
Coronary Artery Disease V: Interprofessional Care
 03:12
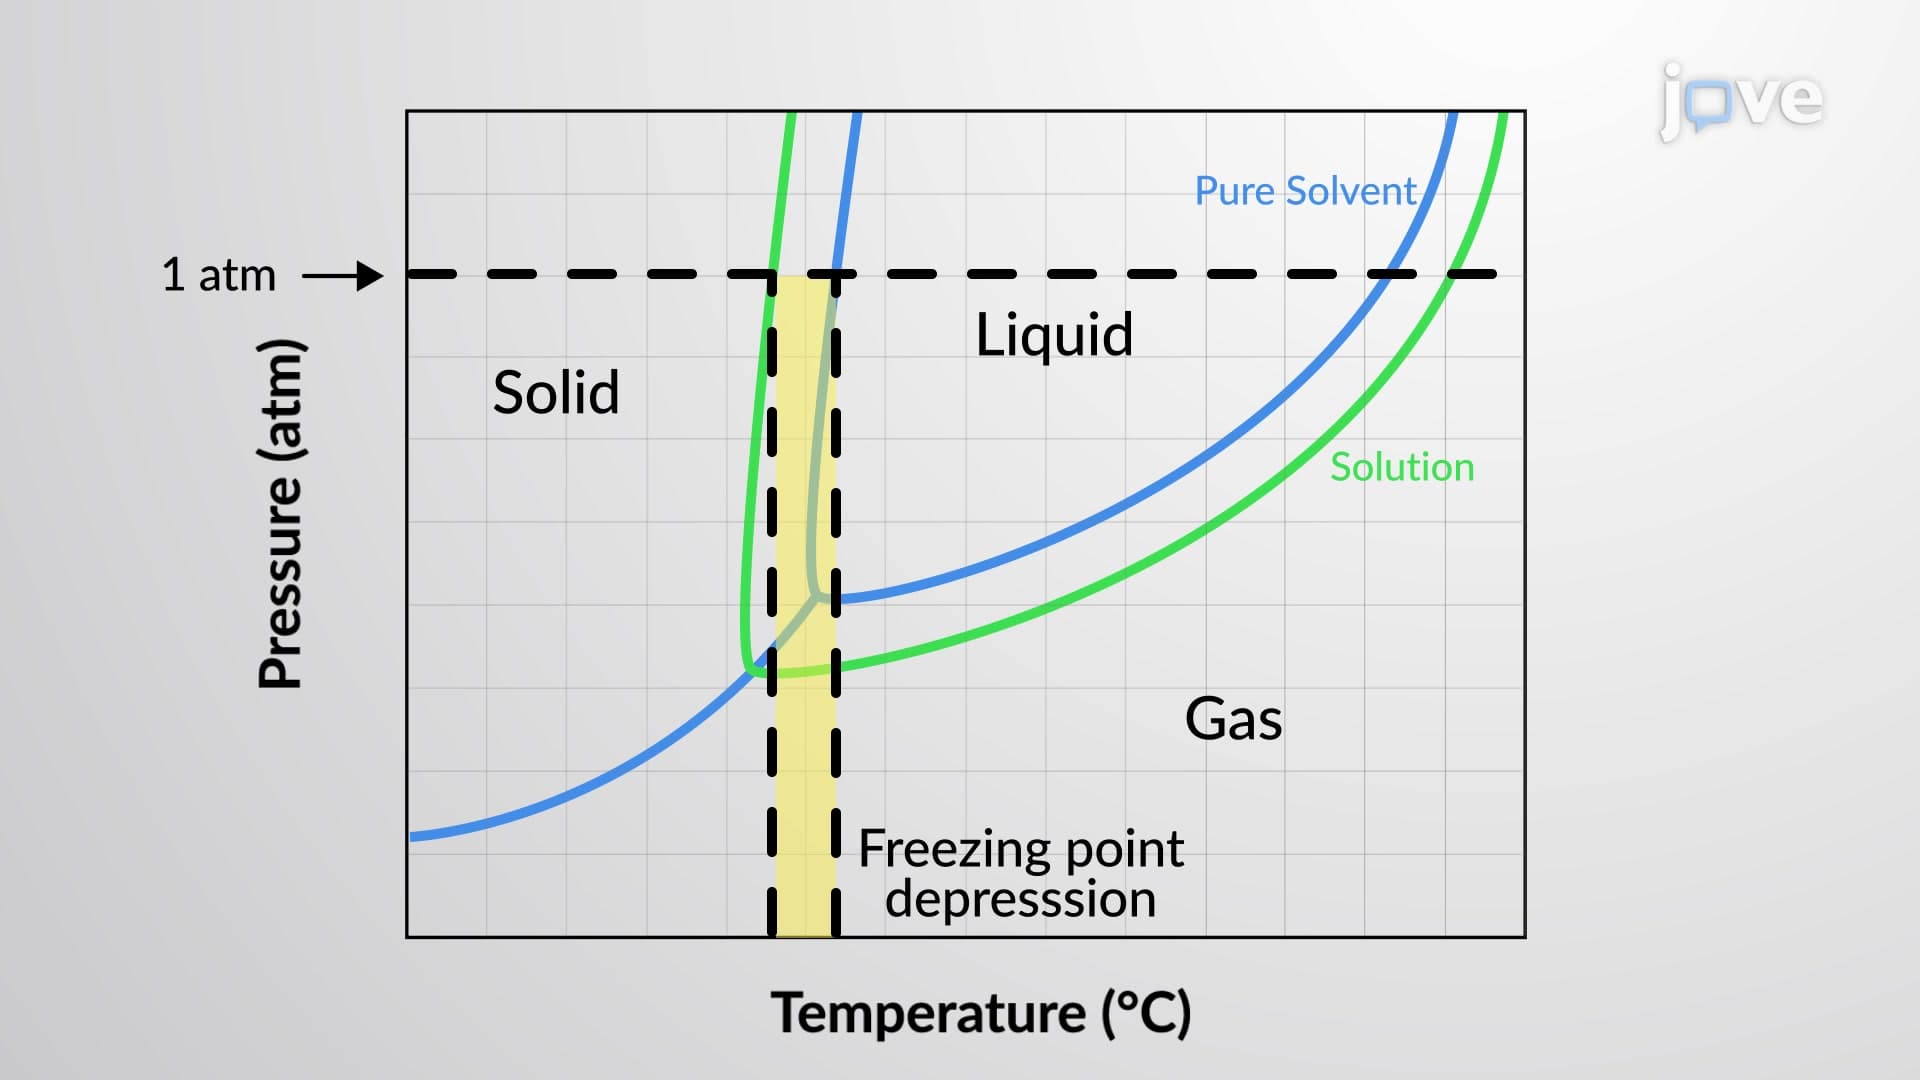
Freezing Point Depression and Boiling Point Elevation
The boiling point of a liquid is the temperature at which its vapor pressure is equal to ambient atmospheric pressure. Since the vapor pressure of a solution is lowered due to the presence of nonvolatile solutes, it stands to reason that the solution’s boiling point will subsequently be increased. Vapor pressure increases with temperature, and so a solution will require a higher temperature than will pure solvent to achieve any given vapor pressure, including one...
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:26
Coronary Artery Disease IV: Preventive Measures