Related Experiment Video
Updated: Feb 14, 2026


Postconditioning with Lactate-enriched Blood for Cardioprotection in ST-segment Elevation Myocardial Infarction
Published on: May 28, 2019
Homocysteine is a bystander for ST-segment elevation myocardial infarction: a case-control study
Ching-Yu Julius Chen1,2, Tzu-Ching Yang3, Christopher Chang4
1Cardiovascular Center and Division of Cardiology, Department of Internal Medicine, National Taiwan University Hospital, 7 Chung-Shan South Road, 100, Taipei, Taiwan.

Insights
Serum homocysteine levels are not elevated in patients with ST-segment elevation myocardial infarction (STEMI). This suggests homocysteine is not a cause of STEMI, and lowering it may not be essential for cardiovascular disease prevention.
Area of Science:
- Cardiology
- Biochemistry
- Vascular Biology
Background:
- Homocysteine is a suspected risk factor for atherosclerosis, but B vitamin supplements have not reduced cardiovascular events.
- The relationship between homocysteine and ST-segment elevation myocardial infarction (STEMI) remains unclear despite associations with other cardiovascular diseases.
Purpose of the Study:
- To investigate the association between serum homocysteine levels and STEMI.
- To examine the cellular effects of homocysteine on human coronary artery endothelial cells.
Main Methods:
- Prospective enrollment of STEMI patients and controls with patent coronary arteries.
- Measurement of serum homocysteine levels and correlation with clinical parameters (Killip classification, CRP, peak creatine kinase, SYNTAX score).
- In vitro culture system to assess homocysteine's toxicity on endothelial cells.
Main Results:
- No significant difference in serum homocysteine levels between STEMI patients and controls.
- Homocysteine levels did not correlate with STEMI severity (Killip classification) or inflammatory markers.
- Supraphysiological homocysteine concentrations did not reduce human coronary artery endothelial cell viability in vitro.
Conclusions:
- Homocysteine is not elevated in STEMI patients, indicating it is likely a bystander, not a causative factor.
- The findings support the current understanding that homocysteine-lowering strategies may not be crucial for preventing cardiovascular disease.
Background:
Homocysteine has been long considered a risk factor for atherosclerosis. However, cardiovascular events cannot be reduced through homocysteine lowering by B vitamin supplements. Although several association studies have reported an elevation of serum homocysteine levels in cardiovascular diseases, the relationship of homocysteine with ST-segment elevation myocardial infarction (STEMI) is not well established.
Methods:
We prospectively enrolled STEMI patients who were consecutively admitted to an intensive care unit following coronary intervention in a single medical center in Taiwan. Control subjects were individuals who presented to the outpatient or emergency department with acute chest pain but subsequently revealed patent coronary arteries by coronary arteriography. The association between serum homocysteine levels and STEMI was investigated. A culture system using human coronary artery endothelial cells was also established to examine the toxic effects of homocysteine at the cellular level.
Results:
Patients with chest pain were divided into two groups. The STEMI group included 56 patients who underwent a primary percutaneous coronary intervention. The control group included 17 subjects with patent coronary arteries. There was no difference in serum homocysteine levels (8.4 ± 2.2 vs. 7.6 ± 1.9 μmol/L, p = 0.142). When stratifying STEMI patients by the Killip classification into higher (Killip III-IV) and lower (Killip I-II) grades, CRP (3.3 ± 4.1 vs. 1.4 ± 2.3 mg/L, p = 0.032), peak creatine kinase (3796 ± 2163 vs. 2305 ± 1822 IU/L, p = 0.023), and SYNTAX scores (20.4 ± 11.1 vs. 14.8 ± 7.6, p = 0.033) were significantly higher in the higher grades, while serum homocysteine levels were similar. Homocysteine was not correlated with WBCs, CRP, or the SYNTAX score in STEMI patients. In a culture system, homocysteine at even a supraphysiological level of 100 μmol/L did not reduce the cell viability of human coronary artery endothelial cells.
Conclusions:
Homocysteine was not elevated in STEMI patients regardless of Killip severity, suggesting that homocysteine is a bystander instead of a causative factor of STEMI. Our study therefore supports the current notion that homocysteine-lowering strategies are not essential in preventing cardiovascular disease.

Related Concept Videos
 02:09
Bystander Effect
 03:12
Freezing Point Depression and Boiling Point Elevation
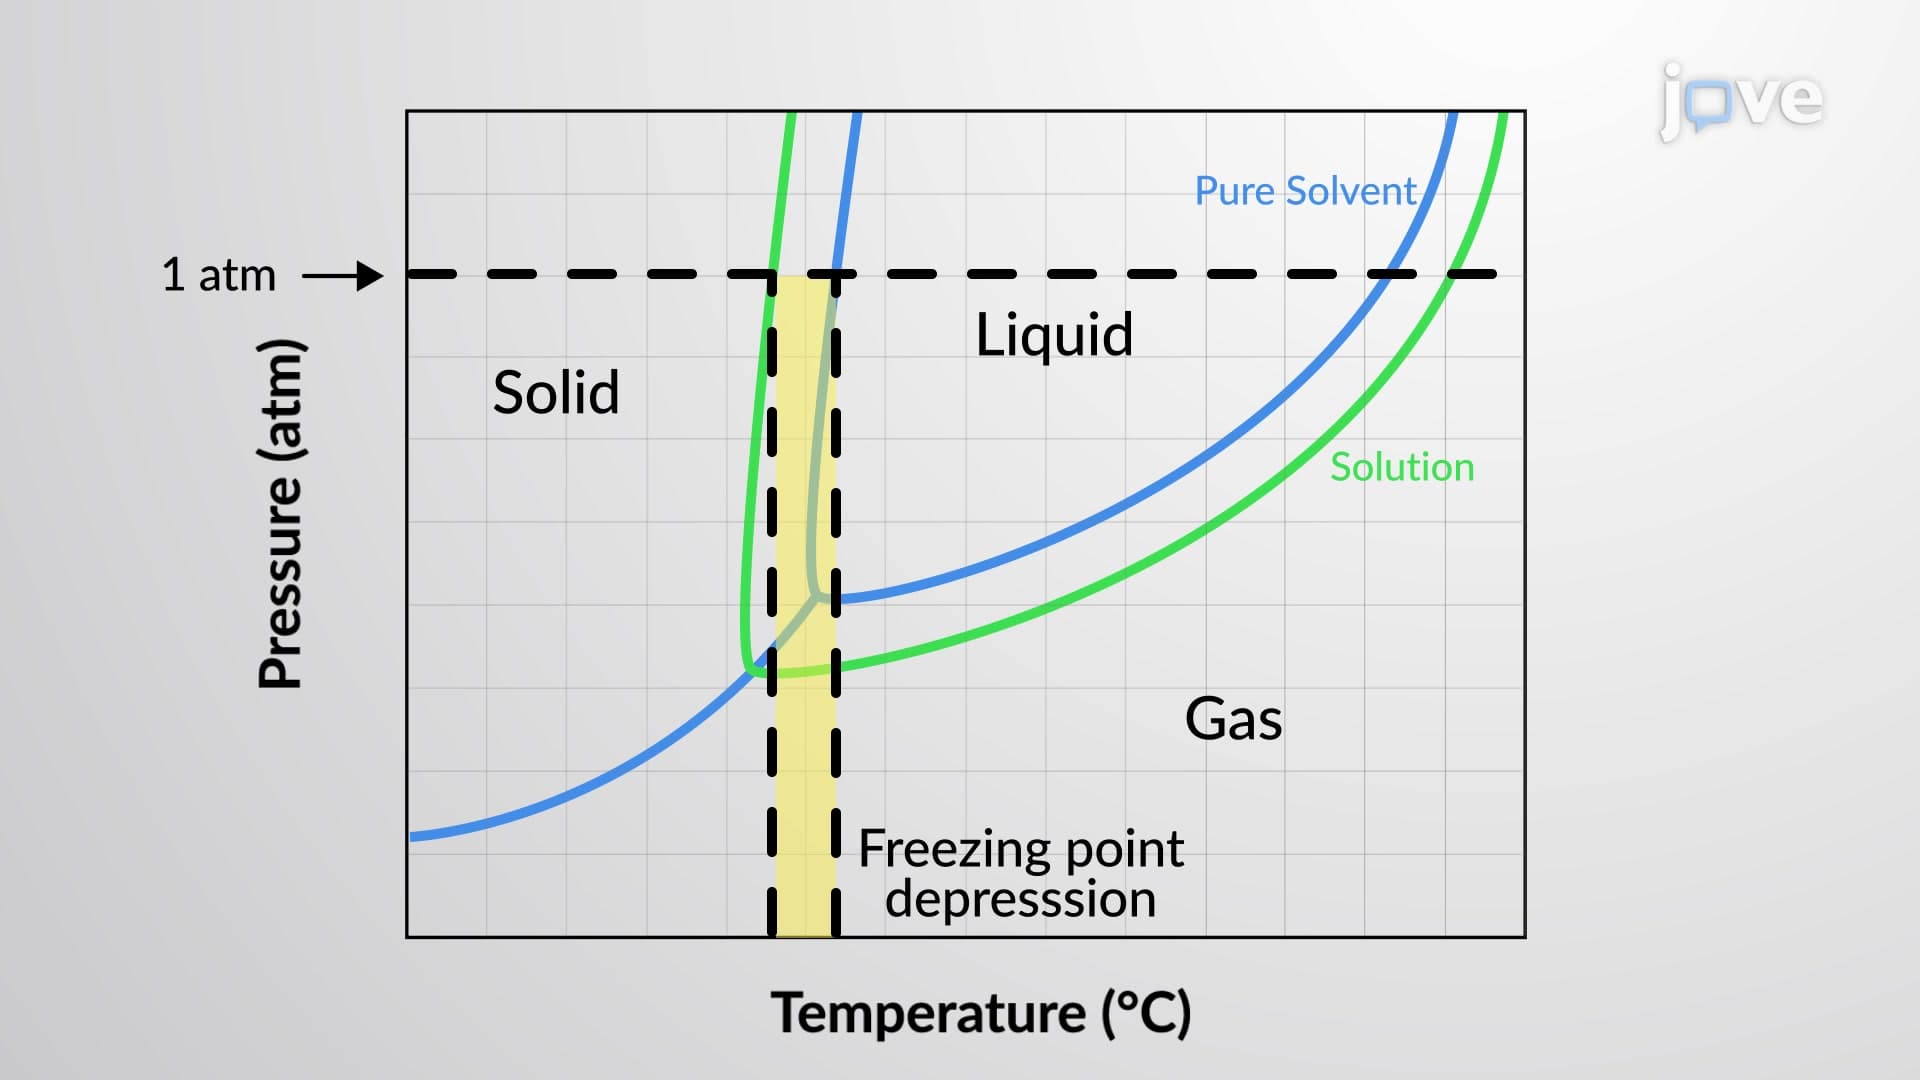
The boiling point of a liquid is the temperature at which its vapor pressure is equal to ambient atmospheric pressure. Since the vapor pressure of a solution is lowered due to the presence of nonvolatile solutes, it stands to reason that the solution’s boiling point will subsequently be increased. Vapor pressure increases with temperature, and so a solution will require a higher temperature than will pure solvent to achieve any given vapor pressure, including one...
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast,...
 01:20
Elevation of Intermediate Points on Vertical Curves
 01:21
Control System Problem
When forming a closed-loop system, issues can arise if the poles cross into the unstable region, leading to potential...
 02:33
Combinatorial Gene Control
The expression of more than 30,000 genes is controlled by approximately 2000-3000 transcription factors. This is possible because a single transcription factor can recognize more than one regulatory sequence. The specificity in gene...