Related Experiment Video
Updated: Feb 14, 2026
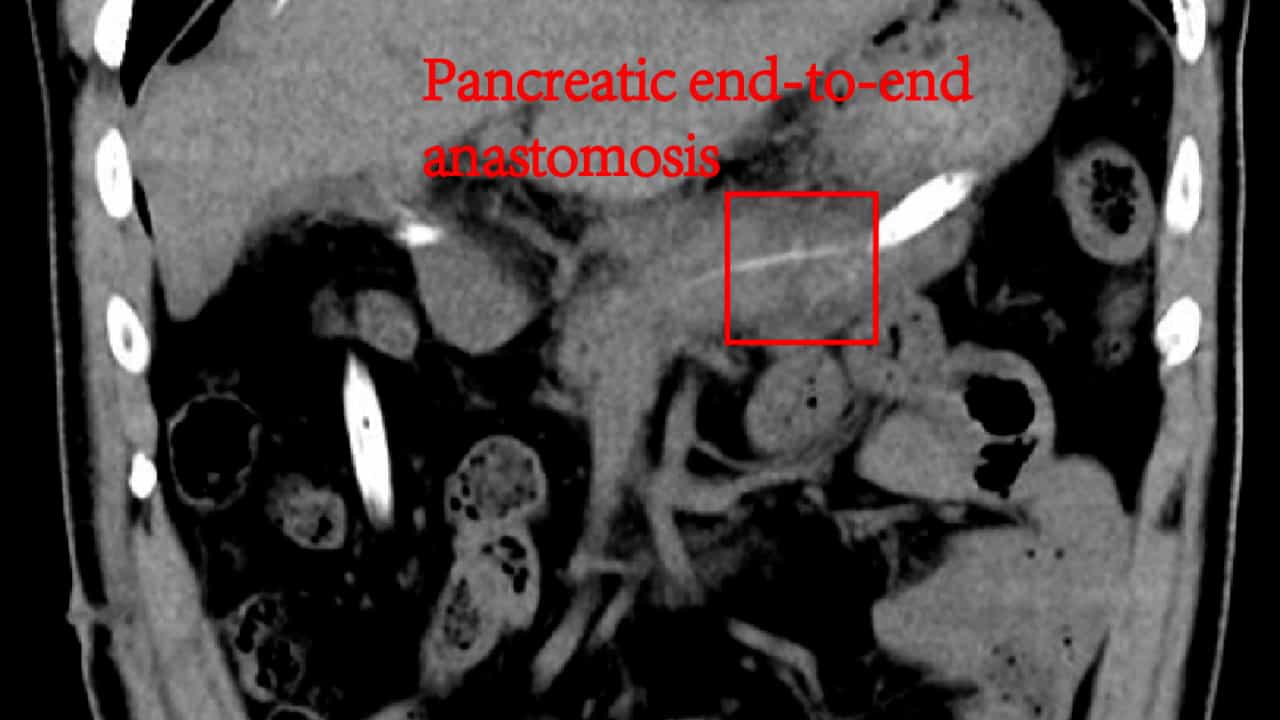

Application of Mid-Pancreatectomy with End-to-End Anastomosis in Pancreatic Benign Tumors
Published on: February 9, 2024
Do Drains Contribute to Pancreatic Fistulae? Analysis of over 5000 Pancreatectomy Patients
R El Khoury1,2, C Kabir2, V K Maker1,2
1Department of Surgery, Division of Surgical Oncology, University of Illinois at Chicago, 835 S. Wolcott St. MC790, Chicago, IL, USA.

Introduction:
Conflicting evidence exists from randomized controlled trials supporting both increased complications/fistulae and improved outcomes with drain placement after pancreatectomy. The objective was to determine drain practice patterns in the USA, and to identify if drain placement was associated with fistula formation.
Methods:
Demographic, perioperative, and patient outcome data were captured from the most recent annual NSQIP pancreatic demonstration project database, including components of the fistula risk score. Significant variables in univariate analysis were entered into adjusted logistic regression models.
Results:
Of 5013 pancreatectomy patients, 4343 (87%) underwent drain placement and 18% of patients experienced a pancreatic fistula. When controlled for other factors, drain placement was associated with ducts < 3 mm, soft glands, and blood transfusion within 72 h of surgery. Age, obesity, neoadjuvant radiation, preoperative INR level, and malignant histology lost significance in the adjusted model. Drained patients experienced higher readmission rates (17 vs. 14%; p < 0.05) and increased (20 vs. 8%; p < 0.01) pancreatic fistulae. Fistula was associated with obesity, no neoadjuvant chemotherapy, drain placement, < 3 mm duct diameter, soft gland, and longer operative times. Drain placement remained independently associated with fistula after both distal pancreatectomy (OR = 2.84 (1.70, 4.75); p < 0.01) and pancreatoduodenectomy (OR = 2.29 (1.28, 4.11); p < 0.01).
Conclusions:
Despite randomized controlled clinical trial data supporting no drain placement, drains are currently placed in the vast majority (87%) of pancreatectomy patients from > 100 institutions in the USA, particularly those with soft glands, small ducts, and perioperative blood transfusions. When these factors are controlled for, drain placement remains independently associated with fistulae after both distal and proximal pancreatectomy.
Related Concept Videos
 01:23
Binet's Contribution to Measures of Intelligence
 01:23
Wechsler's Contribution to Measures of Intelligence
 01:26
Pancreatic Juice and Secretion
When acidic chyme from the stomach enters the duodenum, it triggers the release of secretin, a hormone that prompts pancreatic juice secretion. After a fatty meal, cholecystokinin, another hormone, stimulates gallbladder contraction and enhances enzyme-rich...
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment: