Related Experiment Video
Updated: Feb 13, 2026
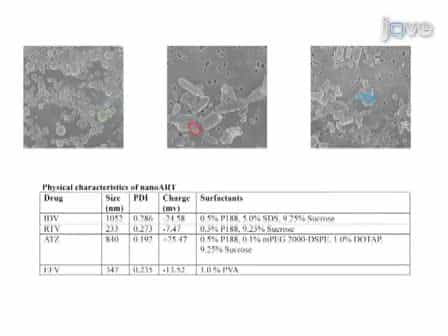

Methods Development for Blood Borne Macrophage Carriage of Nanoformulated Antiretroviral Drugs
Published on: December 9, 2010
[Nephrotoxicity of antiretrovirals other than tenofovir]
Christopher Loens1, Sabine Amet2, Corinne Isnard-Bagnis1
1Service de néphrologie, groupe hospitalier universitaire Pitié-Salpêtrière, 47-83, boulevard de l'Hôpital, 75651 Paris cedex 13, France; Université Pierre et Marie Curie, 4, place Jussieu, 75005 Paris, France.

Abstract:
The remarkable improvement of the outcome of HIV infection came with the price of substantial toxicity of some antiretrovirals. The first molecules used to treat HIV included an important nephrotoxicity. Zalcitabine, stavudine and didanosine can induce severe lactic acidosis. Lactate production is enhanced and the renal capacity to regulate pH is overwhelmed. However, this side effect is not due to a direct dysfunction of the kidneys. Zalcitabine was withdrawn from the market because of this risk. Indinavir, a protease inhibitor, is soluble only in very acidic solutions. Consequently, the small fraction that is excreted in the urine precipitates and can be responsible for uro-nephrolithiasis, leukocyturia, cristalluria, obstructive acute kidney failure, and acute or chronic interstitial nephritis. This is the reason why indinavir is almost not prescribed nowadays, even if it is still marketed. In addition to the direct nephrotoxicity of some antiretrovirals, anti-HIV treatment also includes a toxicity which pathophysiology is not completely elucidated. This nephrotoxicity is the consequence of organ accelerated ageing and of an increased vascular risk. Kidney vascularization (from renal arteries to capillaries) is essential to kidney function and all cardiovascular risks are also renal risks. It is now clearly established that combined antiretroviral treatment increases the vascular risk. A better comprehension of the links between HIV infection, its treatment and very long-term kidney risk is needed to improve the complex management of patients who have now cumulated several decades of HIV infection and treatment with various toxicities.
Insights
Certain antiretrovirals used for HIV treatment can cause significant kidney damage, including lactic acidosis and kidney stones. Understanding these risks is crucial for managing long-term patient health.
Area of Science:
- Nephrology
- Infectious Diseases
- Pharmacology
Background:
- Antiretroviral therapy has greatly improved HIV outcomes but is associated with substantial toxicities.
- Early HIV medications, such as zalcitabine, stavudine, and didanosine, were linked to nephrotoxicity, including severe lactic acidosis.
- Indinavir, a protease inhibitor, can cause kidney stones and acute kidney injury due to precipitation in urine.
Purpose of the Study:
- To review the nephrotoxicities associated with antiretroviral drugs used in HIV treatment.
- To elucidate the mechanisms of direct and indirect kidney damage from HIV medications.
- To highlight the link between HIV treatment, accelerated aging, and increased vascular risk affecting the kidneys.
Main Methods:
- Literature review of antiretroviral drug toxicities.
- Analysis of mechanisms causing lactic acidosis and renal dysfunction.
- Examination of the impact of HIV treatment on renal vascular health.
Main Results:
- Specific antiretrovirals like zalcitabine, stavudine, and didanosine can induce severe lactic acidosis.
- Indinavir is associated with uro-nephrolithiasis and various forms of kidney injury.
- Combined antiretroviral treatment is established to increase overall vascular risk, impacting kidney health.
Conclusions:
- Direct nephrotoxicity from certain antiretrovirals poses significant risks.
- Indirect renal damage linked to accelerated aging and vascular risk is a critical concern in long-term HIV management.
- Further research is needed to understand and mitigate the long-term kidney risks associated with chronic HIV treatment.

