Related Experiment Video
Updated: Feb 13, 2026

Author Spotlight: Utilizing Venoplasty Balloon Model in Rodents to Simulate Surgical Interventions for Deep Veins
Published on: May 24, 2024
Does respiratory variation of inferior vena cava diameter predict fluid responsiveness in spontaneously ventilating
Elliot Long1,2,3, Trevor Duke2,3,4, Ed Oakley1,2,3
1Department of Emergency Medicine, The Royal Children's Hospital, Melbourne, Victoria, Australia.

Objective:
The intent of fluid bolus therapy (FBT) is to increase cardiac output and tissue perfusion, yet only 50% of septic children are fluid responsive. We evaluated respiratory variation of inferior vena cava (IVC) diameter as a predictor of fluid responsiveness.
Methods:
A prospective observational study in the ED of The Royal Children's Hospital, Melbourne, Australia. Patients were spontaneously ventilating children treated with FBT for sepsis-induced acute circulatory failure. IVC ultrasound was performed prior to FBT. Trans-thoracic echocardiography was performed prior to, 5 and 60 min after FBT. IVC collapsibility index and stroke distance were calculated by a blinded Paediatric Emergency Physician and blinded Paediatric Cardiologist, respectively.
Results:
Thirty-nine fluid boluses were recorded in 33 children, 28/39 (72%) of which met criteria for fluid responsiveness at 5 min, which was sustained in 2/28 (7%) of initial fluid responders at 60 min. Sensitivity and specificity (95% confidence interval) of IVC collapsibility index were 0.44 (0.25-0.65) and 0.33 (0.10-0.65) with an area under the receiver operator characteristics curve (95% confidence interval) of 0.38 (0.23-0.55) at 5 min. Test characteristics 60 min after fluid bolus administration were not meaningful because of the infrequency of sustained fluid responsiveness in this patient group. There was no significant correlation between IVC collapsibility and fluid responsiveness at 5 or 60 min.
Conclusions:
IVC collapsibility has poor test characteristics for predicting fluid responsiveness in spontaneously ventilating children with sepsis.

Related Concept Videos
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:11
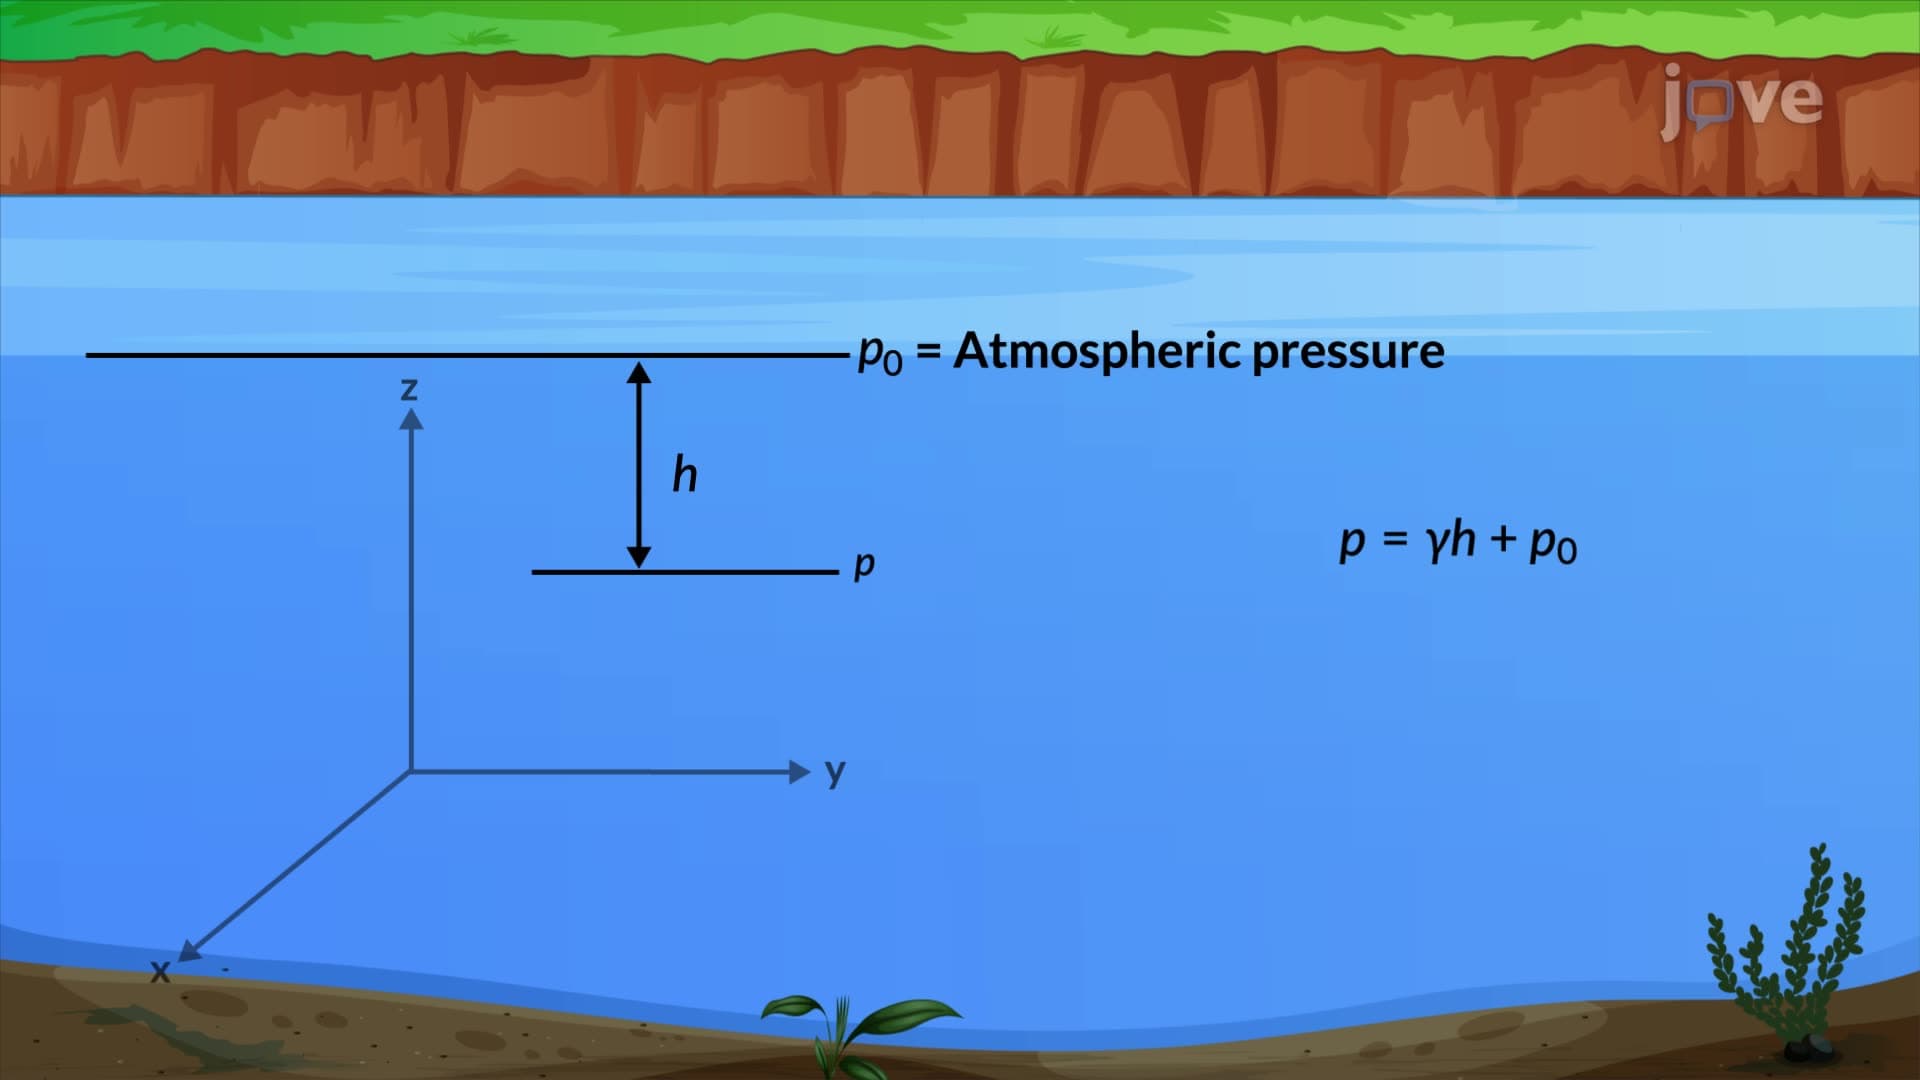
Pressure Variation in a Fluid at Rest
When measuring pressure at two different levels within the fluid, the difference in...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 02:21
Spontaneity
 01:14
What is Variation?
The range, standard deviation, standard error, and variance are the different measures of variation.
Range: The range is the difference between its maximum and...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...