Related Experiment Video
Updated: Sep 10, 2026
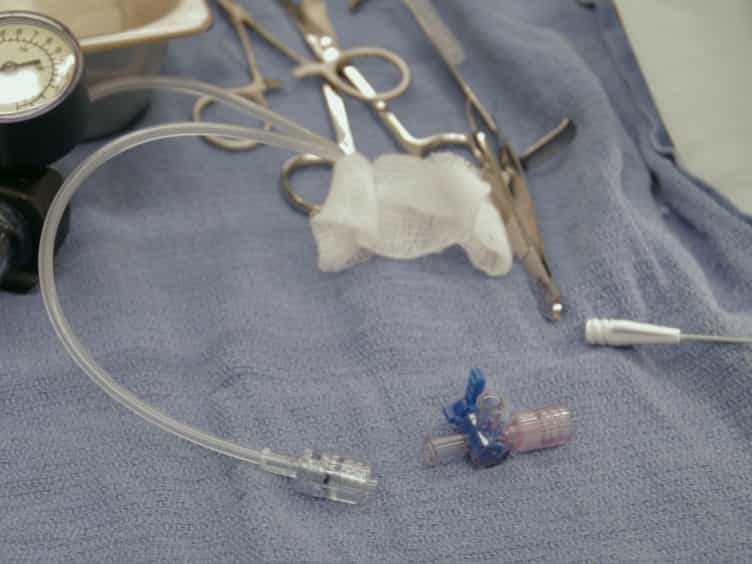

Vascular Balloon Injury and Intraluminal Administration in Rat Carotid Artery
Published on: December 23, 2014
Restenosis after arterial angioplasty: a hemorrheologic response to injury

Restenosis after arterial angioplasty appears to be a response to deep arterial injury, which is much more thrombogenic than superficial injury (endothelial denudation). Deep arterial injury exposes collagen, elastin and smooth muscle cells to circulating blood, releases tissue thromboplastin and causes immediate platelet-thrombus deposition as a result of activation of platelets and the clotting system, both of which mutually facilitate activation of the other. Regrowth of endothelium also is protective against platelet deposition. Platelet adherence to collagen, and thus to the arterial wall that is deeply injured, increases with shear rate (related inversely to the fourth power of luminal cross-sectional area and directly to blood flow); thus, the effect of shear rate increases the importance of adequate dilatation at the time of the procedure. Therapy that will reduce acute platelet-thrombus deposition appears to be an important factor for reduction of restenosis. Vasoconstriction occurs experimentally after arterial angioplasty in arterial segments proximal and distal to the dilated segment where there has been no necrosis of smooth muscle cells. The vasoconstriction is directly related to the severity of platelet deposition, can be reduced by reducing platelet deposition with low dose aspirin (1 mg/kg daily) and is probably mediated by vasoconstrictor substances from platelets (thromboxane A2, serotonin and other substances). Platelet-membrane receptor inhibitors to these substances reduce the vasoconstriction but do not reduce platelet deposition. Therapeutic intervention should probably involve both anticoagulation and platelet inhibition. Platelet-membrane receptor inhibition to the fibrinogen receptor, factor VIII-von Willebrand factor or both may be necessary acutely to sufficiently reduce acute platelet-thrombus deposition.
Restenosis after arterial angioplasty appears to be a response to deep arterial injury, which is much more thrombogenic than superficial injury (endothelial denudation). Deep arterial injury exposes collagen, elastin and smooth muscle cells to circulating blood, releases tissue thromboplastin and causes immediate platelet-thrombus deposition as a result of activation of platelets and the clotting system, both of which mutually facilitate activation of the other. Regrowth of endothelium also is protective against platelet deposition. Platelet adherence to collagen, and thus to the arterial wall that is deeply injured, increases with shear rate (related inversely to the fourth power of luminal cross-sectional area and directly to blood flow); thus, the effect of shear rate increases the importance of adequate dilatation at the time of the procedure. Therapy that will reduce acute platelet-thrombus deposition appears to be an important factor for reduction of restenosis. Vasoconstriction occurs experimentally after arterial angioplasty in arterial segments proximal and distal to the dilated segment where there has been no necrosis of smooth muscle cells. The vasoconstriction is directly related to the severity of platelet deposition, can be reduced by reducing platelet deposition with low dose aspirin (1 mg/kg daily) and is probably mediated by vasoconstrictor substances from platelets (thromboxane A2, serotonin and other substances). Platelet-membrane receptor inhibitors to these substances reduce the vasoconstriction but do not reduce platelet deposition. Therapeutic intervention should probably involve both anticoagulation and platelet inhibition. Platelet-membrane receptor inhibition to the fibrinogen receptor, factor VIII-von Willebrand factor or both may be necessary acutely to sufficiently reduce acute platelet-thrombus deposition.
Related Concept Videos
 01:28
Phases of Wound Repair
Formation of Blood Clot
In case of deep injuries, trauma to blood vessels results in blood loss. In the meantime, phospholipids released from the ruptured endothelial cellular membrane are converted into arachidonic...
 01:05
Introduction to Hemostasis
The three phases of hemostasis involve many clotting factors present in plasma and several substances released by platelets and injured tissue cells. It is a fast, localized, and...
 01:16
Vascular Spasm
 01:22
Formation of the Platelet Plug
As the injured blood vessel contracts, endothelial cells undergo contraction, revealing collagen fibers in the basement membrane and underlying connective tissue. Furthermore, the plasma membrane of endothelial cells becomes adhesive, preparing the site for platelet adhesion. Platelets...
 01:16
Clot Retraction and Fibrinolysis
 01:26
Aneurysm III: Interprofessional Care