Related Experiment Video
Updated: Aug 19, 2026


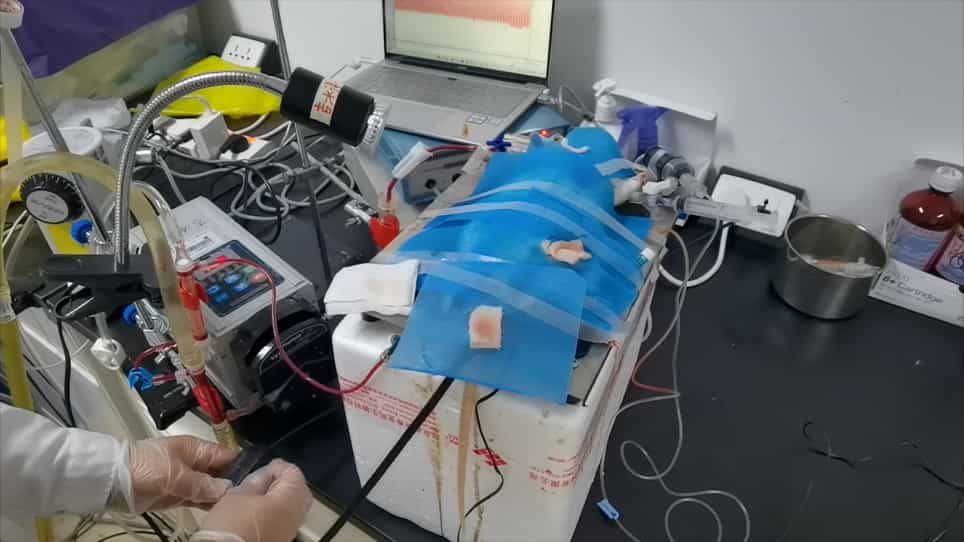
A Recovery Cardiopulmonary Bypass Model Without Transfusion or Inotropic Agents in Rats
Published on: March 23, 2018
Hormonal and metabolic changes during hypothermic coronary artery bypass surgery in diabetic and non-diabetic
P A Crock1, C J Ley, I K Martin
1University of Melbourne Department of Medicine, Fitzroy, Victoria, Australia.

Insights
Managing hyperglycemia in non-insulin-dependent diabetes mellitus (NIDDM) patients undergoing coronary artery bypass grafting (CABG) is crucial. Using a non-glucose prime solution and insulin infusion effectively prevents perioperative hyperglycemia in NIDDM patients.
Area of Science:
- Cardiology
- Endocrinology
- Metabolic Surgery
Background:
- Coronary artery bypass grafting (CABG) involves hypothermic cardiopulmonary bypass.
- Patients with non-insulin-dependent diabetes mellitus (NIDDM) may experience metabolic complications during CABG.
- Understanding hormonal and metabolic responses in NIDDM patients during CABG is critical for optimizing perioperative care.
Purpose of the Study:
- To investigate the hormonal and metabolic effects of hypothermic CABG in NIDDM patients.
- To compare the responses between NIDDM patients receiving glucose or non-glucose priming solutions and non-diabetic patients.
- To identify strategies for preventing perioperative hyperglycemia in NIDDM patients undergoing CABG.
Main Methods:
- Study included three groups: non-diabetic patients, NIDDM patients with glucose prime, and NIDDM patients with non-glucose prime.
- Monitored hormonal levels (adrenaline, noradrenaline, cortisol, glucagon) and glucose/insulin concentrations.
- Analyzed responses during hypothermic cardiopulmonary bypass and the postoperative period.
Main Results:
- No significant differences in stress hormone responses (adrenaline, noradrenaline, cortisol) between NIDDM and non-diabetic groups.
- Glucagon significantly increased during bypass only in NIDDM patients without glucose prime.
- Perioperative hyperglycemia was observed in glucose-primed groups and prevented by excluding glucose from the prime in NIDDM patients.
- Postoperative insulin rise was faster in glucose-primed NIDDM patients compared to non-glucose primed NIDDM patients.
Conclusions:
- Perioperative hyperglycemia in NIDDM patients undergoing CABG can be effectively prevented.
- Utilizing a non-glucose priming solution is a key strategy to avoid hyperglycemia during bypass.
- Postoperative insulin infusion is recommended for NIDDM patients, particularly after CABG, to manage metabolic status.
Abstract:
Hormonal and metabolic responses to hypothermic coronary artery bypass grafting (CABG) were studied in three groups: 8 non-diabetic patients, 8 patients with non-insulin-dependent diabetes mellitus (NIDDM) given a glucose pump priming solution and 8 NIDDM patients given a non-glucose infusion. There were no significant differences in stress hormone responses between NIDDM and non-diabetic patients, with adrenaline concentrations rising 10-fold, noradrenaline 4-fold and cortisol 2 to 3-fold. Glucagon rose significantly during bypass only in the NIDDM patients who did not receive a glucose prime. Comparable marked hyperglycaemia was seen in both glucose primed groups during bypass and exclusion of glucose from the prime in NIDDM patients prevented this major rise. Postoperatively, the rise in insulin in the glucose primed NIDDM patients contrasted with the slower rise in the non-glucose primed NIDDM patients who were also hyperglycaemic by this stage. Perioperative hyperglycaemia in NIDDM patients undergoing CABG can be prevented by using a non-glucose priming solution and by giving insulin infusion, particularly postoperatively.

Related Concept Videos
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management