Related Experiment Video
Updated: Feb 11, 2026


Author Spotlight: Simulating Pediatric Cardiac Surgery Using a Neonatal Piglet Model
Published on: May 26, 2023
Hybrid Extracorporeal Therapies as a Bridge to Pediatric Liver Transplantation
Ayse Akcan Arikan1,2, Poyyapakkam Srivaths1, Ryan W Himes3
1Renal Section, Department of Pediatrics, Baylor College of Medicine, Houston, TX.

Objectives:
Standard intensive care treatment is inadequate to keep children with liver failure alive without catastrophic complications to ensure successful transplant, as accumulation of endogenous protein-bound toxins often lead to hepatic encephalopathy, hepatorenal syndrome, cardiovascular instability, and multiple organ failure. Given paucity of proven treatment modalities for liver failure, blood purification using different extracorporeal treatments as a bridge to transplantation is used, but studies evaluating the safety and efficacy of combination of these therapies, especially in pediatric liver failure, are lacking. We describe our experience at a major tertiary children's hospital, where a unique hybrid extracorporeal treatment protocol has been instituted and followed for acute liver failure or acute-on-chronic liver failure as a bridge to transplantation. This protocol combines high-flux continuous renal replacement therapy for hyperammonemia, therapeutic plasma exchange for coagulopathy, and albumin-assisted dialysis (molecular adsorbent recirculating system) for hepatic encephalopathy.
Design:
Retrospective observational study.
Setting:
Freestanding tertiary children's hospital and liver transplant referral center.
Patients:
All patients with acute liver failure/acute-on-chronic liver failure receiving hybrid extracorporeal therapy over 24 months.
Intervention:
Hybdrid extracorporeal therapy.
Measurements And Main Results:
Fifteen children (age 3 yr [0.7-9 yr]; 73% male) with acute liver failure/acute-on-chronic liver failure who were either listed or actively considered for listing and met our protocol criteria were treated with hybrid extracorporeal therapy; 93% were ventilated, and 80% were on vasoactive support. Of these, two patients recovered spontaneously, four died prior to transplant, and nine were successfully transplanted; 90-day survival post orthotopic liver transplant was 100%. Overall survival to hospital discharge was 73%.
Conclusions:
Hybrid extracorporeal therapies can be effectively implemented in pediatric liver failure as a bridge to transplantation. Overall complexity and heavy resource utilization need to be carefully considered in instituting these therapies in suitable candidates.
Related Concept Videos
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:15
Design Example: Strain Gauge Bridge or Wheatstone Bridge
 01:29
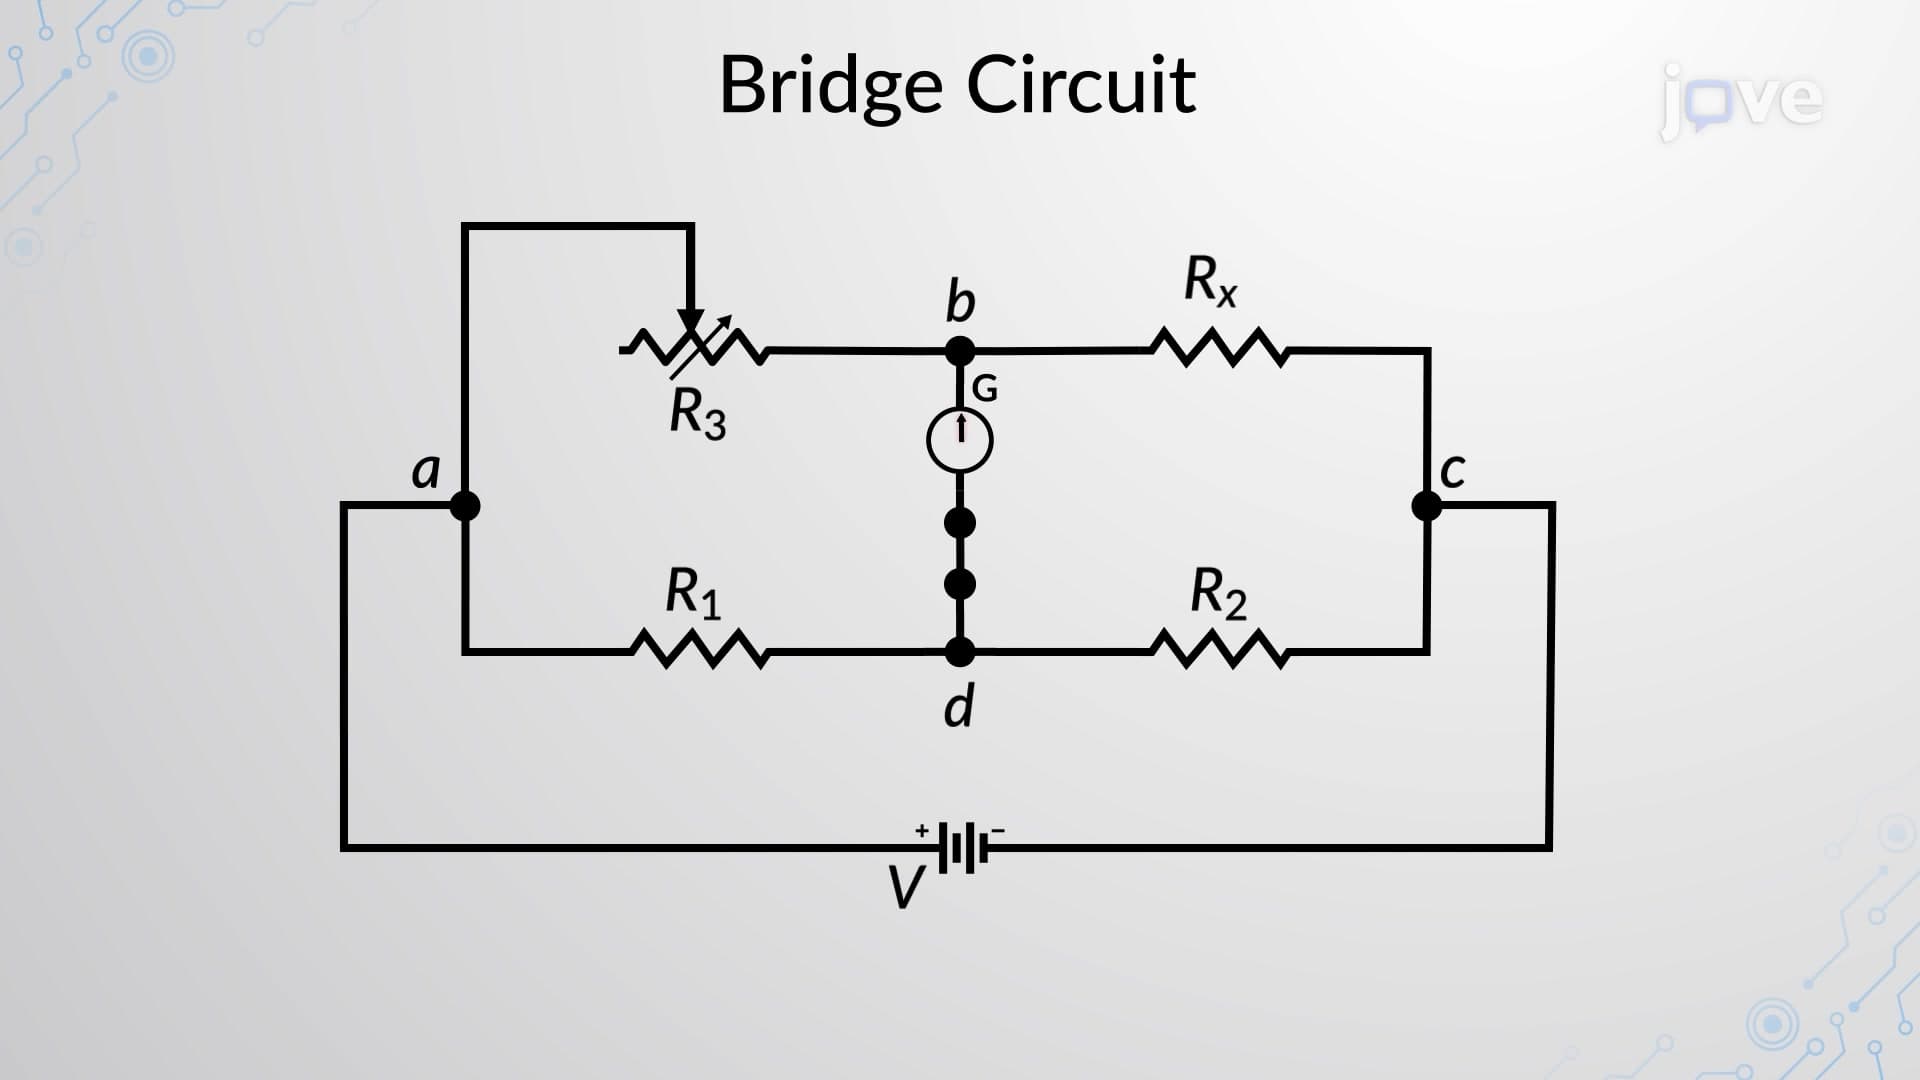
Wheatstone Bridge
Thus, for accurate resistance measurements, a...
 01:24
Bridge rectifier
Operationally, the bridge rectifier allows current flow through two of its diodes during each...
 00:59
Gene Therapy
 01:26
Cross-bridge Cycle