Related Experiment Video
Updated: Jan 9, 2026

Pulmonary Embolism III: Nursing Management
Published on: June 19, 2025
Pathogenesis of sodium retention complicating cirrhosis: is there room for diminished "effective" arterial blood
1Department of Medicine, Denver General Hospital, University of Colorado Health Sciences Center.

Abstract:
We measured total blood volume (125I-albumin), cardiac dimensions and function (echocardiography with Doppler), systemic hemodynamics (blood pressure and pulse), and plasma renin activity and norepinephrine levels in cirrhotic patients with and without ascites to assess the likelihood that either diminished central or arterial filling is the stimulus to sodium retention. Patients with ascites (n = 9) had significantly increased total blood volume, cardiac output, pulse rate, plasma renin activity, and plasma norepinephrine concentration, as well as decreased systemic vascular resistance and arterial blood pressure compared with patients without ascites (n = 8). Left atrial size was similar in the two groups but significantly larger than in normal control subjects. Right and left atrial pressures were also similar in retrospectively studied patients with and without ascites. Sodium retention in cirrhosis is probably not triggered by diminished central filling. Increased blood volume is compatible with either a primary hepatorenal stimulus to sodium retention or a signal arising from a region of underfilling within an otherwise expanded circulation. If the latter model is correct, a "hyperdynamic" systemic circulation and increased plasma neurohormone concentrations may indicate "effective" arterial underfilling in patients with ascites.
Related Concept Videos
 01:27
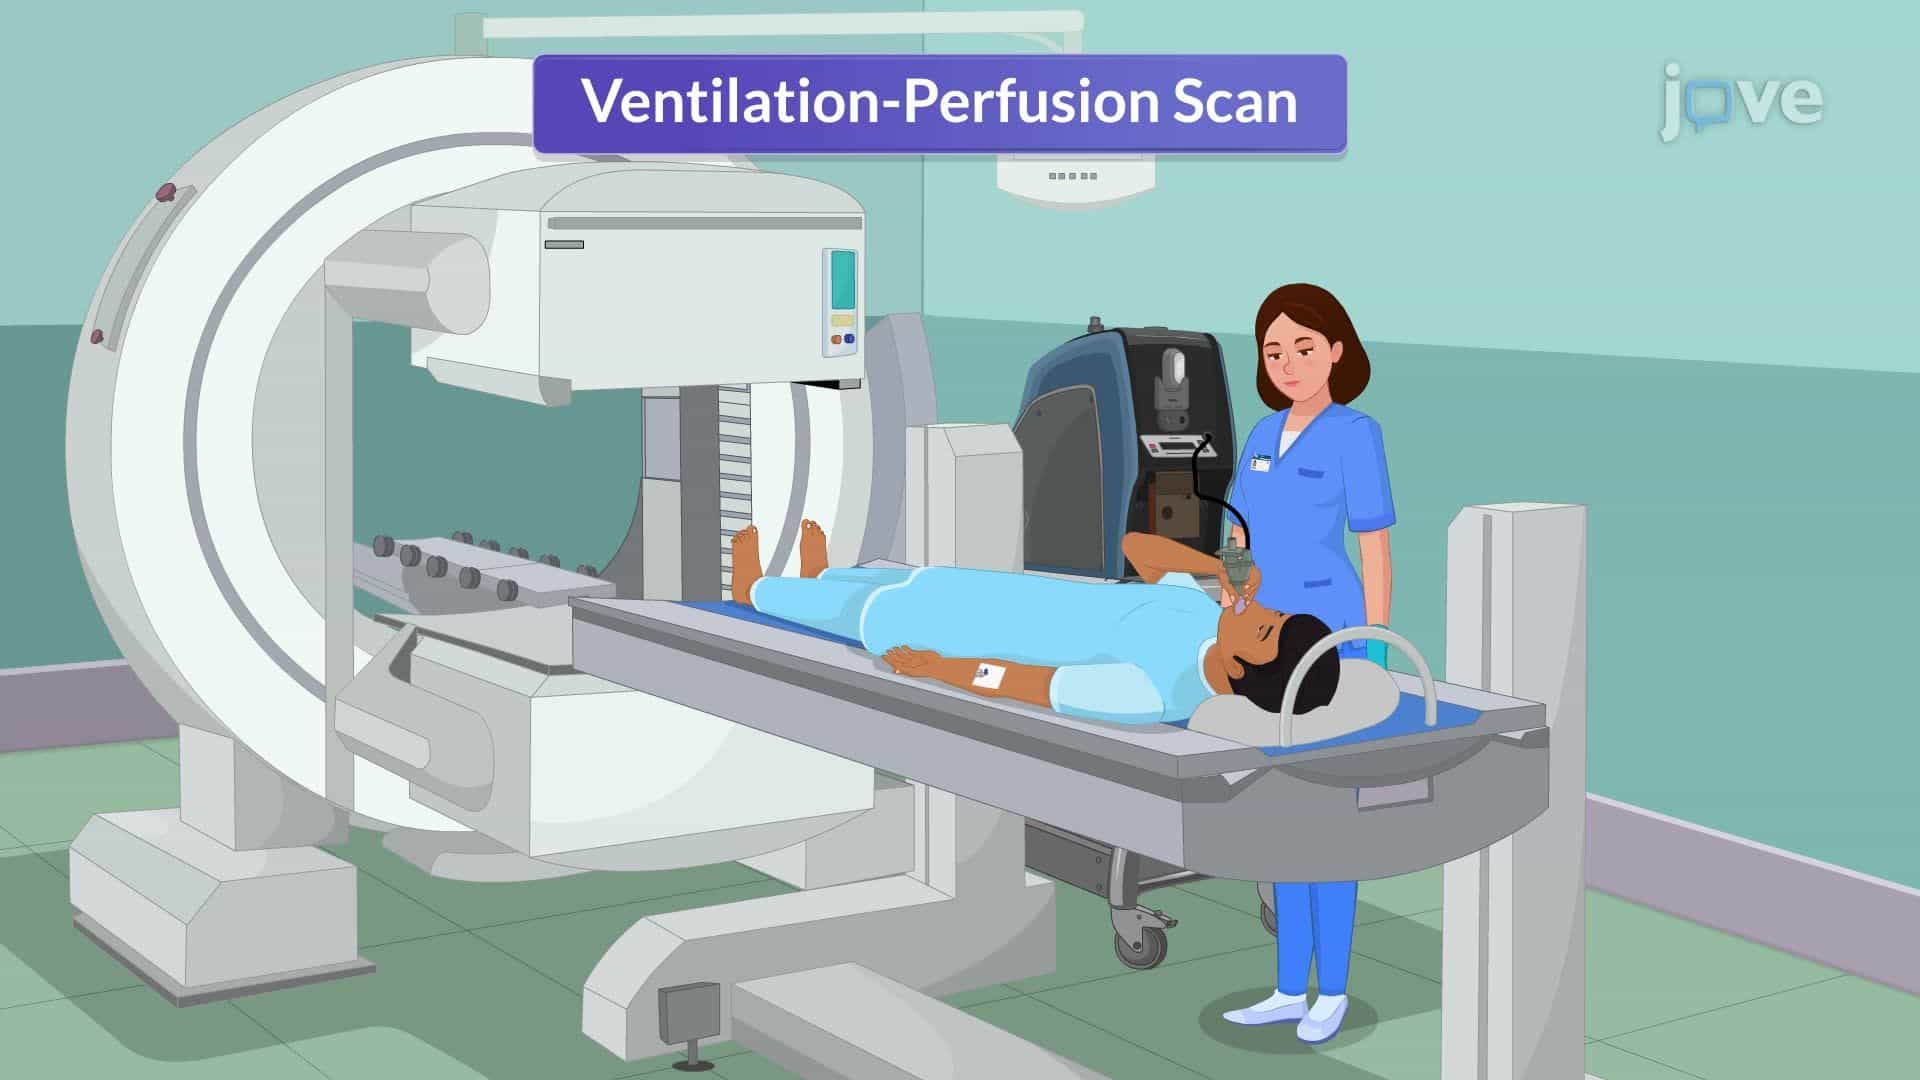
Pulmonary Embolism III: Nursing Management
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:29
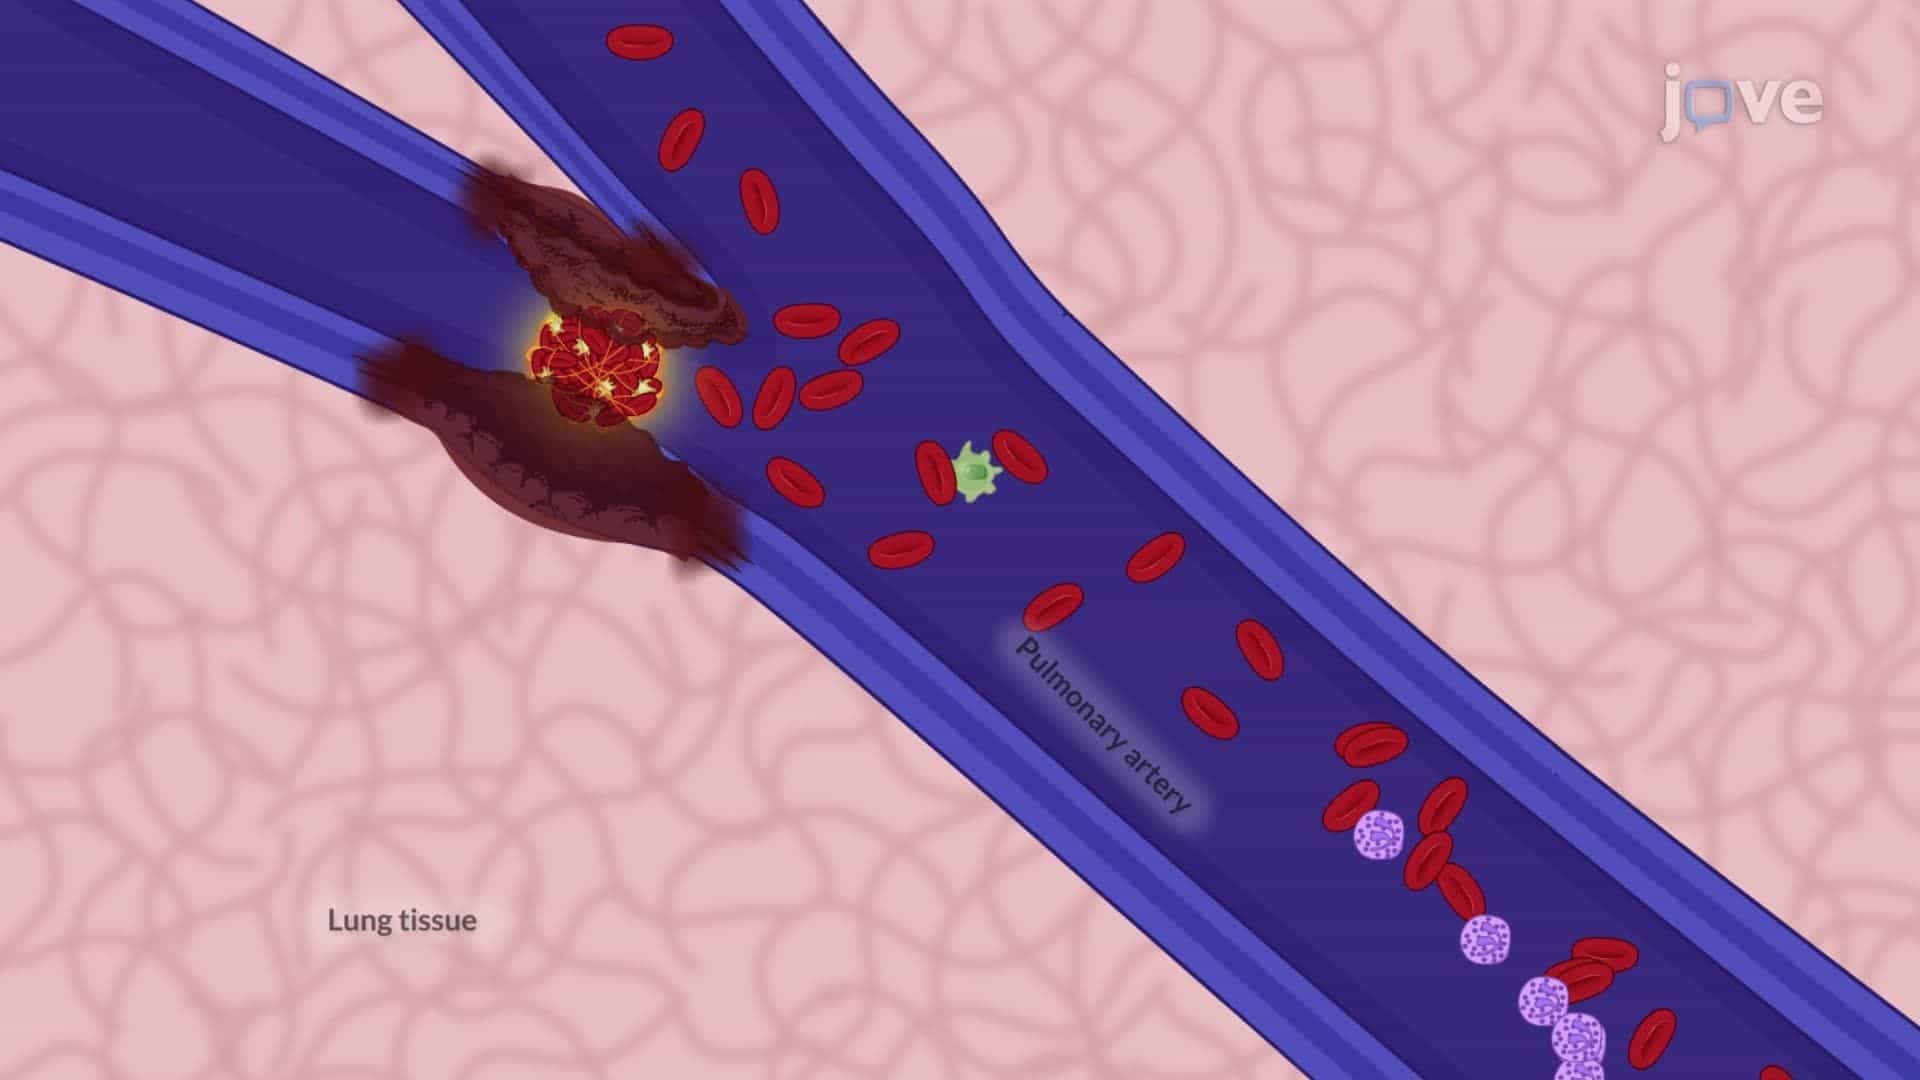
Pulmonary Embolism I: Introduction
 01:29
Venous Thrombosis III: Interprofessional Care
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
Smoking Cessation