Age-adjusted versus clinical probability-adjusted D-dimer to exclude pulmonary embolism
Related Experiment Video
Updated: Feb 10, 2026
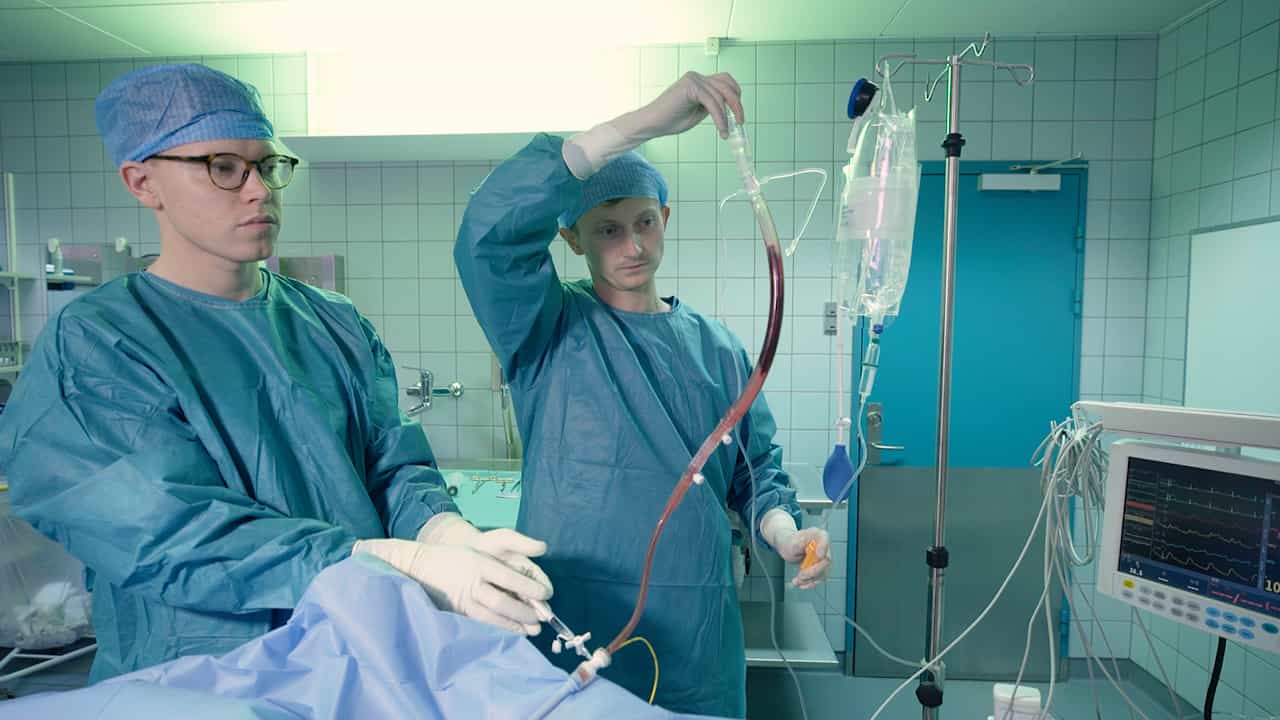
A Porcine Model of Acute Autologous Pulmonary Embolism
Published on: September 6, 2024
Sarah Takach Lapner1, Scott M Stevens2, Scott C Woller2
1Department of Medicine, University of Alberta, 4-112 Clinical Sciences Building, 11350 83 Avenue, Edmonton, AB T6G 2R3, Canada.

Introduction:
A low D-dimer can exclude suspected pulmonary embolism (PE) in cases with low or intermediate clinical probability of disease. Yet D-dimer is nonspecific, so many cases without PE require imaging. D-dimer's specificity is improved by increasing the threshold for a positive test with age (age × 10 ng/mL; age-adjusted D-dimer; AADD) or clinical probability of PE (1000 ng/mL if low and 500 ng/mL if intermediate clinical probability; clinical probability-adjusted D-dimer; CPADD). It is unclear which approach is preferable.
Objectives:
We report the sensitivity, specificity and negative predictive value (NPV) of AADD compared to CPADD in suspected PE.
Materials And Methods:
A retrospective cohort of 3500 consecutive cases imaged for suspected PE at two U.S. emergency departments was assembled. We analyzed cases with low or intermediate clinical probability of PE (Revised Geneva Score) who had a D-dimer. The outcome was acute PE on imaging at presentation.
Results:
Of the 3500 cases, 1745 were eligible. 37% were low, and 63% were intermediate clinical probability of PE. PE was present in 145 (8.3%) cases. Sensitivity of CPADD was 87.5% vs. 96.6% for AADD (difference 9.1%; 95% CI 4.3% to 14.0%). NPV of CPADD was 97.1% vs. 99.0% for AADD (difference 1.9%; 95% CI, 0.7% to 3.1%). Specificity of CPADD was 37.5% vs. 30.2% for AADD (difference -7.3%; 95% CI -9.4% to -5.1%). D-dimer was negative in 35.4% of cases using CPADD vs. 28.0% using AADD.
Conclusions:
CPADD modestly improved the specificity of D-dimer, but had a lower NPV than AADD. AADD appears preferable in this analysis.


Related Concept Videos
 01:25
The Anchoring-and-Adjustment Heuristic
 01:12
Adjusting a Traverse
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:29
Pulmonary Embolism I: Introduction
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:27
Pulmonary Embolism III: Nursing Management