D-dimer in Routine Hospital Practice: Diagnostic Accuracy for Venous Thromboembolism
Related Experiment Video
Updated: Nov 7, 2026
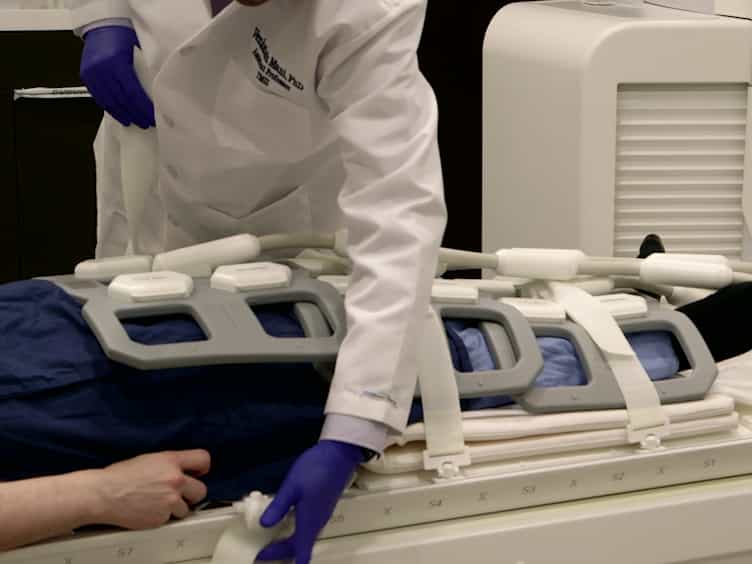
A Multicenter MRI Protocol for the Evaluation and Quantification of Deep Vein Thrombosis
Published on: June 2, 2015
Ammour Abdesselam1,2, Reda Amrani Souhli1,2, Moussab Arbai1,2
1Medical Biology Department, Faculty of Medicine and Pharmacy, Abdelmalek Essaadi University, Tangier, MAR.

Abstract:
Background D-dimer is a sensitive rule-out test for venous thromboembolism (VTE), but most validation data come from selected cohorts with suspected embolism, and its performance in unselected hospital populations is less well characterized. We assessed the diagnostic performance of plasma D-dimer for VTE in an unselected hospital population, with pulmonary embolism (PE) as a subgroup, and evaluated the impact of an age-adjusted D-dimer threshold. Methods In this one-year retrospective study (May 2025-April 2026), 100 patients were included from 143 consecutive plasma D-dimer requests at a tertiary university hospital in Tangier, Morocco, irrespective of department or clinical indication. D-dimer was measured by immunoturbidimetric assay (threshold 500 ng/mL) and compared with CT pulmonary angiography (CTPA) for PE and venous Doppler ultrasound for deep vein thrombosis (DVT) in patients with a documented reference standard, with PE as a pre-specified subgroup. Results The study population (53% female; mean age 55.6 years) had D-dimer requested across many departments, most often adult emergency (54%). Values were right-skewed (median 814 ng/mL); 65% were positive. Imaging confirmed thromboembolic disease in 15 patients, including 12 venous events (nine PE, three DVT), and excluded it in 26. For VTE, sensitivity was 91.7% (95% CI 61.5-99.8) and negative predictive value (NPV) 92.9% (95% CI 66.1-99.8), with specificity 50.0% (95% CI 29.9-70.1), positive predictive value (PPV) 45.8% (95% CI 25.6-67.2) and an area under the curve (AUC) of 0.72 (95% CI 0.55-0.87). For PE, sensitivity and NPV both reached 100% (95% CI 66.4-100.0 and 73.5-100.0), with specificity 52.2% (95% CI 30.6-73.2). An age-adjusted D-dimer threshold raised specificity for VTE to 65.4% without loss of sensitivity. Conclusion In this unselected hospital population, plasma D-dimer showed high sensitivity for PE but low specificity, in keeping with its established role as a rule-out test. Its use in routine practice should be guided by clinical pretest probability and, where appropriate, age-adjusted thresholds.
Related Concept Videos
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:29
Venous Thrombosis III: Interprofessional Care
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:30
Venous Thrombosis I: Introduction
 01:24
Automated Microbial Diagnostics
 01:30
Venous Thrombosis IV: Nursing Management