Related Experiment Video
Updated: Feb 10, 2026
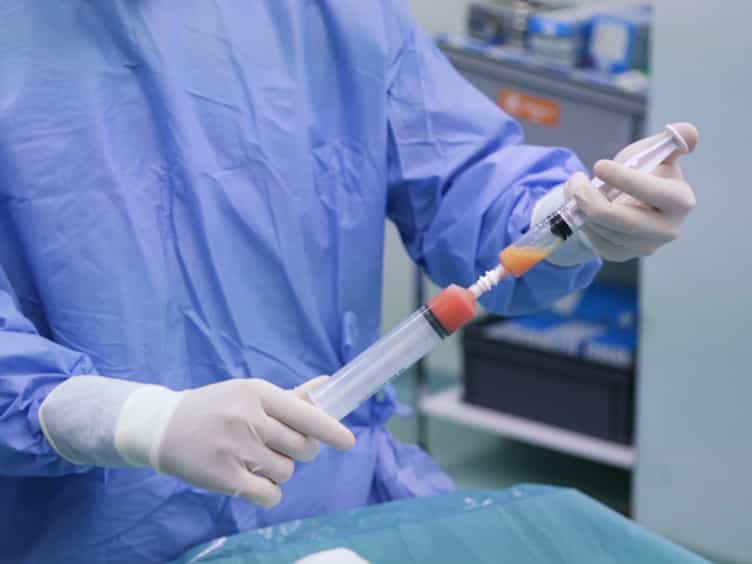
Autologous Microfractured and Purified Adipose Tissue for Arthroscopic Management of Osteochondral Lesions of the Talus
Published on: January 23, 2018
Effects of Bone Incorporation After Arthroscopic Stabilization Surgery for Bony Bankart Lesion Based on Preoperative
In Park1, Jae-Hoo Lee1, Hwan-Sub Hyun1
1Department of Orthopedic Surgery, College of Medicine, Ewha Womans University Mokdong Hospital, Seoul, Republic of Korea.

Background:
Recurrent shoulder instability occurs more frequently after soft tissue surgery when the glenoid defect is greater than 20%. However, for lesions less than 20%, no scientific guidance is available regarding what size of bone fragments may affect shoulder functional restoration after bone incorporation. Purpose/Hypothesis: The purpose was to analyze how preoperative glenoid defect size and bone fragment incorporation alter postoperative clinical outcomes, we compared the functional outcomes of shoulders with and without bony Bankart lesion. It was hypothesized that differences in postoperative clinical outcomes between patients with and without bony fragments would be found only in patients with a larger glenoid defect.
Study Design:
Cohort study; Level of evidence, 3.
Methods:
A total of 223 patients who underwent arthroscopic stabilization surgery for recurrent anterior shoulder instability were divided into two groups based on the presence of anterior glenoid bone fragments. In each group, postoperative shoulder functional outcomes, sports activity level, and recurrence rates were evaluated according to preoperative glenoid defect size (small, <10%; medium, 10%-15% and 15%-20%; large, >20%).
Results:
In patients with small or medium defects, no significant differences were found in postoperative clinical outcomes and sports activity levels between the two groups. However, in patients with a large defect, the patients with bone fragments (mean ± SD American Shoulder and Elbow Surgeons [ASES] score, 92.3 ± 2.7; Rowe score, 90.9 ± 5.4) showed significantly superior clinical outcomes compared with patients who did not have fragments (ASES score, 87.3 ± 6.2, P = .02; Rowe score, 84.8 ± 7.3, P = .04). Among patients without bone fragments, recurrence increased significantly with increasing preoperative glenoid defect size (recurrence rates: 0% in small defects, 7.4% in medium defects, 22.2% in large defects), whereas patients with bone fragments showed no tendency for increasing or decreasing recurrence rates (0% in small defects, 7.9% in medium defects, 5.9% in large defects).
Conclusion:
In the treatment of bony Bankart lesion, the effect of bone fragment incorporation was different according to preoperative glenoid defect size. In patients with preoperative glenoid defects less than 20% of the glenoid width, bone fragment incorporation after arthroscopic bony Bankart repair did not alter clinical outcomes, sports activity levels, or recurrence rates, whereas in patients with defects greater than 20% of the glenoid width, bone fragment incorporation improved clinical outcomes and recurrence rates.
More Related Videos
 06:38
Establishment of a Segmental Femoral Critical-size Defect Model in Mice Stabilized by Plate Osteosynthesis
Published on: October 12, 2016
 08:20
A Reliable and Reproducible Critical-Sized Segmental Femoral Defect Model in Rats Stabilized with a Custom External Fixator
Published on: March 24, 2019
Related Concept Videos
 01:23
Factors Affecting Dissolution: Particle Size and Effective Surface Area
 03:18
Nuclear Stability
To hold positively charged protons together...
 01:53
RNA Stability
 01:23
Lumber Defects
Shakes are minor fractures that run along or across the wood's annual rings, while wane is...
 01:28
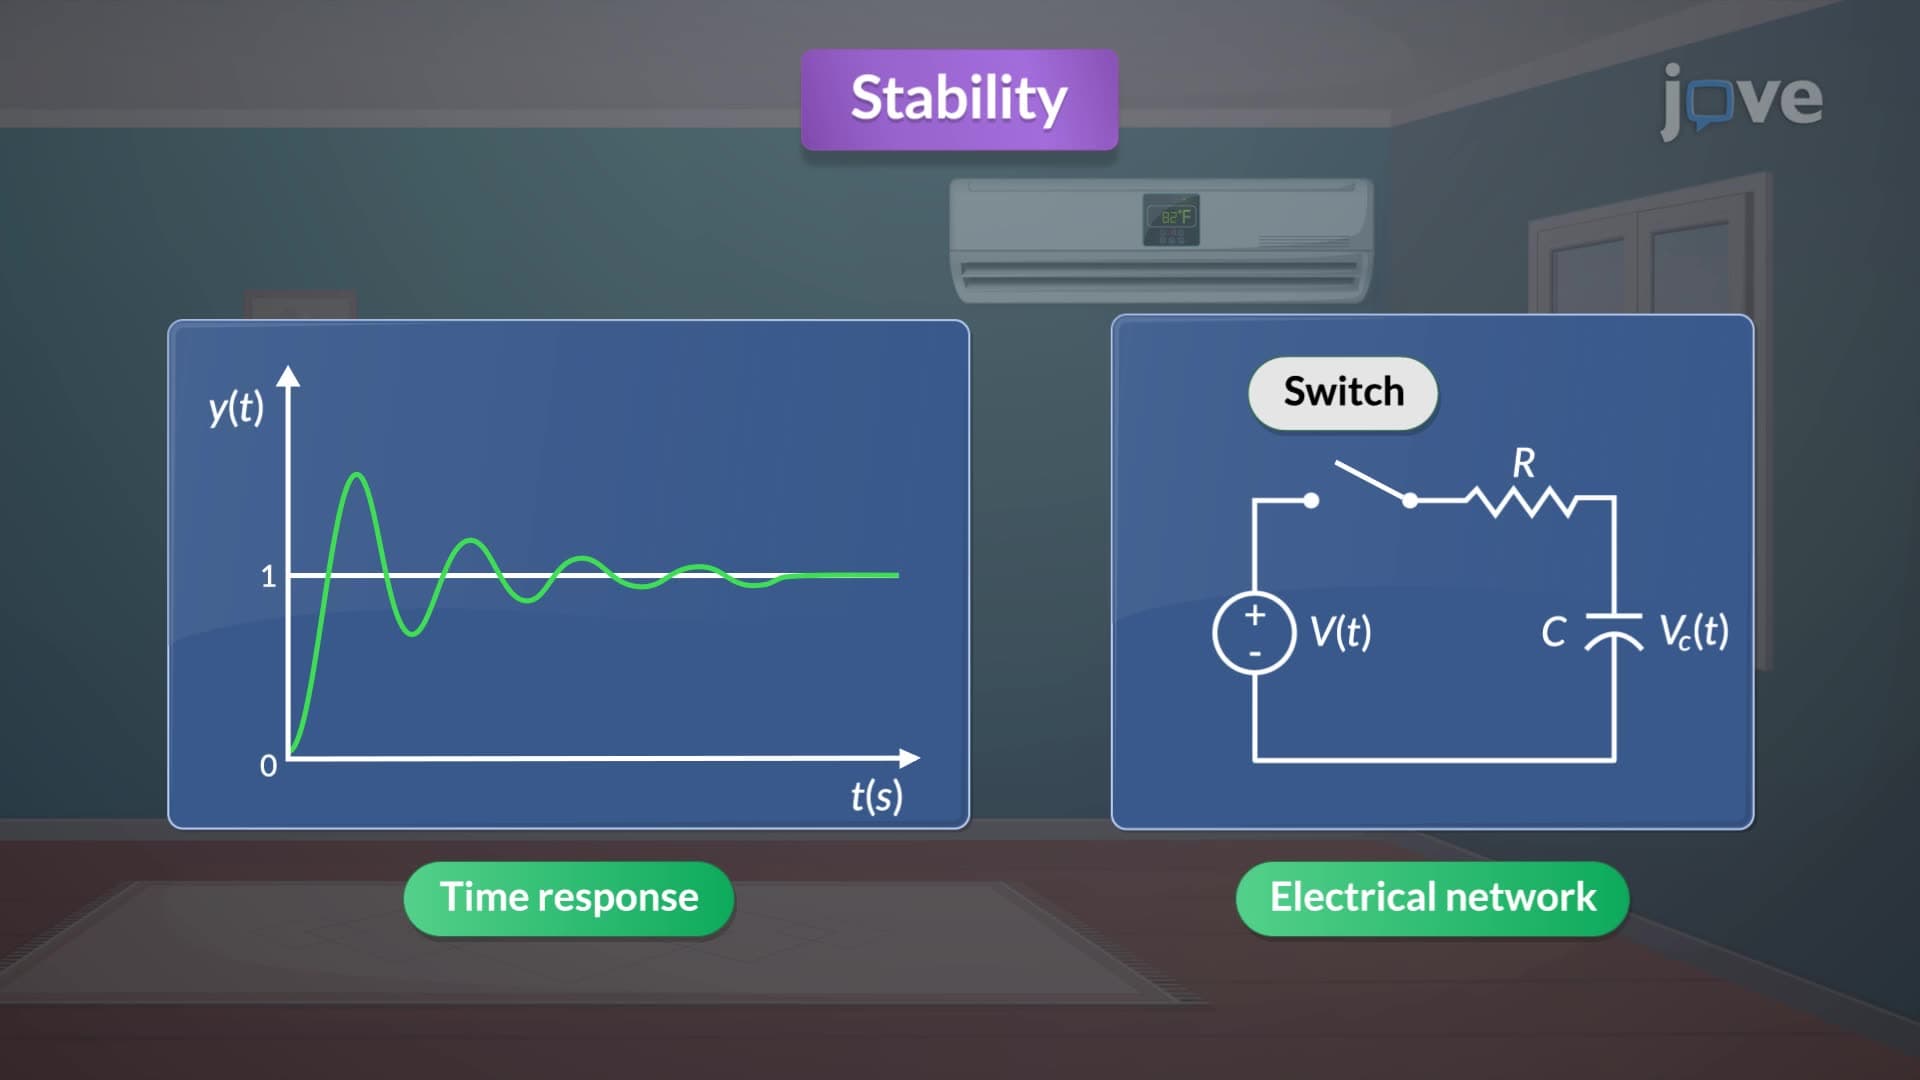
Stability
The stability of an LTI system is determined by the roots of its characteristic equation, known as poles. A system is stable if it produces a bounded...
 01:22
Cell Size
Surface Area
Cells can take in nutrients and water via diffusion through the plasma membrane itself or through specific channels in the membrane. The area of the membrane surrounding...