Related Experiment Video
Updated: Feb 9, 2026


In Vivo Electrophysiological Measurement of the Rat Ulnar Nerve with Axonal Excitability Testing
Published on: February 6, 2018
Ulnar Nerve Injury in Pediatric Midshaft Forearm Fractures: A Case Series
Andrew E Federer1, Joshua S Murphy2, James H Calandruccio3
1Department of Orthopaedic Surgery, Duke University Medical Center, Durham, NC.

Objectives:
To describe a midshaft forearm fracture pattern that places the ulnar nerve at risk in the pediatric population and provide 7 clinical case examples describing the injury pattern and treatment methods.
Design:
Retrospective observational case series, review of literature, cadaver dissection, and treatment recommendations.
Setting:
Multi-institutional, Southeast United States.
Patients:
Seven pediatric patients (5 male and 2 female) with mean age of 8.7 years (range, 3-14) who sustained a significantly displaced closed, or grade I open, middle to distal one-third both-bone forearm fracture with subsequent ulnar nerve dysfunction.
Interventions:
Manual reduction and casting of both-bone forearm shaft fractures, operative debridement, fracture fixation, nerve exploration, neurolysis, nerve repair, and nerve grafting.
Main Outcome Measurements:
Radiographic fracture union, clinical ulnar nerve motor and sensory function testing, along with selective electric nerve testing and advanced imaging were monitored throughout follow-up postinjury.
Results:
Five of 7 patients underwent surgical treatment and 2 others were treated with conservative measures. The ulnar nerve was entrapped within the fracture site of one patient with an open fracture along with partial nerve transection, and 4 patients were found to have the nerve encased in hypertrophic scar tissue or bony callus upon surgical exploration at 3-12 months postinjury.
Conclusions:
The ulnar nerve lies in a precarious position in the middle to distal one-third forearm and is bound by anatomic constraints that place the nerve at risk of injury. This article offers a treatment algorithm that includes conservative treatment, acute exploration, early exploration (≤3 months), and late exploration (>3 months).
Level Of Evidence:
Therapeutic Level IV. See Instructions for Authors for a complete description of levels of evidence.
Related Concept Videos
 01:16
Muscles that Move the Forearm
Forearm Flexors
The biceps brachii, brachialis, and brachioradialis are forearm flexors. The biceps brachii is made up of two heads. Its long head originates at the supraglenoid tubercle of the scapula, whereas that of the short head is...
 01:16
Muscles of the Forearm that Move the Hand and Fingers
Anterior Compartment
The anterior compartment muscles originate from the humerus. They primarily function as flexors and are also known as flexor muscles. They typically insert on the carpals, metacarpals, and phalanges. The superficial layer includes the flexor carpi...
 01:10
Resistors In Series
In a series circuit, the...
 01:17
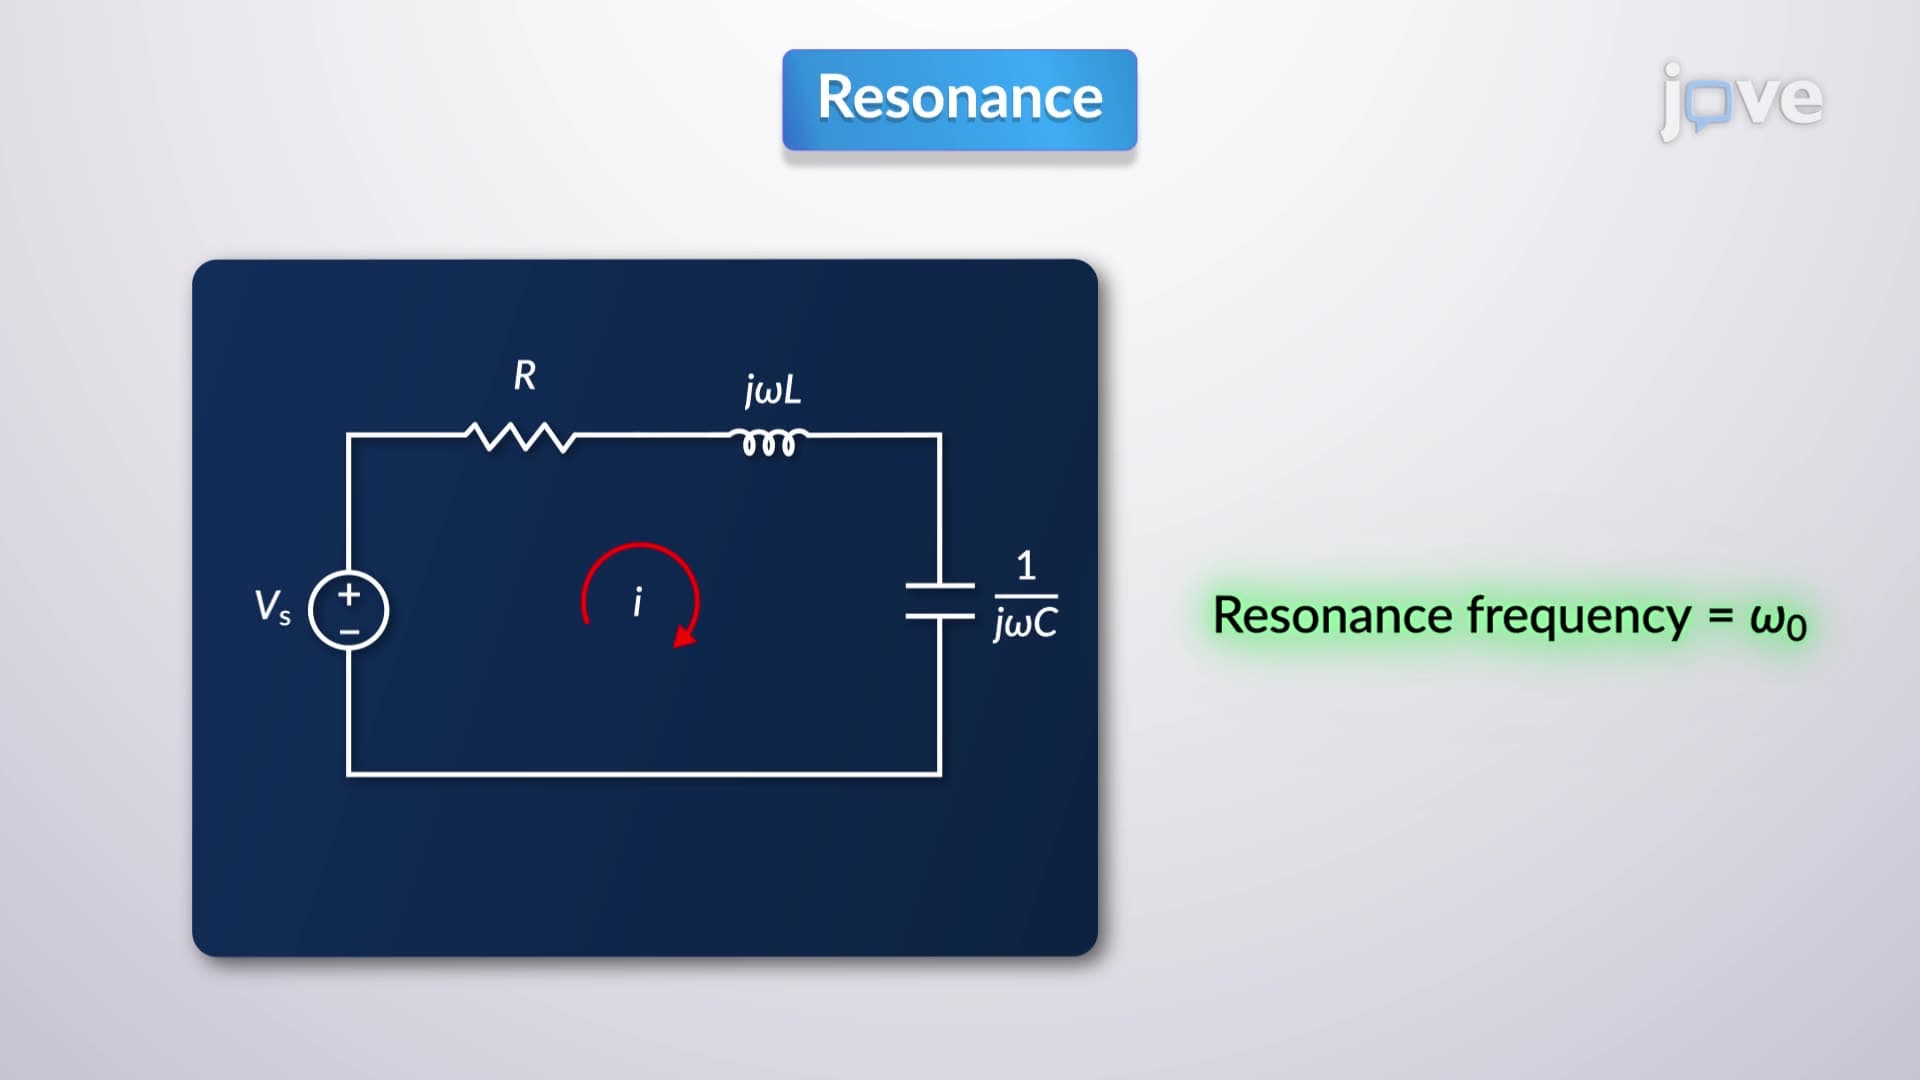
Series Resonance
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:14
Series and Parallel Capacitors
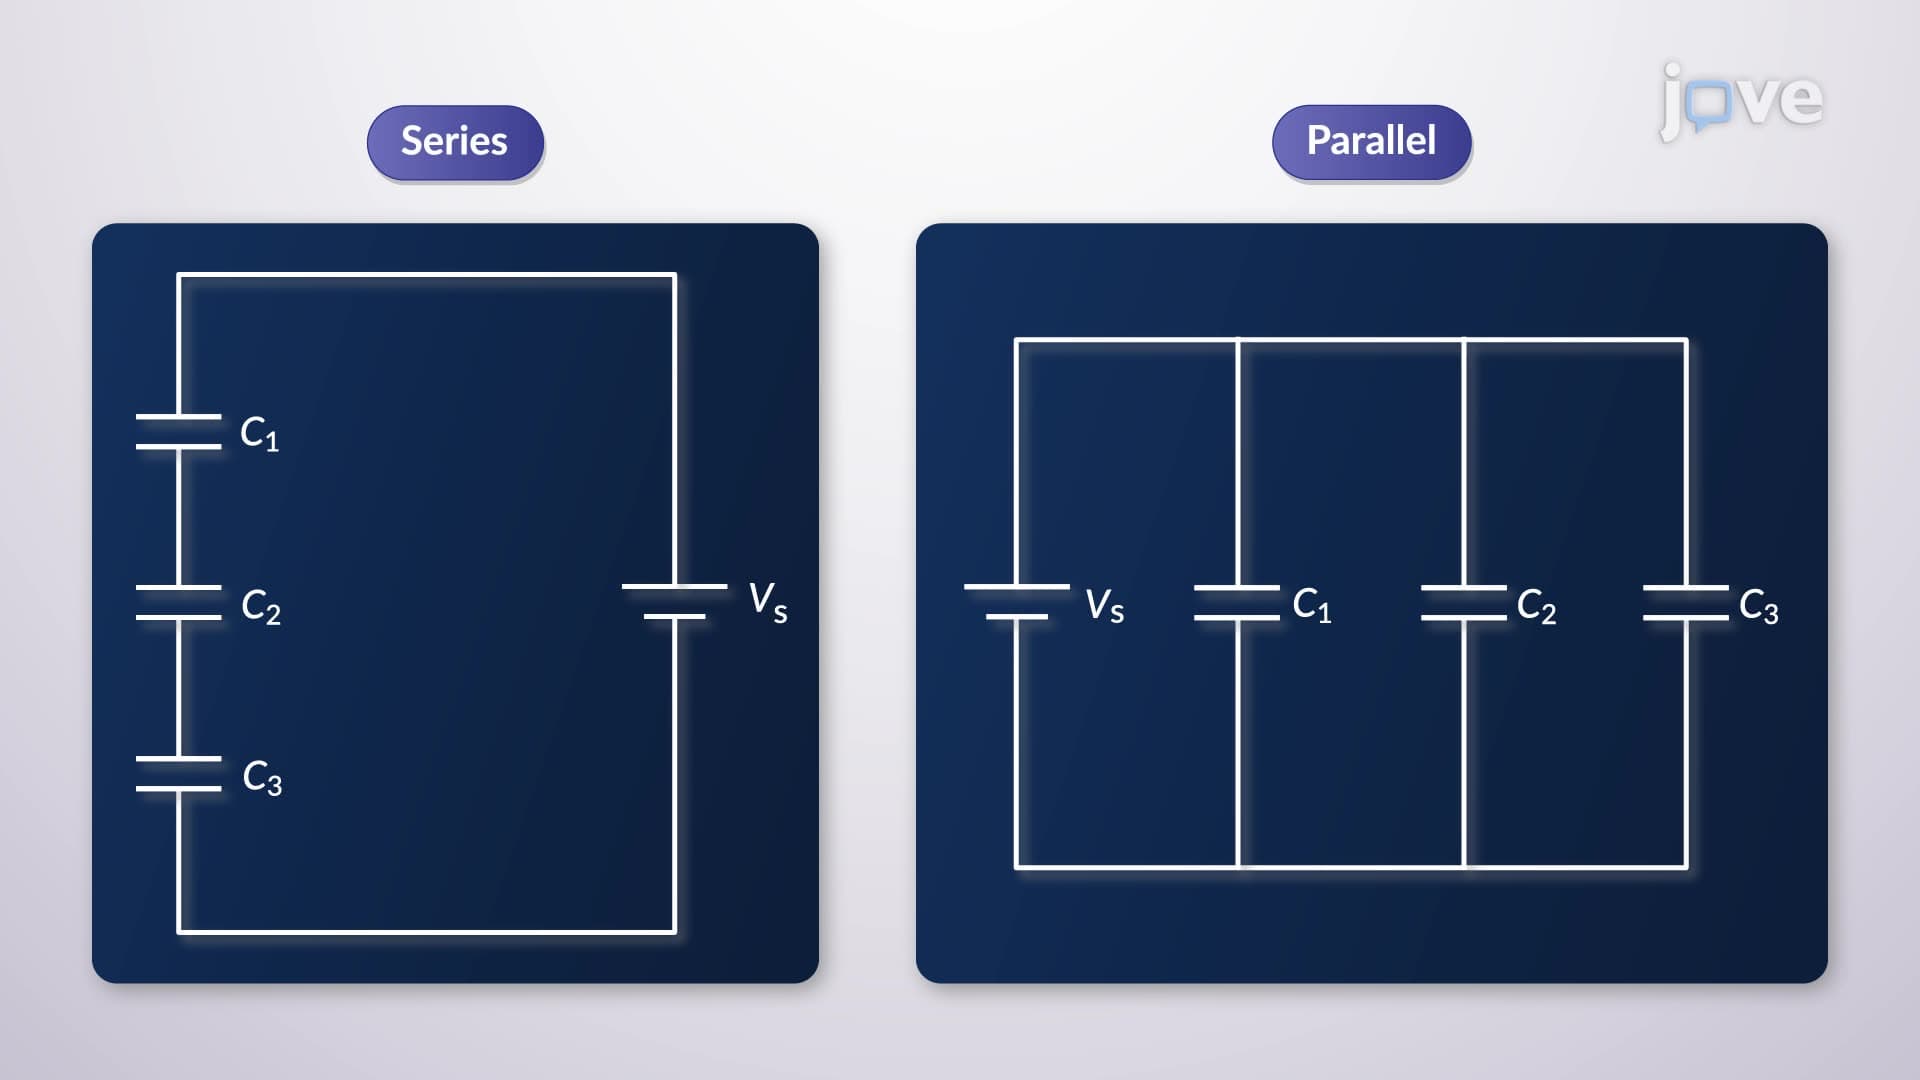
First, consider capacitors connected in series to a battery. In this configuration, the plate connected to the battery's positive terminal develops a positive charge, while the plate attached to the negative terminal becomes negatively charged. An equal magnitude of charge is induced on the...