Related Experiment Video
Updated: Feb 8, 2026

Postconditioning with Lactate-enriched Blood for Cardioprotection in ST-segment Elevation Myocardial Infarction
Published on: May 28, 2019
Survival benefit from recent changes in management of men and women with ST-segment elevation myocardial infarction
Łukasz Zandecki1,2, Marcin Sadowski3,4, Marianna Janion5,4
12nd Cardiology Clinic, Swietokrzyskie Cardiology Center, Kielce, Poland. lukasz.zandecki@gmail.com.

Insights
Improvements in percutaneous coronary interventions (PCI) for ST-segment elevation myocardial infarction (STEMI) reduced in-hospital deaths but did not improve 30-day or 1-year survival rates. Further optimization of guideline-recommended pharmacotherapy is needed for STEMI patients treated with PCI.
Area of Science:
- Cardiology
- Interventional Cardiology
- Public Health
Background:
- Primary percutaneous coronary intervention (PCI) is the standard treatment for ST-segment elevation myocardial infarction (STEMI).
- Despite advancements in PCI techniques, devices, and pharmacotherapy, further reductions in mortality for PCI-treated STEMI patients remain uncertain.
- This study examines changes in STEMI management and outcomes in a real-world setting.
Purpose of the Study:
- To compare management strategies and mortality rates in PCI-treated STEMI patients between 2005 and 2011.
- To identify temporal trends in PCI procedures and pharmacotherapy use.
- To assess the impact of these changes on in-hospital, 30-day, and 1-year mortality.
Main Methods:
- Analysis of 79,522 STEMI patients treated with PCI from the Polish Registry of Acute Coronary Syndromes (PL-ACS) between 2005 and 2011.
- Comparison of in-hospital management trends between men and women.
- Propensity score matching of patients from 2005 and 2011 to compare mortality and management outcomes.
Main Results:
- Significant changes in management observed, including reduced time to PCI, increased use of drug-eluting stents and potent antiplatelet agents.
- Decreased use of statins, beta-blockers, and ACE inhibitors/ARBs noted.
- While in-hospital mortality decreased significantly after propensity score adjustment, 30-day and 1-year mortality rates showed no significant change between 2005 and 2011.
Conclusions:
- Management of PCI-treated STEMI patients evolved significantly between 2005 and 2011, leading to reduced in-hospital mortality.
- These management changes did not translate into improved 30-day or 1-year survival at a population level.
- There is a need to improve the utilization of guideline-recommended pharmacotherapy in STEMI patients undergoing PCI.
Background:
Nowadays, the majority of patients with myocardial infarction with ST-segment elevation (STEMI) are treated with primary percutaneous coronary interventions (PCI). In recent years, there have been ongoing improvements in PCI techniques, devices and concomitant pharmacotherapy. However, reports on further mortality reduction among PCI-treated STEMI patients remain inconclusive. The aim of this study was to compare changes in management and mortality in PCI-treated STEMI patients between 2005 and 2011 in a real-life setting.
Methods:
Data on 79,522 PCI-treated patients with STEMI from Polish Registry of Acute Coronary Syndromes (PL-ACS) admitted to Polish hospitals between 2005 and 2011 were analyzed. First, temporal trends of in-hospital management in men and women were presented. In the next step, patients from 2005 and 2011 were nearest neighbor matched on their propensity scores to compare in-hospital, 30-day and 1-year mortality rates and in-hospital management strategies and complications.
Results:
Some significant changes were noted in hospital management including shortening of median times from admission to PCI, increased use of drug-eluting stents, potent antiplatelet agents but also less frequent use of statin, beta-blockers and angiotensin converting enzyme inhibitors and angiotensin II receptor blockers. There was a strong tendency toward preforming additional PCI of non-infarct related arteries, especially in women. After propensity score adjustment there were significant changes in inhospital but not in 30-day or 1-year mortality rates between 2005 and 2011. The results were similar in men and women.
Conclusions:
There were apparent changes in management and significant in-hospital mortality reductions in PCI-treated STEMI patients between 2005 and 2011. However, it did not result in 30-day or 1-year survival benefit at a population level. There may be room for improvement in the use of guideline-recommended pharmacotherapy.

Related Concept Videos
 01:26
Acute Coronary Syndrome V: Nursing Management
 03:12
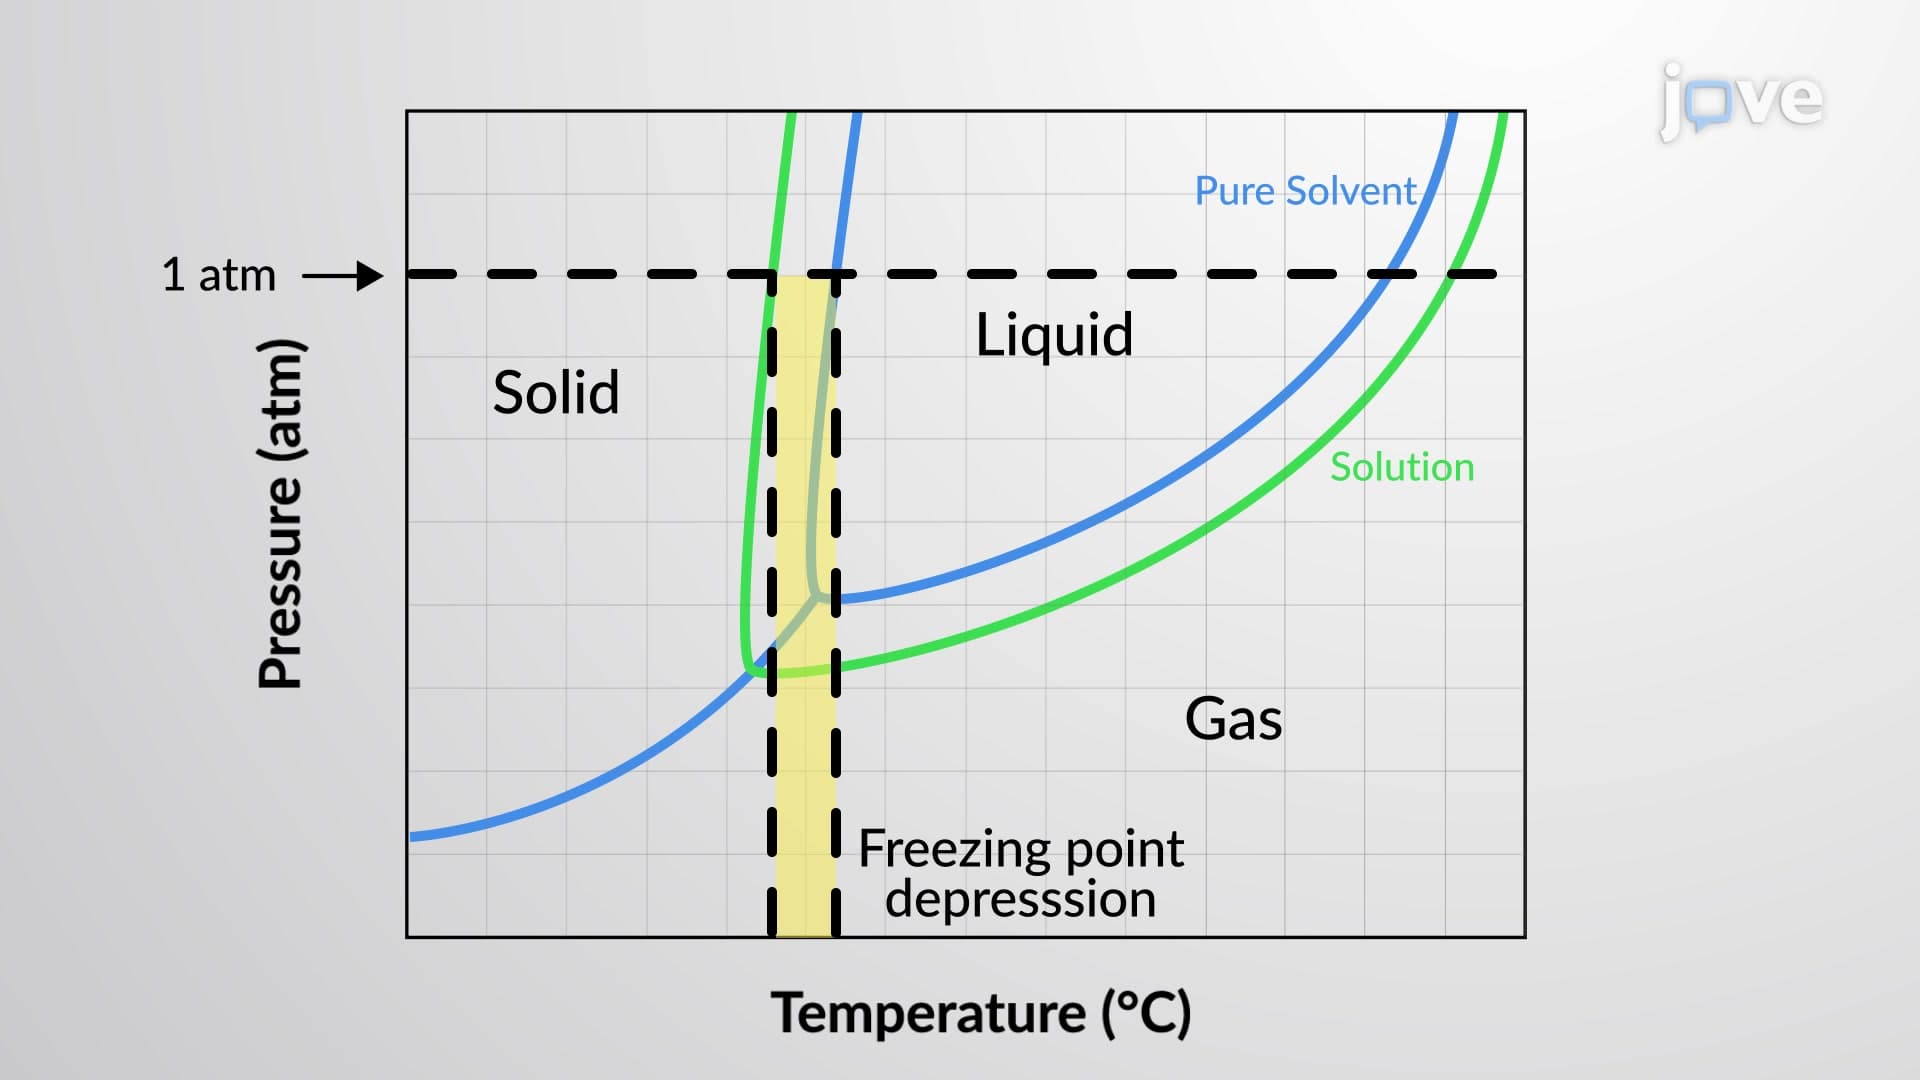
Freezing Point Depression and Boiling Point Elevation
The boiling point of a liquid is the temperature at which its vapor pressure is equal to ambient atmospheric pressure. Since the vapor pressure of a solution is lowered due to the presence of nonvolatile solutes, it stands to reason that the solution’s boiling point will subsequently be increased. Vapor pressure increases with temperature, and so a solution will require a higher temperature than will pure solvent to achieve any given vapor pressure, including one...
 01:25
Benefits of Self-Esteem
 01:03
Nursing Interventions I: Taxonomy of Nursing Interventions
A nursing intervention is a treatment or action based on scientific concepts and knowledge from the nursing, behavioral, and physical sciences. Identifying and prioritizing nursing interventions based on the desired outcome...
 01:29
Nursing Interventions II: Selecting and Classifying the Nursing Interventions
 01:18
Survival Curves
The Kaplan-Meier estimator is the most common method for constructing survival curves. This...