Related Experiment Video
Updated: Feb 8, 2026


Assessment of Bone Fracture Healing Using Micro-Computed Tomography
Published on: December 9, 2022
Comparison of Methods for Improving Fracture Risk Assessment in Diabetes: The Manitoba BMD Registry
William D Leslie1, Helena Johansson2,3, Eugene V McCloskey3
1Department of Internal Medicine, University of Manitoba, Winnipeg, Manitoba, Canada.

Abstract:
Type 2 diabetes is a risk factor for fracture independent of FRAX (fracture risk assessment) probability. We directly compared four proposed methods to improve the performance of FRAX for type 2 diabetes by: (1) including the rheumatoid arthritis (RA) input to FRAX; (2) making a trabecular bone score (TBS) adjustment to FRAX; (3) reducing the femoral neck T-score input to FRAX by 0.5 SD; and (4) increasing the age input to FRAX by 10 years. We examined major osteoporotic fractures (MOFs) and hip fractures (HFs) over a mean of 8.3 years observation among 44,543 women and men 40 years of age or older (4136 with diabetes) with baseline lumbar spine and hip DXA from 1999 through 2016. Controlled for unadjusted FRAX probability, diabetes was associated with an increased risk for MOFs and HFs. All four FRAX adjustments attenuated the effect of diabetes, but a residual effect of diabetes was seen on MOF risk after TBS adjustment, and on HF risk after the RA and TBS adjustments. Among those with diabetes, unadjusted FRAX risk underestimated MOF (observed/predicted ratio 1.15; 95% CI, 1.03 to 1.28), but this was no longer significant after applying the diabetes adjustments. HF risk was more severely underestimated (observed/predicted ratio 1.85; 95% CI, 1.51 to 2.20) and was only partially corrected with the diabetes adjustments (still significant for the RA and TBS adjustments). Among those with diabetes, there was moderate reclassification based upon a fixed MOF cut-off of 20% (4.1% to 7.1%) or fixed HF cut-off of 3% (5.7% to 16.5%). Net reclassification improvement increased for MOF with each of the diabetes adjustments (range 3.9% to 5.6% in the diabetes subgroup). In conclusion, each of the proposed methods for addressing limitations in the ability of FRAX to assess fracture risk in individuals with diabetes was found to improve performance, though no single method was optimal in all settings. © 2018 American Society for Bone and Mineral Research.


Related Concept Videos
 02:57
The Sense of Self: Reflected Self-Appraisal and Social Comparison
 01:17
Design Example: Analyzing Capacity Contours for Flood Risk Assessment
 01:08
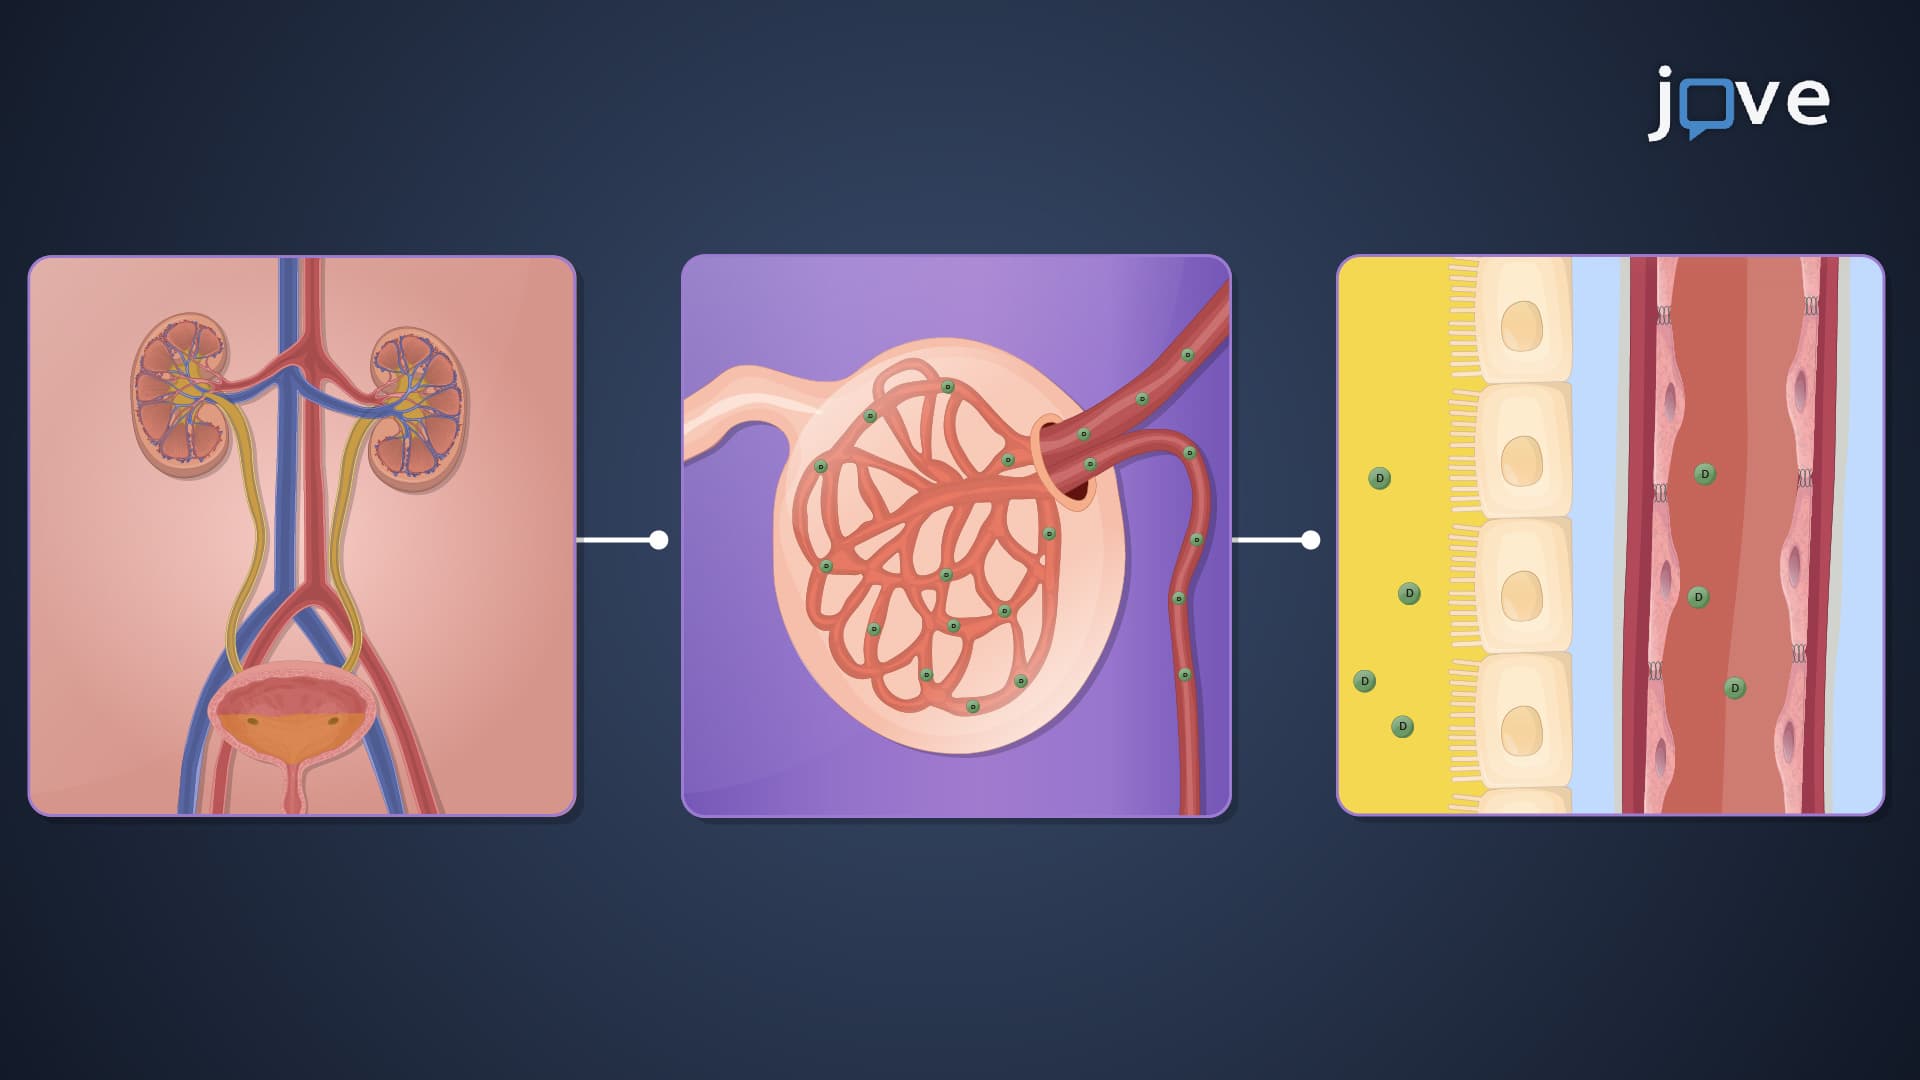
Renal Drug Clearance: Comparison Between Renal Excretion Methods
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...
 01:12
Relative Risk
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility,...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...