Related Experiment Video
Updated: Feb 8, 2026


Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Short-term outcomes of transanal completion total mesorectal excision (cTaTME) for rectal cancer: a case-matched
T W A Koedam1,2, M Veltcamp Helbach3, M Penna4
1Department of Surgery, VU University Medical Center, Boelelaan 1117, 1081 HV, Amsterdam, The Netherlands. t.koedam@vumc.nl.

Background:
Local excision of early rectal tumors as a rectal preserving treatment is gaining popularity, especially since bowel cancer screening programs result in a shift towards the diagnosis of early stage rectal cancers. However, unfavorable histological features predicting high risk for recurrence within the "big biopsy" may mandate completion total mesorectal excision (cTME). Completion surgery is associated with higher morbidity, poorer specimen quality, and less favorable oncological outcomes compared to primary TME. Transanal approach potentially improves outcome of completion surgery for rectal cancer. The aim of this study was to compare radical completion surgery after local excision for rectal cancer by the transanal approach (cTaTME) with conventional abdominal approach (cTME).
Methods:
All consecutive patients who underwent cTaTME for rectal cancer between 2012 and 2017 were case-matched with cTME patients, according to gender, tumor height, preoperative radiotherapy, and tumor stage. Surgical, pathological, and short-term postoperative outcomes were evaluated.
Results:
In total, 25 patients underwent completion TaTME and were matched with 25 patients after cTME. Median time from local excision to completion surgery was 9 weeks in both groups. In the cTaTME and cTME groups, perforation of the rectum occurred in 4 and 28% of patients, respectively (p = 0.049), leading to poor specimen quality in these patients. Number of harvested lymph nodes was higher after cTaTME (median 15; range 7-47) than after cTME (median 10; range 0-17). No significant difference was found in end colostomy rate between the two groups. Major 30-day morbidity (Clavien-Dindo≥ III) was 20 and 32%, respectively (p = 0.321). Hospital stay was significantly longer after cTME.
Conclusion:
TaTME after full-thickness excision is a promising technique with a significantly lower risk of perforation of the rectum and better specimen quality compared to conventional completion TME.
Related Concept Videos
 01:08
Nucleotide Excision Repair
 01:38
Nucleotide Excision Repair
Cells are regularly exposed to mutagens—factors in the environment that can damage DNA and generate mutations. UV radiation is one of the most common mutagens and is estimated to introduce a significant number of changes in DNA. These include bends or kinks in the structure, which can block DNA replication or transcription. If these errors are not fixed, the damage can cause mutations, which in turn can result in cancer or disease depending on which sequences are...
 01:17
Sign Test for Matched Pairs
To conduct the sign test, we first calculate the differences in...
 01:54
Base Excision Repair
The first step of...
 01:27
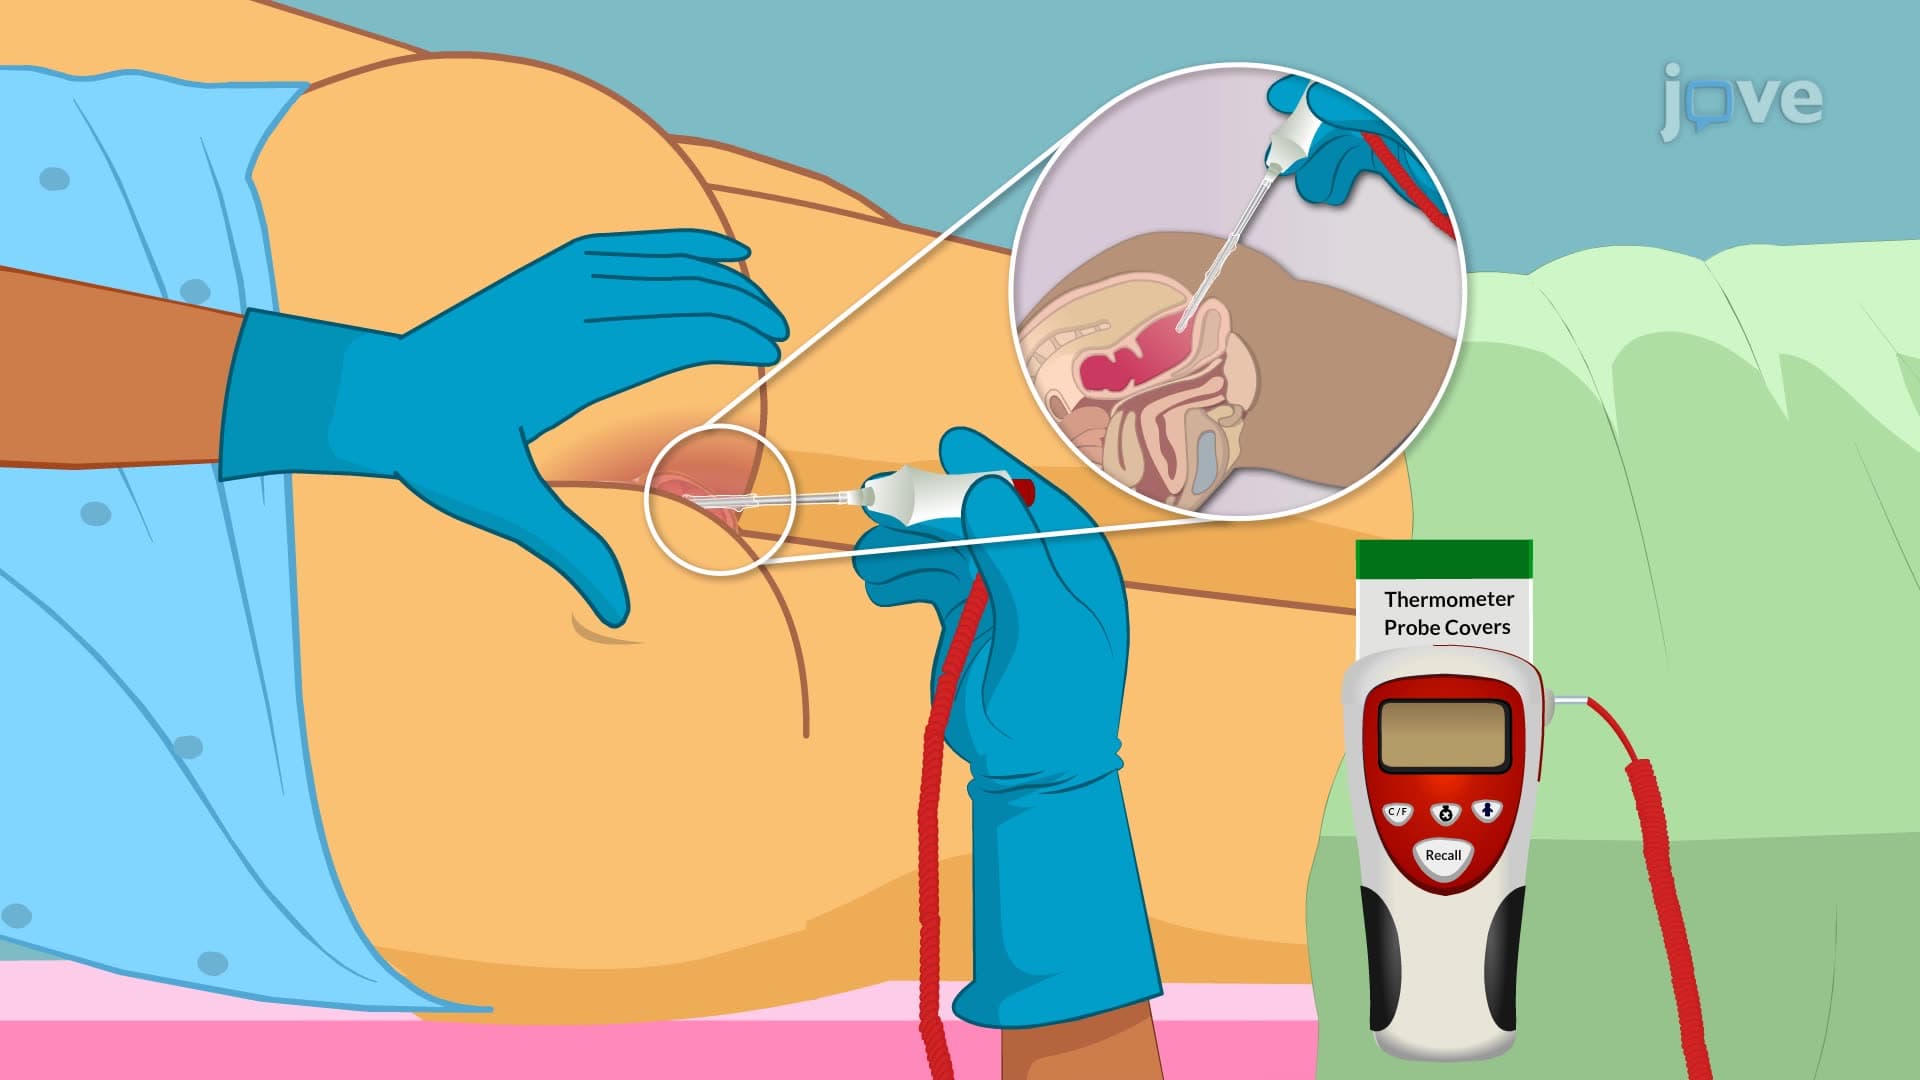
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 02:24
Predicting Reaction Outcomes