Correlation of anteroseptal ST elevation with myocardial infarction territories through cardiovascular magnetic resonance imaging
Related Experiment Video
Updated: Feb 7, 2026

Postconditioning with Lactate-enriched Blood for Cardioprotection in ST-segment Elevation Myocardial Infarction
Published on: May 28, 2019
Joseph Allencherril1, Yama Fakhri2, Henrik Engblom3
1Section of Cardiology, Baylor College of Medicine, One Baylor Plaza, Houston, TX, USA.

Insights
ST elevation myocardial infarction (STEMI) in leads V1-V4 predominantly affects the apical region, not the basal anteroseptum. This finding suggests "anteroapical" infarction is a more accurate term for these STEMI cases.
Area of Science:
- Cardiology
- Medical Imaging
- Myocardial Infarction
Background:
- Anteroseptal ST elevation myocardial infarction (STEMI) is traditionally linked to electrocardiogram (ECG) findings in leads V1-V3, often implicating the basal anteroseptal myocardial segment.
- Existing literature suggests Q waves in leads V1-V4 may indicate apical infarction, but specific evaluations of anteroseptal ST elevation territories are lacking.
- This study investigates the myocardium at risk (MaR) distribution in STEMI patients with ST elevation (STE) limited to V1-V4 versus more extensive STE (V1-V6).
Purpose of the Study:
- To compare the distribution of myocardium at risk (MaR) in STEMI patients with ST elevation (STE) limited to leads V1-V4 versus those with STE in leads V1-V6.
- To determine the specific myocardial segments affected in anteroseptal STEMI based on ECG lead involvement.
- To refine the terminology used to describe STEMI based on the affected myocardial regions.
Main Methods:
- Patients from the MITOCARE study with a first acute STEMI and new ST elevation (STE) in contiguous anterior leads (V1-V6) were identified.
- Cardiac magnetic resonance (CMR) imaging was performed three to five days after the acute infarction.
- The distribution of myocardium at risk (MaR) was assessed in specific myocardial segments for patients categorized by STE lead involvement (V1-V4 vs. V1-V6).
Main Results:
- In STEMI patients with STE in leads V1-V4 (n=20), significant myocardium at risk (MaR > 50%) was observed predominantly in apical anterior (100%), apical septal (90%), and apex (90%) segments.
- Basal anteroseptal segments showed minimal MaR (>50%) in 0% of patients with STE in V1-V4.
- STEMI patients with more extensive STE in leads V1-V6 (n=12) showed similar high MaR in apical segments but slightly higher involvement in the basal anteroseptum (8%).
Conclusions:
- Acute STEMI with ST elevation in leads V1-V4 primarily involves apical myocardial territories, with rare involvement of the basal anteroseptum.
- The study found no evidence supporting the existence of isolated basal anteroseptal or septal STEMI based on the evaluated ECG criteria.
- 'Anteroapical' infarction is proposed as a more accurate descriptor than 'anteroseptal' infarction for STEMI cases presenting with ST elevation in leads V1-V4.
Background:
Anteroseptal ST elevation myocardial infarction (STEMI) is traditionally defined on the electrocardiogram (ECG) by ST elevation (STE) in leads V1-V3, with or without involvement of lead V4. It is commonly taught that such infarcts affect the basal anteroseptal myocardial segment. While there are suggestions in the literature that Q waves limited to V1-V4 represent predominantly apical infarction, none have evaluated anteroseptal ST elevation territories. We compared the distribution of the myocardium at risk (MaR) in STEMI patients presenting with STE limited to V1-V4 and those with more extensive STE (V1-V6).
Methods:
We identified patients in the MITOCARE study presenting with a first acute STEMI and new STE in at least two contiguous anterior leads from V1 to V6. Patients underwent cardiac magnetic resonance (CMR) imaging three to five days after acute infarction.
Results:
Thirty-two patients met inclusion criteria. In patients with STE in V1-V4 (n = 20), myocardium at risk (MaR) > 50% was seen in 0%, 85%, 75%, 100%, and 90% in the basal anteroseptal, mid anteroseptal, apical anterior, apical septal segments, and apex, respectively. The group with STE in V1-V6 (n = 12), MaR > 50% was seen in 8%, 83%, 83%, 92%, and 83% of the same segments.
Conclusions:
Patients with acute STEMI and STE in leads V1-V4, exhibit MaR in predominantly apical territories and rarely in the basal anteroseptum. We found no evidence to support existence of isolated basal anteroseptal or septal STEMI. "Anteroapical" infarction is a more precise description than "anteroseptal" infarction for acute STEMI patients exhibiting STE in V1-V4.
More Related Videos
 04:41
Digital PCR for Quantifying Circulating MicroRNAs in Acute Myocardial Infarction and Cardiovascular Disease
Published on: July 3, 2018
 11:13
Quantification of Mouse Heart Left Ventricular Function, Myocardial Strain, and Hemodynamic Forces by Cardiovascular Magnetic Resonance Imaging
Published on: May 24, 2021
Related Concept Videos
 01:24
Magnetic Resonance Imaging
 01:27
Imaging Studies IV: Magnetic Resonance Imaging
 01:05
Atomic Nuclei: Magnetic Resonance
 01:17
Imaging Studies for Cardiovascular System I:Echocardiography
Indications: Echocardiography is utilized to diagnose heart failure, valve disorders, and myocardial infarction. It also assesses cardiac structures' size, shape, and motion,...
 03:12
Freezing Point Depression and Boiling Point Elevation
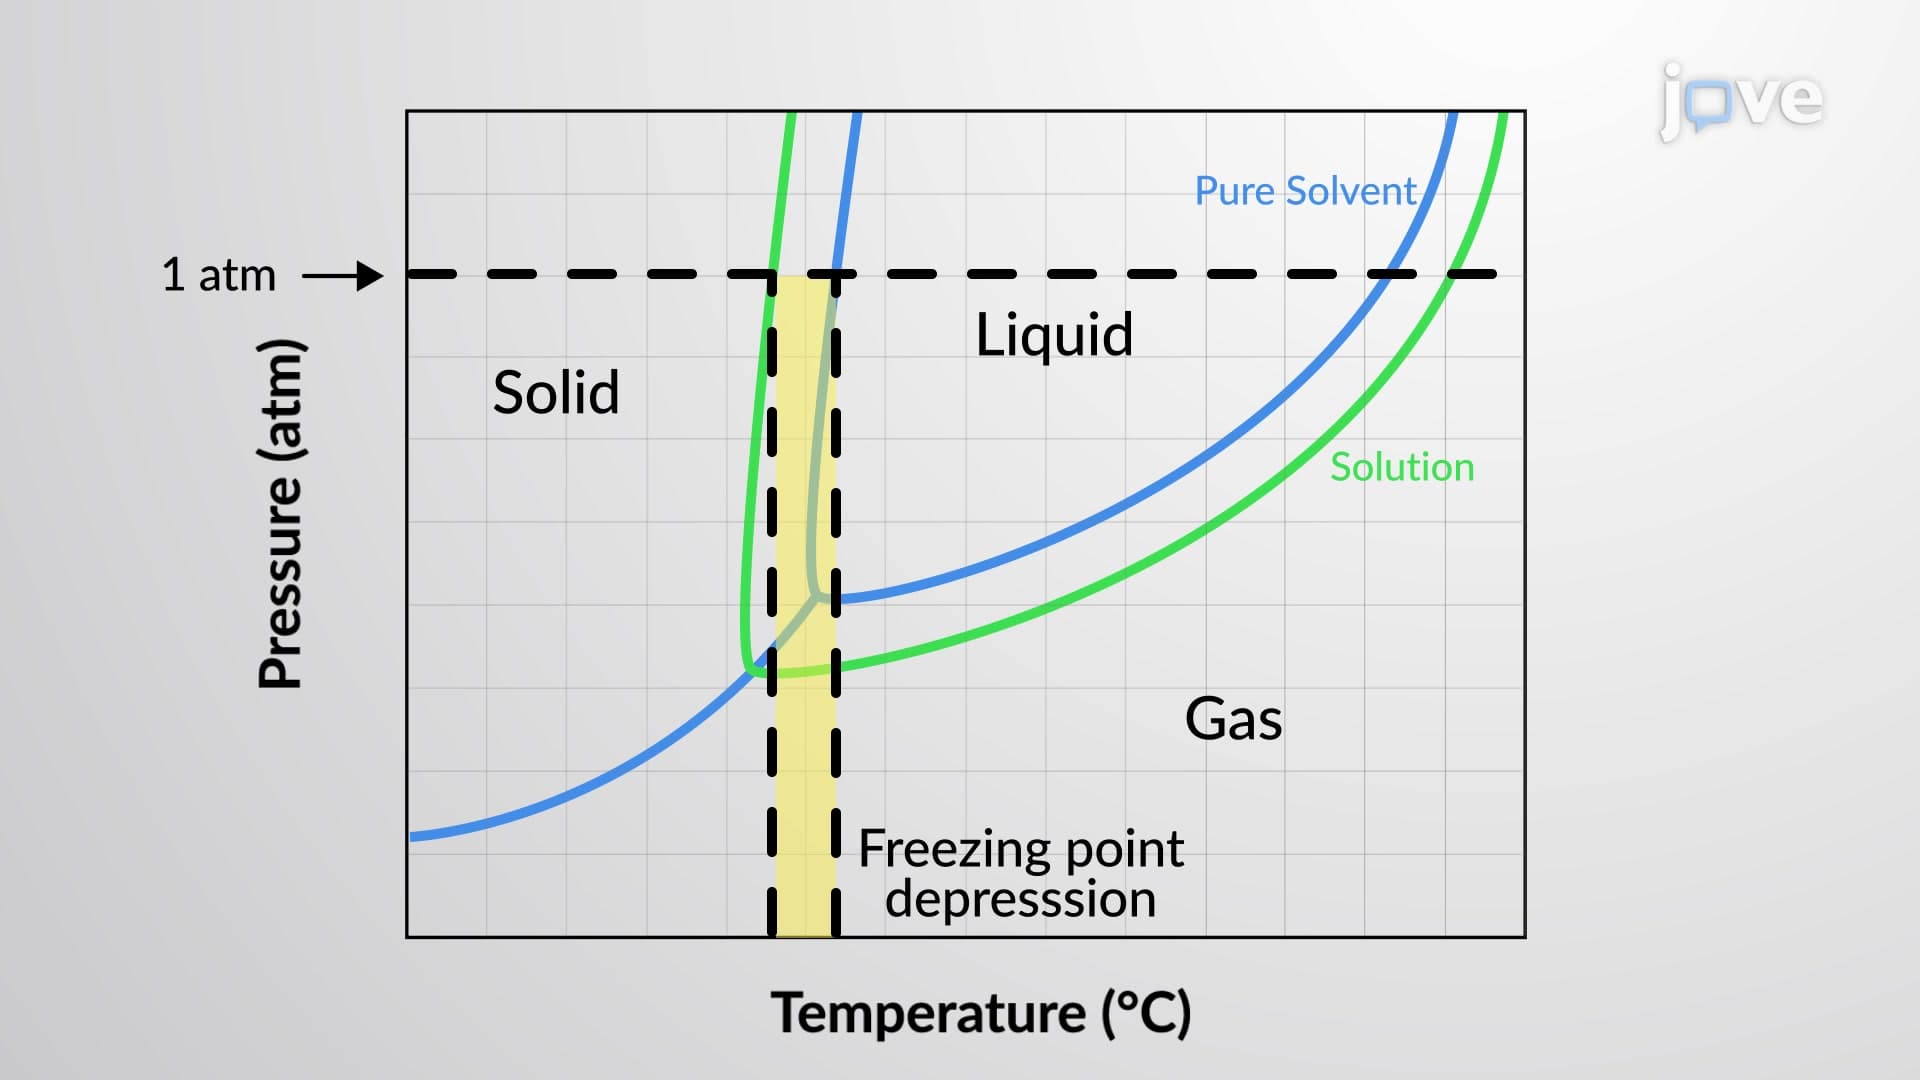
The boiling point of a liquid is the temperature at which its vapor pressure is equal to ambient atmospheric pressure. Since the vapor pressure of a solution is lowered due to the presence of nonvolatile solutes, it stands to reason that the solution’s boiling point will subsequently be increased. Vapor pressure increases with temperature, and so a solution will require a higher temperature than will pure solvent to achieve any given vapor pressure, including one...
 01:28
Imaging Studies for Cardiovascular System V: CT