Related Experiment Video
Updated: Oct 25, 2026
Confirmation of Myocardial Ischemia and Reperfusion Injury in Mice Using Surface Pad Electrocardiography
Published on: November 24, 2016
Pathological Q waves in anterior myocardial infarction: A marker of infarct extent rather than location
Emre K Aslanger1, Gamze Gençol Akçay2, Şeyma Acaroğlu2
1Health Sciences University, Başakşehir Pine and Sakura City Hospital, Department of Cardiology, Istanbul, Türkiye.

Background:
Pathological Q waves have traditionally been used to localize myocardial infarction (MI), although their anatomical specificity remains uncertain. We investigated the relationship between Q-wave distribution and cardiac magnetic resonance (CMR)-defined myocardial infarct burden after anterior MI.
Methods:
We analyzed 102 patients with first anterior ST-elevation MI. Individual Q waves and established anterior Q wave patterns were compared with segmental late gadolinium enhancement (LGE).
Results:
Individual Q waves showed broad, overlapping relationships with LGE-defined infarct burden; after false-discovery-rate correction, only Q waves in V1 remained significantly associated with basal anteroseptal and apical septal LGE-defined infarct burden. Established Q wave patterns showed substantial anatomical overlap but a clear gradient in infarct burden. Across the four-level classification based on the most lateral precordial lead with a pathological Q wave (none, V1-V2 only, up to V3, or extending to V4-V6), infarct size increased from 6% to 14%, 17%, and 18% (P for trend<0.001), mid-ventricular LGE burden from 75 to 125, 150, and 175 percentage-points (P < 0.001), and apical LGE burden from 100 to 125, 200, and 200 percentage-points (P < 0.001). LVEF declined across categories (P for trend = 0.004).
Conclusions:
In anterior MI, pathological Q wave distribution showed limited correspondence with discrete myocardial territories but was associated with increasing infarct size and greater mid-apical LGE-defined infarct burden, suggesting that Q-wave distribution may be better interpreted as a marker of infarct extent than as a geographical map of infarct location. External validation of this simplified extent-based classification is warranted.


Related Concept Videos
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:27
Myocarditis II: Clinical Features and Diagnostic Tests
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:30
Acute Coronary Syndrome I: Introduction
 01:28
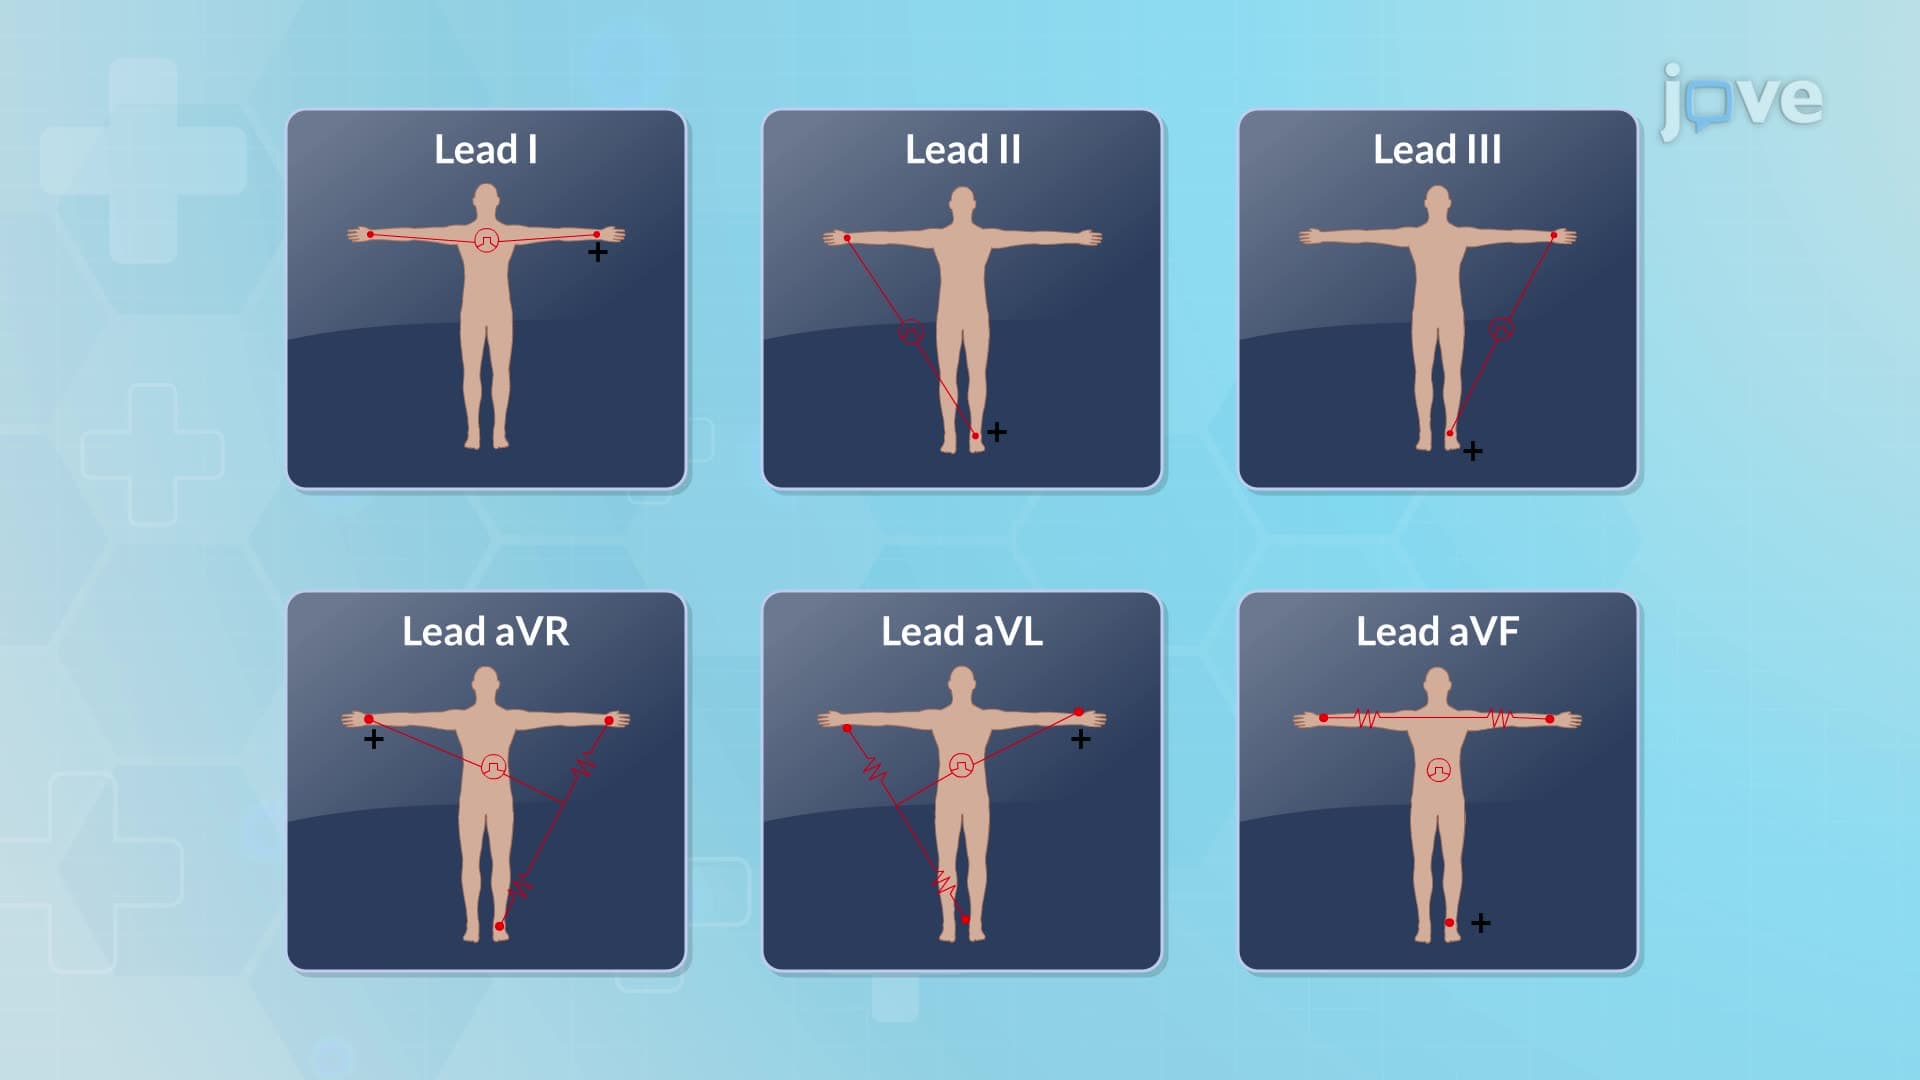
Electrocardiogram Fundamentals
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin to...