Related Experiment Video
Updated: Feb 7, 2026
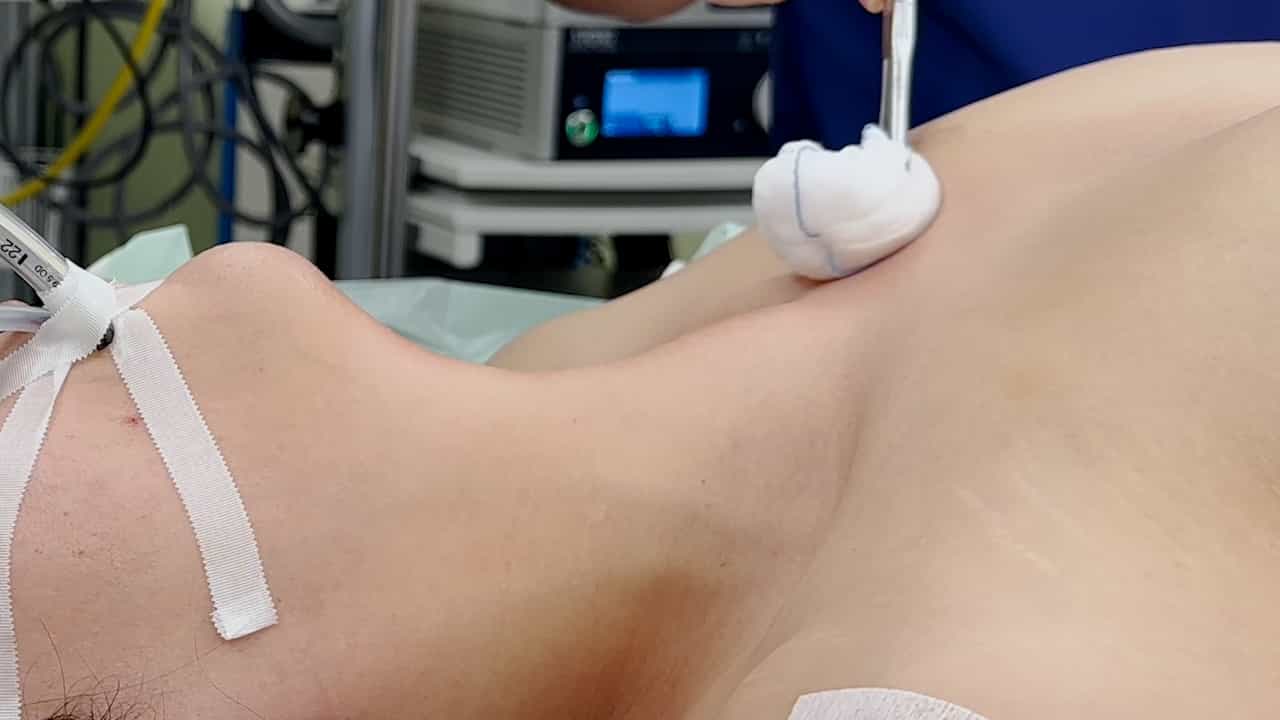

Minimal Invasive Resection of Large Retrosternal Thyroid Goiter
Published on: September 20, 2024
Management of retrosternal goiter: Retrospective study of 72 patients at two secondary care centers
Wai Keat Wong1, Subhaschandra Shetty1, Randall P Morton2
1Department of Otolaryngology, Head and Neck Surgery, Manukau Surgery Center, Counties Manukau District Health Board, Auckland, New Zealand; Department of Otolaryngology, Head and Neck Surgery, Whangarei Base Hospital, Northland District Health Board, Whangarei, New Zealand.

Objective:
Data pertaining to the outcomes of retrosternal goiter surgeries performed at secondary care centers, where thoracic surgery expertise is not readily available, is infrequently reported. Careful patient selection is crucial to avoid an unexpected need for a sternotomy during surgery. We sought to evaluate the surgical management of patients with retrosternal goiters treated at two secondary care centers.
Methods:
Retrospective review of clinical records and computed tomographic (CT) scans of 557 patients who underwent thyroid surgery at the Departments of Otolaryngology, Head and Neck Surgery of Manukau Surgery Center and Whangarei Base Hospital. Inclusion criterion was extension of goiter below the plane of the thoracic inlet on CT scan. Clinicopathologic features and surgical outcomes were recorded.
Results:
The prevalence of retrosternal goiter was 72 of 557 patients (12.9%). All patients in this series underwent thyroidectomy transcervically. Dyspnea was present in 48 patients (66.7%). On preoperative CT scans, the goiter was noted to extend beyond the aortic arch in seven patients (9.7%), tracheal bifurcation in five patients (6.9%) and posterior mediastinum in 15 patients (20.8%). Malignancy was diagnosed in eight patients (11.1%) histologically. Postoperatively, vocal cord paralysis was temporary in 5 patients (6.9%) and permanent in 1 patient (1.4%). Hypocalcaemia was transient in 10 patients (13.9%). No permanent hypocalcemia, tracheomalacia, postoperative hematoma or patient death was reported. During the study period, 4 patients were encountered in the outpatients setting whereby the evaluation of their CT imaging demonstrated features deemed to be at high risk of requiring a sternotomy: primary mediastinal goiter (n=2) and inferior extent of goiter to the level of right atrium (n=2). These patients were pre-emptively referred to a tertiary center where thoracic surgery service was available and their data was reported separately.
Conclusion:
With careful patient selection, the majority of retrosternal goiter can be resected transcervically with minimal morbidities. Preoperative CT scan yielded useful surgical information; in the presence of primary mediastinal goiter or inferior extent of goiter to the level of the right atrium, surgery should be planned in a tertiary center where thoracic surgeon is available.


Related Concept Videos
 01:13
Patient-centered Care
 01:30
Specialized Care Centers and Settings-I
Daycare centers
They provide several functions. Some facilities care for healthy newborns and children whose parents work, while others are medically focused and care for...
 01:30
Specialized Care Centers and Settings-II
Rural health centers are specialized care facilities in remote locations with very few medical personnel. The primary care providers who run the centers are mostly Registered Nurse Practitioners. Here, emergency treatment is provided to critically ill or injured patients before they are transferred to the closest hospital. Fortunately, due to advancement in technology, many rural healthcare facilities and professionals have easy access to diagnostic and treatment...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 03:02
Primary and Secondary Growth in Roots and Shoots
 01:55
Secondary Active Transport