

Treatment Strategy for Newly Diagnosed T1 High-grade Bladder Urothelial Carcinoma: New Insights and Updated
Zachary Klaassen1, Ashish M Kamat2, Wassim Kassouf3
1Division of Urology, Department of Surgery, University Health Network, Princess Margaret Cancer Centre, University of Toronto, Toronto, ON, Canada.

Context:
High-grade T1 (T1HG) bladder cancer (BCa) has a very high likelihood of disease recurrence and progression to muscle invasion. Radical cystectomy is considered the best chance at cure, albeit with a high risk of morbidity, and is overtreatment for some patients. Treatment with bacillus Calmette-Guerin (BCG) allows bladder preservation but may risk disease progression.
Objective:
To systematically review the current literature on the management of T1HG BCa and provide updated treatment recommendations.
Evidence Acquisition:
Medline, EMBASE, and Epub Ahead of Print databases were searched in November 2017 to identify observational cohort studies and controlled trials, between 1946 and 2017, associated with diagnosis, treatment, and prognosis of T1HG BCa.
Evidence Synthesis:
Clinical understaging and/or persistence of disease is not uncommon at initial transurethral resection (TUR); thus, a second re-TUR is recommended for cases with T1HG BCa. Patients electing a bladder preservation approach should undergo induction BCG therapy followed by a maintenance schedule, while patients with several high-risk features should consider immediate cystectomy and those with BCG-refractory or BCG-unresponsive disease should be considered for early cystectomy. Current phase I/II clinical trials for T1HG patients may offer future bladder preservation therapy approaches.
Conclusions:
T1HG tumours are heterogeneous in nature and challenging to treat. Bladder preservation with BCG induction and maintenance, or radical cystectomy is the current standard treatment modality of choice for these tumours. Promising therapies for BCG-unresponsive disease are currently under investigation.
Patient Summary:
Patients with high-grade T1 bladder cancer are at a high risk of tumour recurrence and progression, requiring more aggressive treatment such as bladder removal. Bladder preservation therapies are available (and new therapies are being tested in clinical trials); however, patients should be aware that currently bladder removal is considered the best opportunity for cancer cure.
More Related Videos
 09:16
Ex Vivo Organoid Model of Adenovirus-Cre Mediated Gene Deletions in Mouse Urothelial Cells
Published on: May 5, 2022
 11:02
Induction of Invasive Transitional Cell Bladder Carcinoma in Immune Intact Human MUC1 Transgenic Mice: A Model for Immunotherapy Development
Published on: October 30, 2013
Related Concept Videos
 01:24
Treatment Strategies for Psychological Disorders
Psychological therapies focus on modifying emotions, thoughts, and behaviors through talking, interpreting, listening, rewarding, challenging, and modeling. Clinical psychologists, counselors, and social workers commonly practice psychotherapy. Clinical...
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and...
 01:19
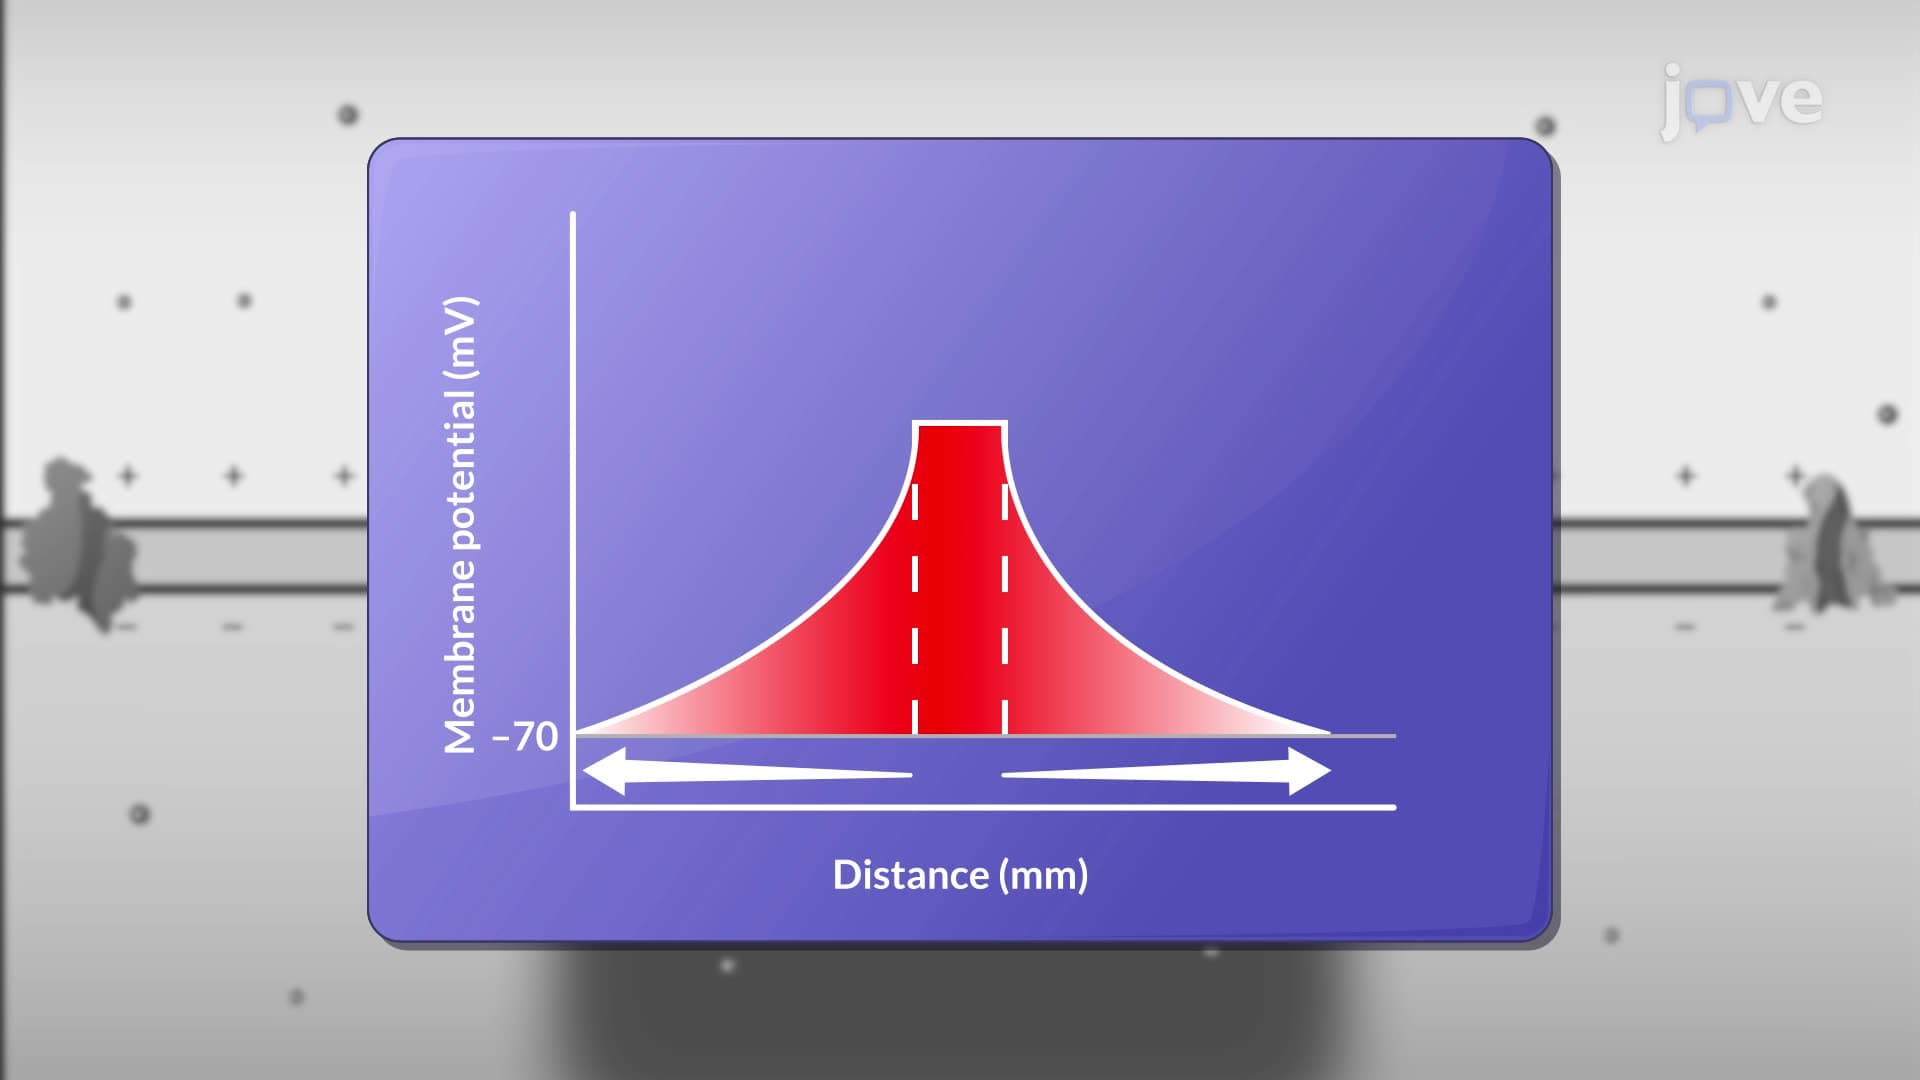
Graded Potential
Graded potentials fall into two categories: depolarizing and hyperpolarizing. Depolarizing graded potentials typically occur when sodium (Na+) or...
 01:23
Urinary Bladder
In males, the bladder is situated in front of the rectum, while in females, it is positioned anterior to the vagina and uterus. The bladder floor contains an inverted triangular area called the trigone, defined by the two ureteric...
 01:15
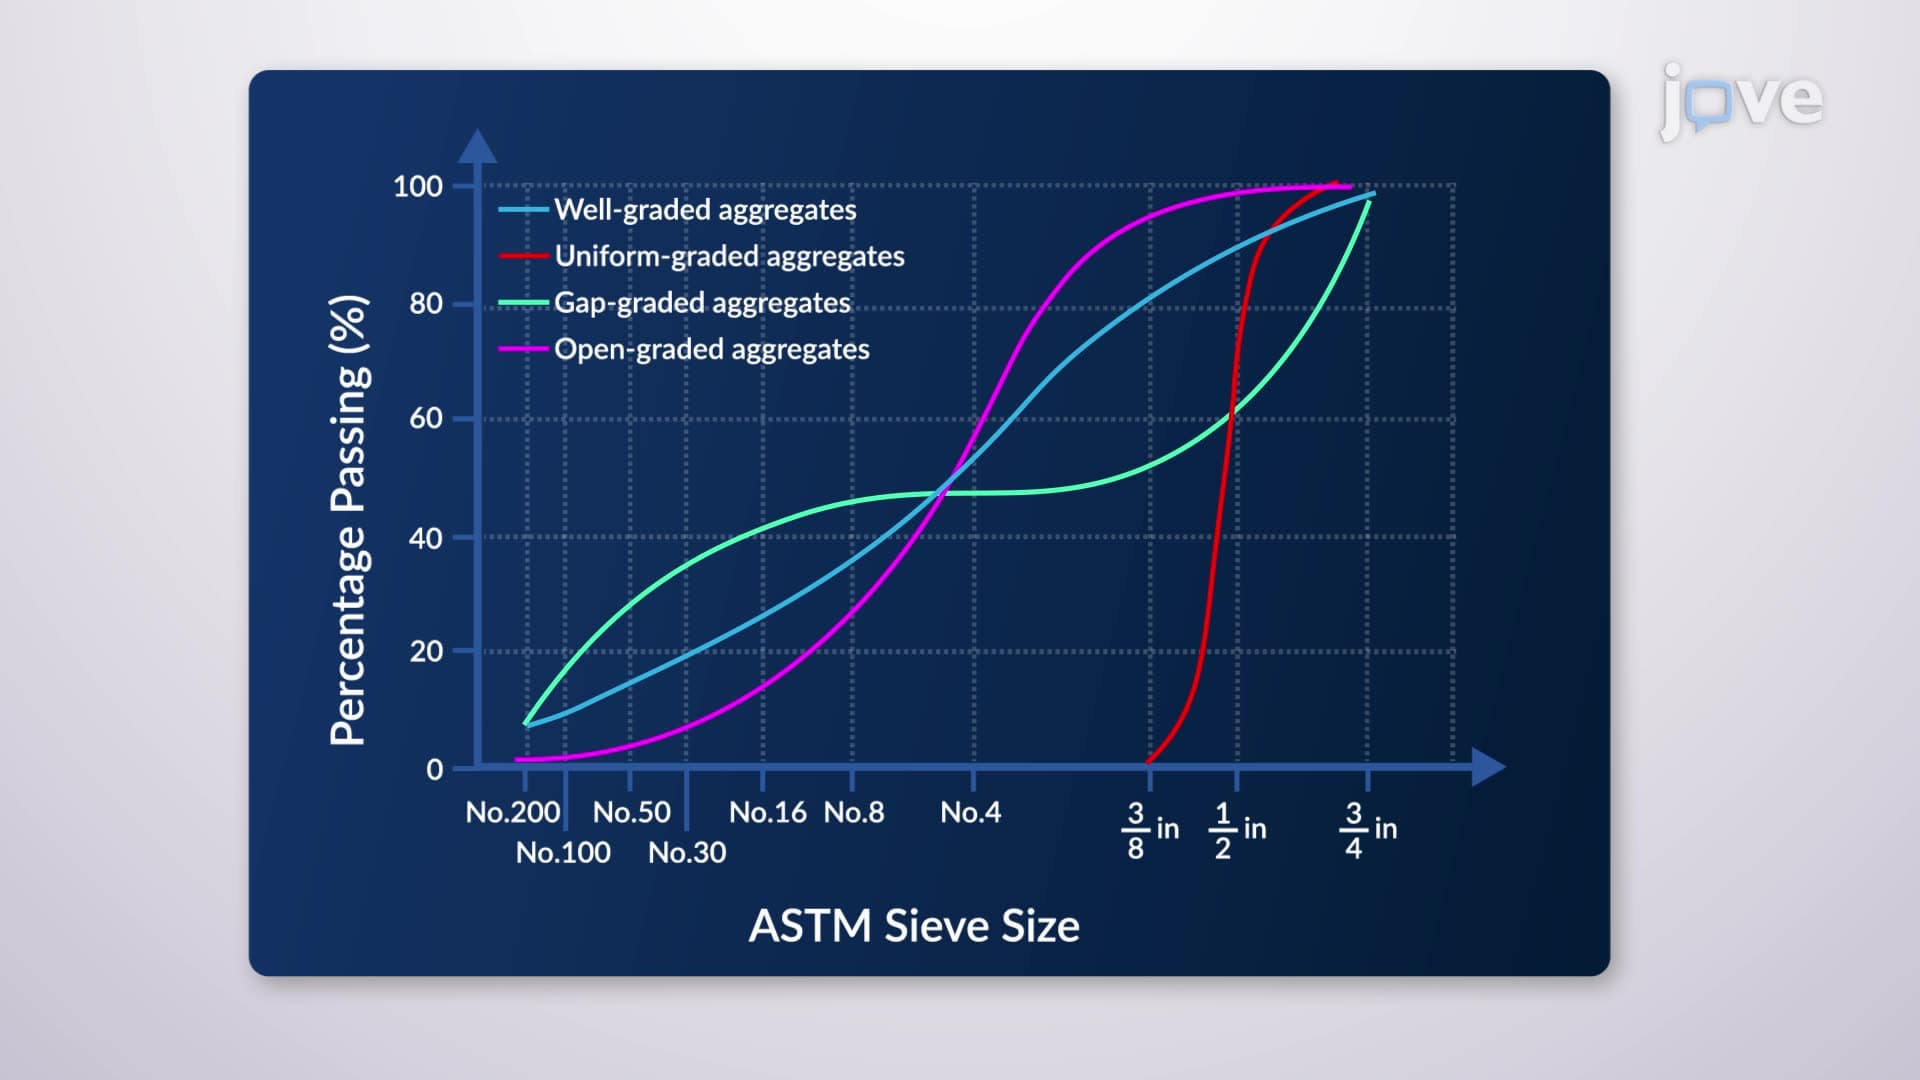
Types of Aggregate Grading
Well-graded aggregates include a complete range of necessary size fractions that fit together to create a dense matrix with minimal voids, represented by a smooth, continuous gradation curve. This type of grading ensures good...
 01:19
Sieve Analysis and Grading Curves