Related Experiment Video
Updated: Feb 7, 2026

Nerve Ultrasound Protocol to Detect Dysimmune Neuropathies
Published on: October 7, 2021
MR neurography biomarkers to characterize peripheral neuropathy in AL amyloidosis
Jennifer Kollmer1, Markus Weiler2, Jan Purrucker2
1From the Department of Neuroradiology (J.K., S.H., T.H., M.P., M.B.), Amyloidosis Center Heidelberg (J.K., M.W., J.P., S.O.S., E.H., C.K., U.H.), Department of Neurology (M.W., J.P., E.H.), Division of Experimental Radiology, Department of Neuroradiology (S.H.), and Medical Department V (S.O.S., C.K., U.H.), Heidelberg University Hospital, Germany; Department of Neurology (J.M.H.), University of Michigan, Ann Arbor; and Department of Neuroradiology (M.P.), Würzburg University Hospital, Germany. jennifer.kollmer@med.uni-heidelberg.de.

Objective:
To detect, localize, and quantify peripheral nerve lesions in amyloid light chain (AL) amyloidosis by magnetic resonance neurography (MRN) in correlation with clinical and electrophysiologic findings.
Methods:
We prospectively examined 20 patients with AL-polyneuropathy (PNP) and 25 age- and sex-matched healthy volunteers. After detailed neurologic and electrophysiologic testing, the patient group was subdivided into mild and moderate PNP. MRN in a 3.0 tesla scanner with anatomical coverage from the lumbosacral plexus and proximal thigh down to the tibiotalar joint was performed by using T2-weighted and dual-echo 2-dimensional sequences with spectral fat saturation and a 3-dimensional, T2-weighted inversion recovery sequence. Besides evaluation of nerve T2-weighted signal, detailed quantification of nerve injury by morphometric (nerve caliber) and microstructural MRN markers (proton spin density, T2 relaxation time) was conducted.
Results:
Nerve T2-weighted signal increase correlated with disease severity: moderate (420.2 ± 60.1) vs mild AL-PNP (307.2 ± 17.9; p = 0.0003) vs controls (207.0 ± 6.4; p < 0.0001). Proton spin density was also higher in moderate (tibial: 525.5 ± 53.0; peroneal: 553.6 ± 64.5; sural: 492.0 ± 56.6) and mild AL-PNP (tibial: 431.6 ± 22.0; peroneal: 457.6 ± 21.7; sural: 404.8 ± 25.2) vs controls (tibial: 310.5 ± 14.1; peroneal: 313.6 ± 11.6; sural: 261.7 ± 11.0; p < 0.0001 for all nerves). T2 relaxation time was elevated in moderate AL-PNP only (tibial: p = 0.0106; peroneal: p = 0.0070; sural: p = 0.0190). Tibial nerve caliber was higher in moderate (58.0 ± 8.8 mm3) vs mild AL-PNP (46.5 ± 2.5 mm3; p = 0.008) vs controls (39.1 ± 1.2 mm3; p < 0.0001).
Conclusions:
MRN detects and quantifies peripheral nerve injury in AL-PNP in vivo with high sensitivity and in close correlation with the clinical stage. Quantitative parameters are feasible new imaging biomarkers for the detection of early AL-PNP and might help to monitor microstructural nerve tissue changes under treatment.
Related Concept Videos
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:24
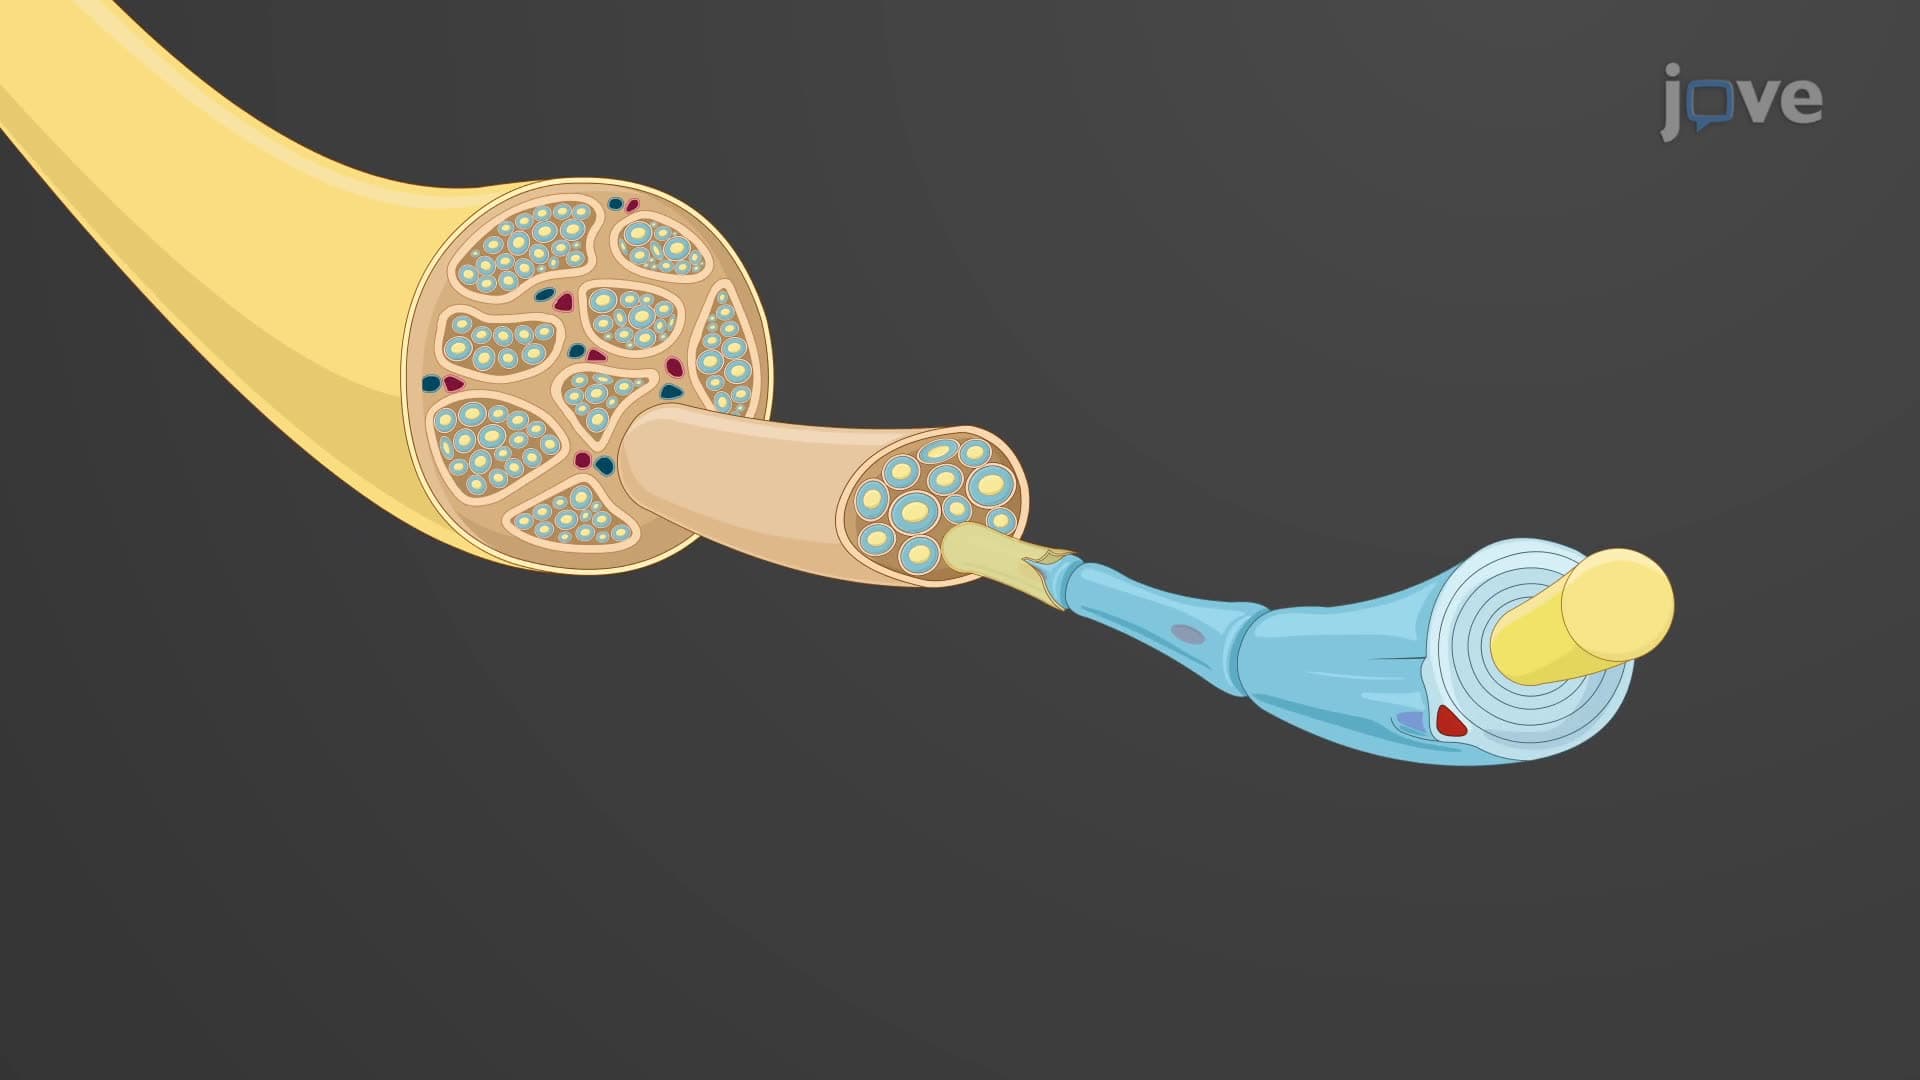
Peripheral Nervous System: Ganglia and Nerves
Nerves
The nerve is a bundle of axons that serves as the communication highway in the PNS. Each nerve is ensheathed in a protective layer of connective tissue called the epineurium. This outermost layer safeguards the nerve and supports the...
 01:30
Peripheral Artery Disease I: Introduction
 01:09
Peripherally and Centrally Acting Muscle Relaxants: A Comparison
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic...
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management