Related Experiment Video
Updated: Feb 7, 2026


Sex Differences in Mouse Hippocampal Astrocytes after In-Vitro Ischemia
Published on: October 25, 2016
Sex Differences in the Coronary System
1Heart and Vascular Center; Noninvasive Cardiovascular Imaging Program, Departments of Medicine (Cardiology) and Radiology (Nuclear Medicine and Molecular Imaging), Brigham and Women's Hospital, Harvard Medical School, Boston, MA, USA. vtaqueti@bwh.harvard.edu.

Insights
Ischemic heart disease (IHD) presents differently in women and men, often with nonobstructive coronary artery disease (CAD) and microvascular dysfunction in women. Understanding these sex differences is crucial for equitable cardiovascular care.
Area of Science:
- Cardiovascular Medicine
- Cardiology
- Sex Differences in Health
Background:
- Cardiovascular disease is a leading cause of death globally.
- Ischemic heart disease (IHD) manifestations, diagnosis, and outcomes differ between women and men.
- Traditional focus on obstructive coronary artery disease (CAD) inadequately explains IHD in women.
Purpose of the Study:
- To review sex differences in coronary circulation and IHD pathophysiology.
- To highlight the prevalence of nonobstructive CAD and microvascular dysfunction in women.
- To emphasize the need for research beyond obstructive CAD for equitable cardiovascular care.
Main Methods:
- State-of-the-art review of existing literature on sex differences in IHD.
- Analysis of pathophysiological processes contributing to IHD phenotypes in women and men.
- Examination of coronary circulation, cardiomyocyte function, and shear stress differences.
Main Results:
- Women exhibit higher symptom burden and comorbidities, with worse outcomes despite less obstructive CAD.
- Symptomatic women more frequently present with nonobstructive CAD and coronary microvascular dysfunction.
- Smaller coronary arteries and altered shear stress in women may contribute to diffuse CAD patterns.
Conclusions:
- IHD pathophysiology extends beyond obstructive CAD, particularly in women.
- Coronary microvascular dysfunction is a significant factor in IHD, especially in women.
- Further research into biological and environmental determinants is essential for sex-specific cardiovascular care.
Abstract:
Cardiovascular disease remains the leading cause of morbidity and mortality for both women and men. Emerging evidence supports that ischemic heart disease (IHD) may manifest differently in women and men, in ways ranging from the clinical presentation, diagnosis, and management of disease to the basic biology and biomechanics of cardiomyocyte function and the coronary circulation. Women consistently present with a higher burden of symptoms and comorbidities as compared with men and experience worse outcomes. These data have proved perplexing given the decreased likelihood of women to demonstrate obstructive coronary artery disease (CAD) on coronary angiography. Reported sex differences have long been influenced by the practice of defining heart disease primarily as obstructive CAD, but obstructive plaque is now recognized as neither necessary nor sufficient to explain symptoms of IHD, and it is no longer adequate to tailor diagnostic and treatment strategies only to this subset of patients. To date, women remain underrepresented in guideline-changing heart disease research and trials, creating important limitations in the evidence base for cardiovascular medicine. Smaller epicardial coronary arteries in women as compared to men, coupled with differences in shear stress and inflammatory mediators over the life span, may modify the development of CAD in susceptible patients into a diffuse pattern with more contribution from coronary vasomotor dysfunction than focal obstruction. Newer studies corroborate that symptomatic women are more likely than men to present with nonobstructive CAD and coronary microvascular dysfunction. When present, these processes increase cardiovascular risk in both women and men but may constitute an especially malignant phenotype in a subset of severely affected women, with implications for the management of not only CAD but also heart failure with preserved ejection fraction. This represents a state-of-the-art review of sex differences in the coronary system, with an eye toward how diverse pathophysiological processes may contribute to IHD phenotypes prevalent in women and men. Beyond providing women and men with equitable optimal care according to current paradigms, understanding the pathophysiology of IHD beyond a conventional focus on obstructive CAD is needed to address what is likely a combination of biological as well as environmental determinants of their prognosis.

Related Concept Videos
 01:43
Sex-linked Disorders
 01:21
Coronary Circulation
Coronary circulation begins at the base of the aorta, where two main arteries arise—the left and right coronary arteries. These arteries encircle the heart in the coronary sulcus and supply the...
 01:16
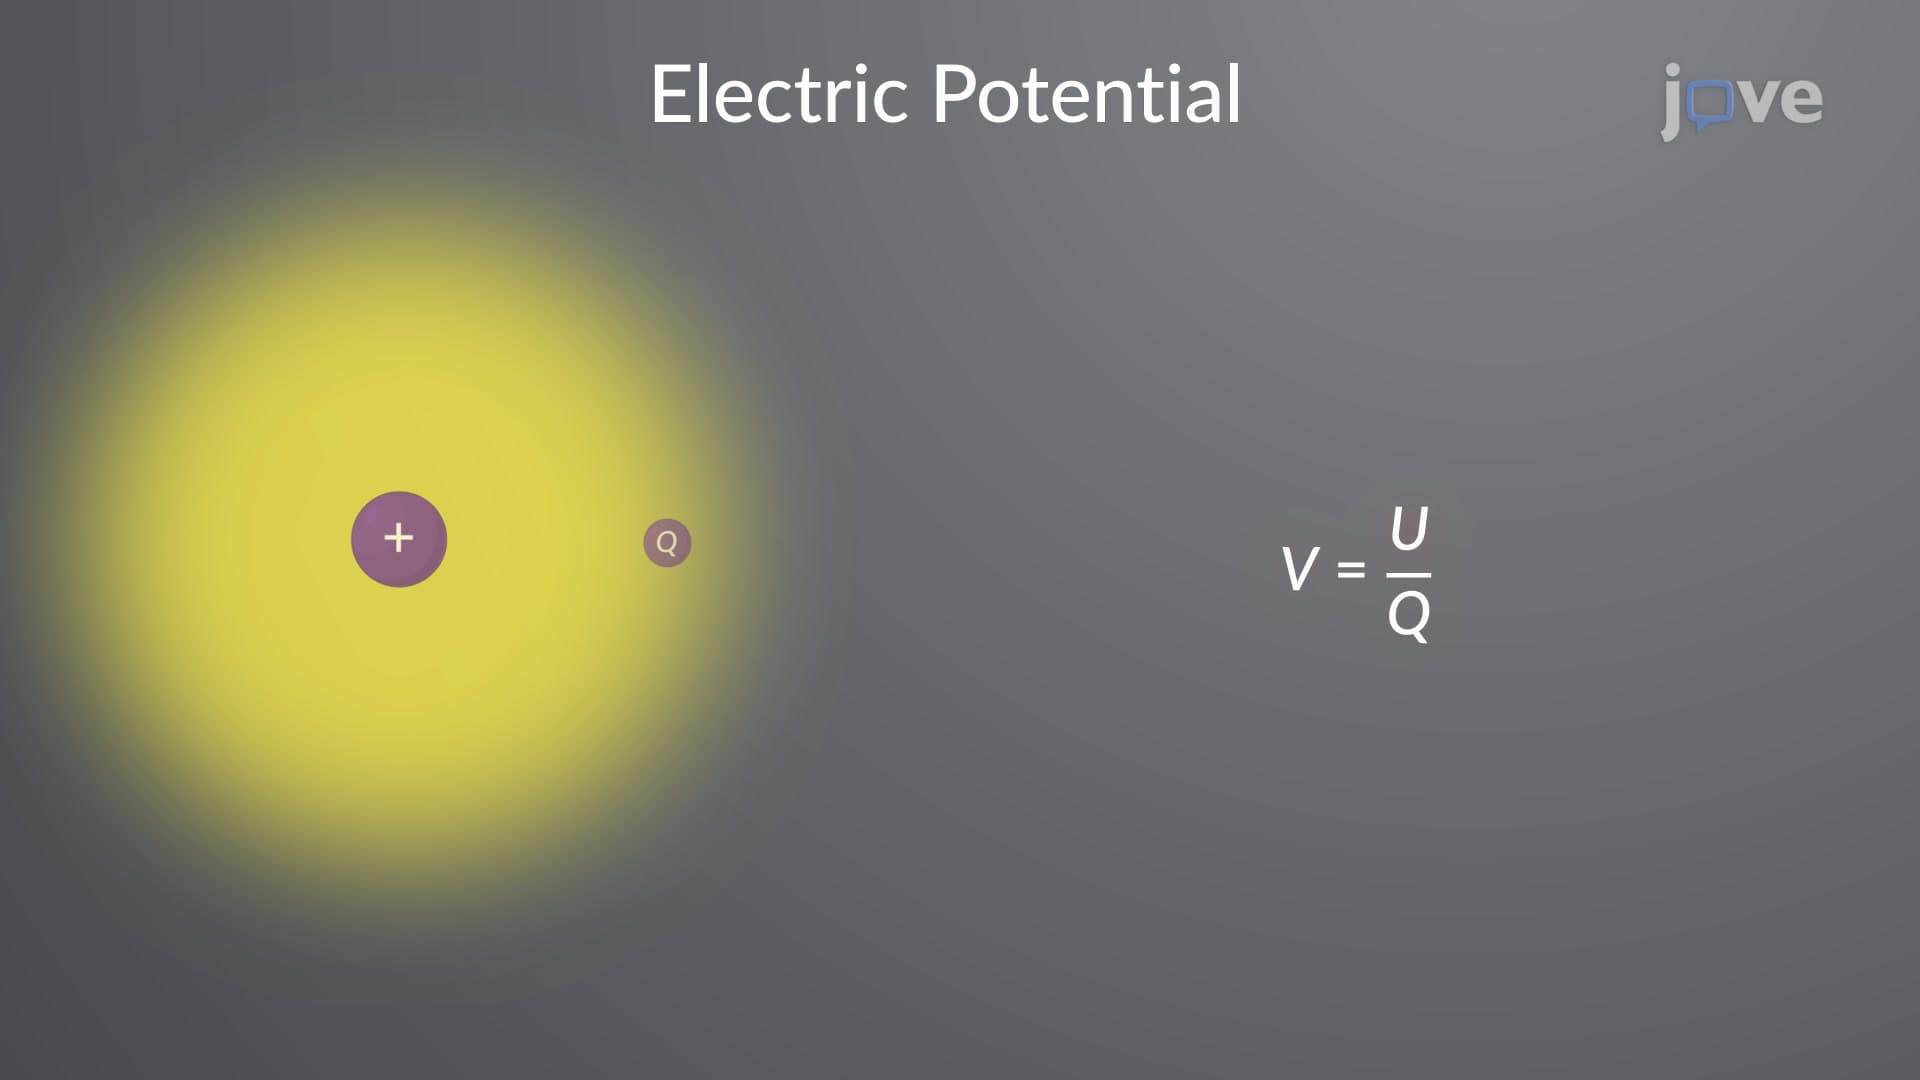
Electric Potential and Potential Difference
When a test charge moves from the initial to the final position, the electric potential difference between those positions is defined as the ratio of the change in the potential energy to the charge on the...
 01:05
Difference from Background: Limit of Detection
The LOD indicates the presence or absence...
 01:14
Identifying Statistically Significant Differences: The F-Test
 01:22
Sum and Difference OpAmps
A summing amplifier, or an adder, utilizes an op-amp to merge multiple input signals into a single output signal. When audio signals are introduced into its input channels, the input resistors initiate currents that traverse feedback resistors, resulting in an output voltage. Applying Kirchhoff's current...