Related Experiment Video
Updated: Feb 7, 2026

Utilizing the Modified T-Maze to Assess Functional Memory Outcomes After Cardiac Arrest
Published on: January 5, 2018
Variation in post-TAVR antiplatelet therapy utilization and associated outcomes: Insights from the STS/ACC TVT
Matthew W Sherwood1, Sreekanth Vemulapalli2, John Kevin Harrison3
1Inova Heart and Vascular Institute, Falls Church VA; Duke Clinical Research Institute, Durham, NC.

Background:
Dual antiplatelet therapy (DAPT) is recommended following transcatheter aortic valve replacement (TAVR); however, the optimal antiplatelet strategy is undefined, and little is known about practice patterns. We aimed to describe contemporary practice patterns of antiplatelet therapy and their relationship to outcomes post-TAVR.
Methods:
The population was derived from the National Cardiovascular Data Registry, Society of Thoracic Surgeons/American College of Cardiology Transcatheter Valve Therapies Registry with Center for Medical Services linkage for 1-year outcomes from October 1, 2011 to June 30,2016. The primary outcome measured was DAPT use in patients without anticoagulation. Secondary outcomes included death, major bleeding, myocardial infarction (MI), and stroke at 1 year.
Results:
Overall, 16,694 patients underwent transfemoral TAVR at 444 hospitals and were discharged without anticoagulation. Among these, 13,546 (81.1%) patients were discharged on DAPT, whereas 3,148 patients (18.9%) were discharged on monotherapy. Patients discharged on DAPT versus monotherapy were similar in age, sex, and most comorbid illnesses but had higher rates of coronary artery disease (64.6% vs 52.3%; P < .01) and peripheral artery disease (25.2% vs 22.3%; P < .01). Hospital prescribing patterns varied significantly (median frequency of DAPT 85.7%, interquartile range 94.1%-74.2%). DAPT (vs monotherapy) patients had a similar mortality risk at 1 year (adjusted hazard ratio 0.92, 95% CI 0.81-1.05), significantly higher risk for major bleeding (1.48, 1.10-1.99), and similar hazard for stroke (1.04, 0.83-1.31) and MI (1.00, 0.72-1.39).
Conclusions:
In the United States, most patients were discharged on DAPT following TAVR. Practice patterns varied significantly among hospitals. Patients discharged with DAPT had a similar adjusted risk of mortality, stroke, and MI compared to antiplatelet monotherapy, although risk for bleeding was significantly higher. Future investigation is needed to define the optimal antiplatelet therapy for patients undergoing TAVR.
More Related Videos

Related Concept Videos
 02:53
Conservative Site-specific Recombination and Phase Variation
The recognition sites for Cre recombinase called LoxP...
 01:14
What is Variation?
The range, standard deviation, standard error, and variance are the different measures of variation.
Range: The range is the difference between its maximum and...
 01:19
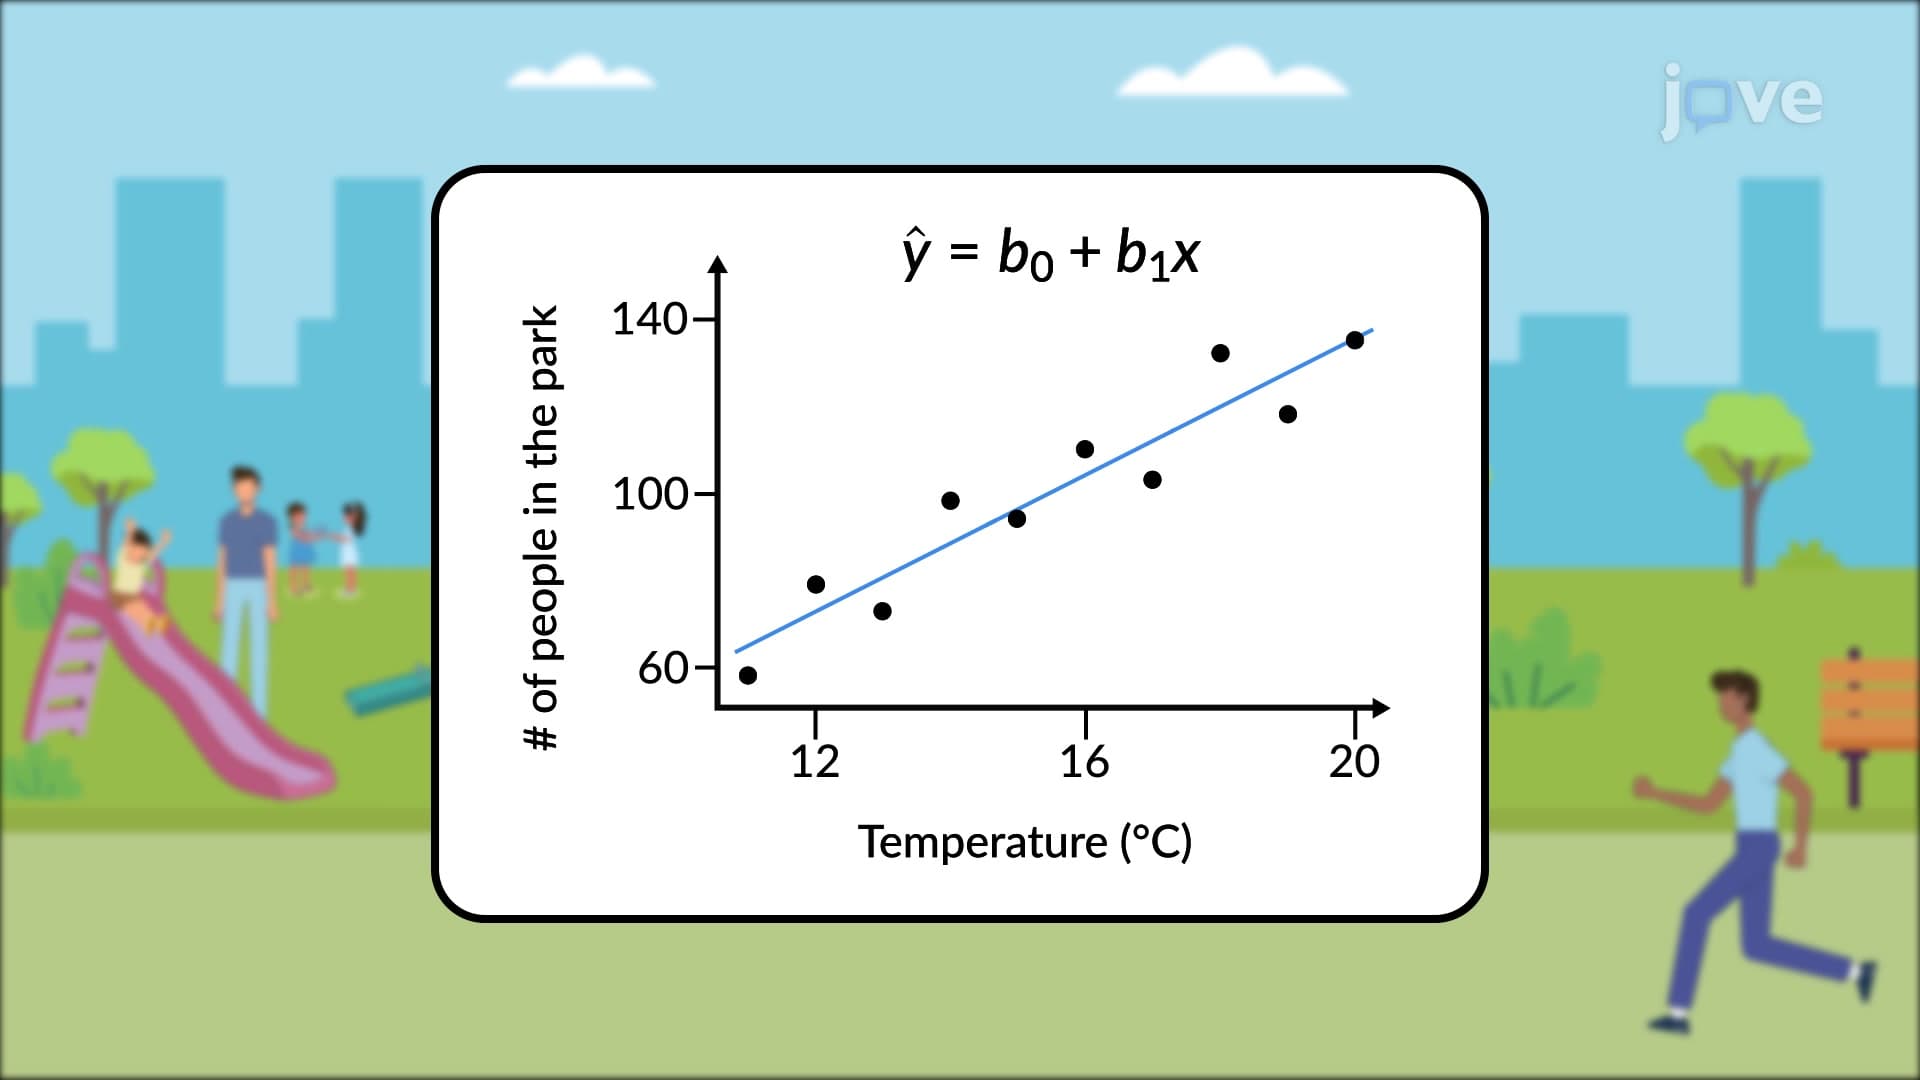
Variation
When independent and dependent variables are plotted on a scatter plot, the slope of a line is a value that describes the rate of change between the two...
 01:18
Variation of Atmospheric Pressure
Assuming the air temperature is constant at a given altitude and that the ideal gas law of thermodynamics describes the atmosphere to a good approximation, one can find the variation of atmospheric pressure with height.
Let p(y) be the atmospheric pressure at...
 02:26
Comparing Copy Number Variations and SNPs
Copy number variations or CNVs are the structural variations that cover more than 1kb of DNA sequence. The single nucleotide polymorphism (SNP), on the other hand, is a single nucleotide change or a point mutation that is found in more than 1%...
 02:24
Predicting Reaction Outcomes