Related Experiment Video
Updated: Feb 6, 2026


A Novel Method for Involving Women of Color at High Risk for Preterm Birth in Research Priority Setting
Published on: January 12, 2018
Assessing the Impact of Different Race-Bridging Algorithms on the Reported Rate of Birth Defects

Insights
Race-bridging techniques can help standardize birth defect data collected with inconsistent race categories. Different methods impact race-specific birth defect rates, suggesting further investigation is needed for optimal application.
Area of Science:
- Public Health
- Epidemiology
- Biostatistics
Background:
- Florida birth certificates changed race identification methods in 2004, from single to multiple race options.
- This data collection inconsistency impacts the accuracy of race-specific time trend analyses for birth defects.
- Race-bridging techniques aim to reassign multiple race responses to single categories for data standardization.
Purpose of the Study:
- To compare race-specific birth defect rates using two methods: current data handling and race-bridging techniques.
- To evaluate the impact of six different race-bridging methods on birth defect rate calculations.
Main Methods:
- Utilized Florida birth data (2005-2014) for non-Hispanic mothers.
- Calculated birth defect rates for White, Black, American Indian/Alaska Native (AIAN), and Asian/Pacific Islander (API) populations.
- Applied six distinct race-bridging methods: no bridging, largest group (whole allocation), smallest group (whole allocation), largest group other than white (whole allocation), equal fractions (fractional allocation), and reported fractions (fractional allocation).
Main Results:
- The choice of race-bridging method significantly altered race-specific birth defect rates.
- Whole allocation methods (largest/smallest group) generally increased White, Black, and API populations, decreasing their birth defect rates, while AIAN was unaffected or decreased.
- Fractional allocation methods (equal/reported fractions) increased live birth counts across all races, leading to corresponding decreases in birth defect rates.
Conclusions:
- Race-bridging techniques can improve comparability of race/ethnic data in birth defect studies, especially for national or longitudinal analyses.
- The impact of bridging methods on specific race categories and overall rates varies considerably.
- Further research is necessary to determine the optimal race-bridging technique for different health outcomes and populations.
Introduction:
In Florida prior to 2004, the birth certificate only allowed parents to identify themselves as 1 race. The birth certificate was subsequently revised in 2004, allowing parents to identify with more than 1 race. This inconsistency in data collection methods can greatly impact the results of race-specific time trend analyses. Race-bridging techniques have been developed to reassign multiple race responses to single race categories. This investigation aimed to compare race-specific birth defect rates calculated in 2 ways: (1) the current method: treating those selecting multiple race categories as though they selected Other race, and (2) the bridged method: attempting to classify those selecting multiple categories into the category they would have selected if they could only pick 1 race.
Methods:
Data from the Florida Office of Vital Statistics and the Florida Birth Defects Registry were used to examine rates of selected birth defects by race among births to non-Hispanic mothers from 2005 to 2014. Rates of selected birth defects were calculated and compared for the following race groups: white, black, American Indian/Alaska Native (AIAN), and Asian/Pacific Islander (API) using the following 6 bridging methods: (1) no bridging method, (2) largest group, whole allocation, (3) smallest group, whole allocation, (4) largest group other than white, (5) equal fractions, fractional allocation, and (6) reported fractions, fractional allocation.
Results:
The differences in birth defect rates comparing the current method to the recalculated bridged-race population depends on the bridging method used. Using largest group, whole-allocation, the total population of white, black, and API races increased, whereas the total number of AIAN remained unaffected. Using the smallest group or largest group other than white, whole-allocation, the total population of black, API, and AIAN increased, resulting in decreased birth defect rates. Lastly, using equal fractions or reported fractions, fractional allocation we found an increase in the live birth count for each race and a corresponding decrease in birth defect rates.
Discussion:
Race-bridging techniques may be useful when reviewing race-specific rates over time, or to account for the lack of comparability of race/ethnic classification in birth defect studies, particularly national studies combining data from different states. However, determining the best race-bridging technique warrants further investigation on larger populations and on other health outcomes.

Related Concept Videos
 01:22
Birth Control Methods
 01:15
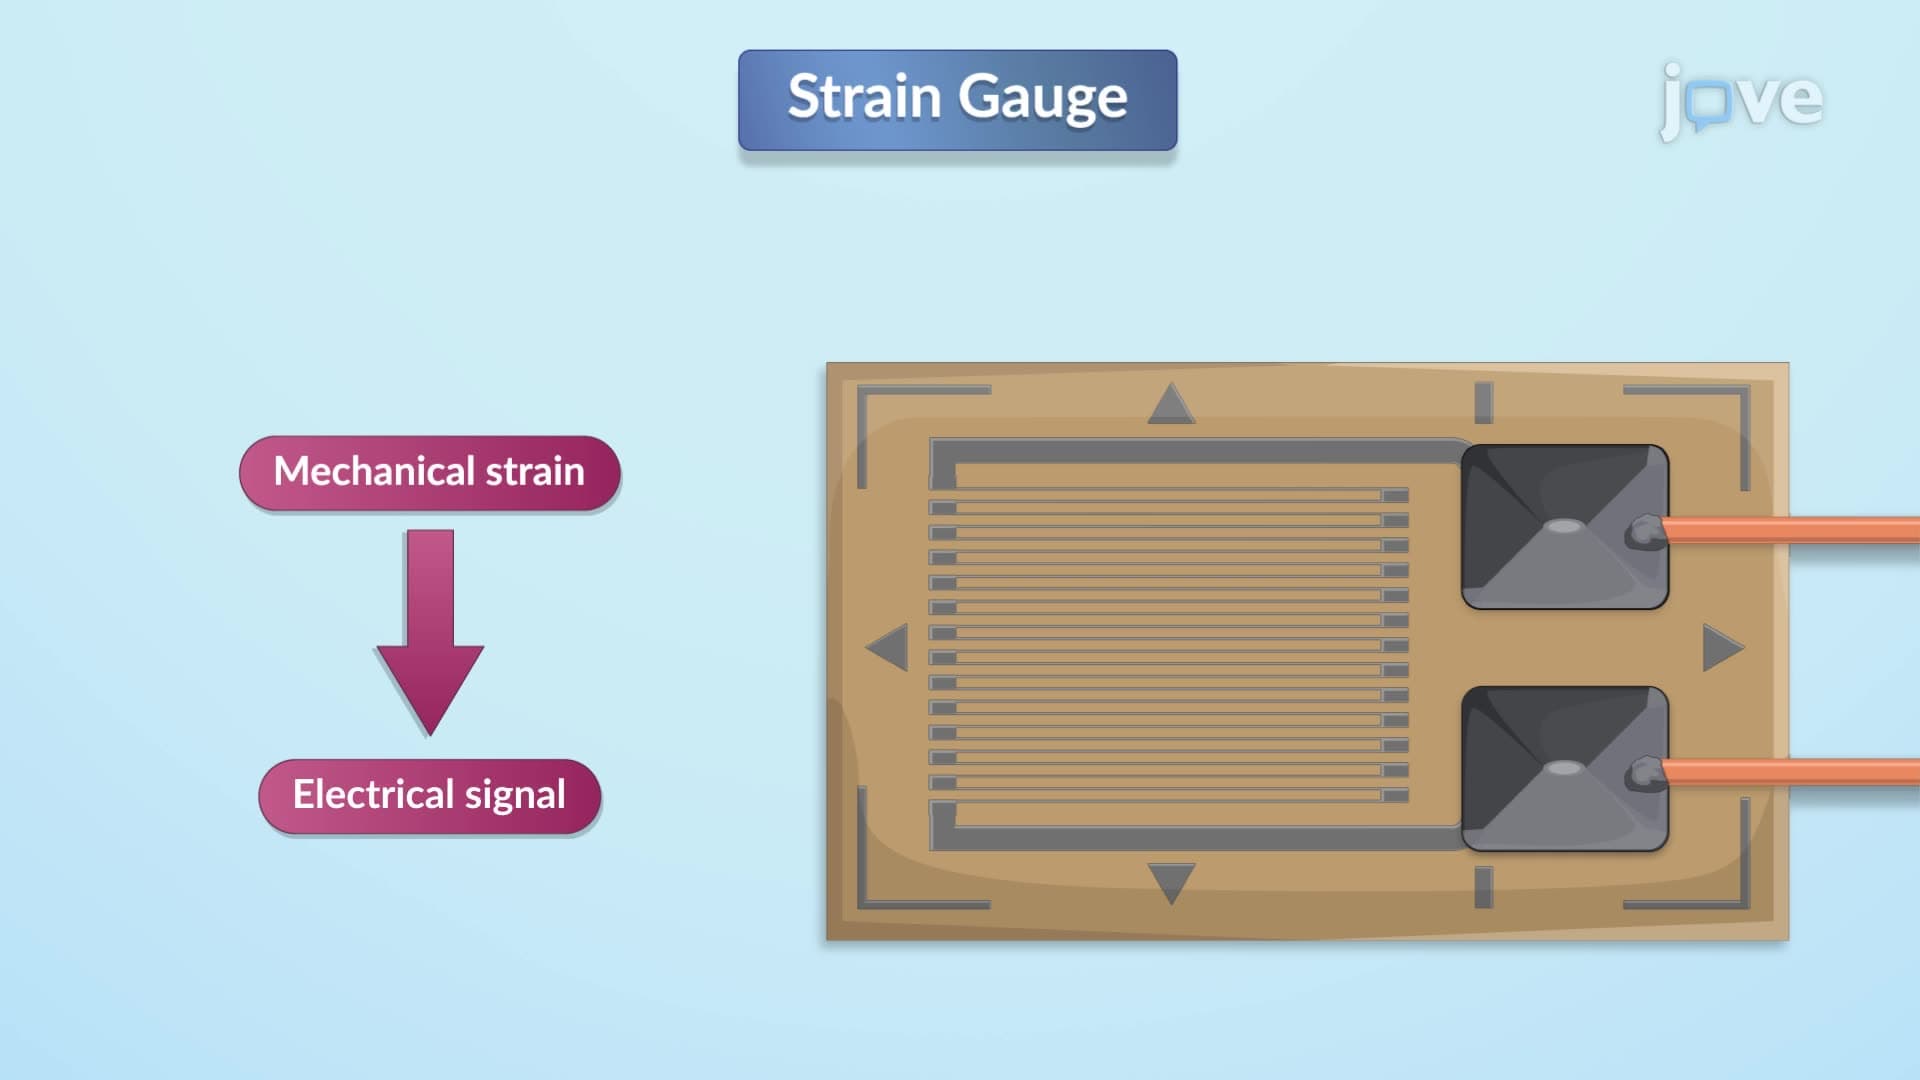
Design Example: Strain Gauge Bridge or Wheatstone Bridge
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:29
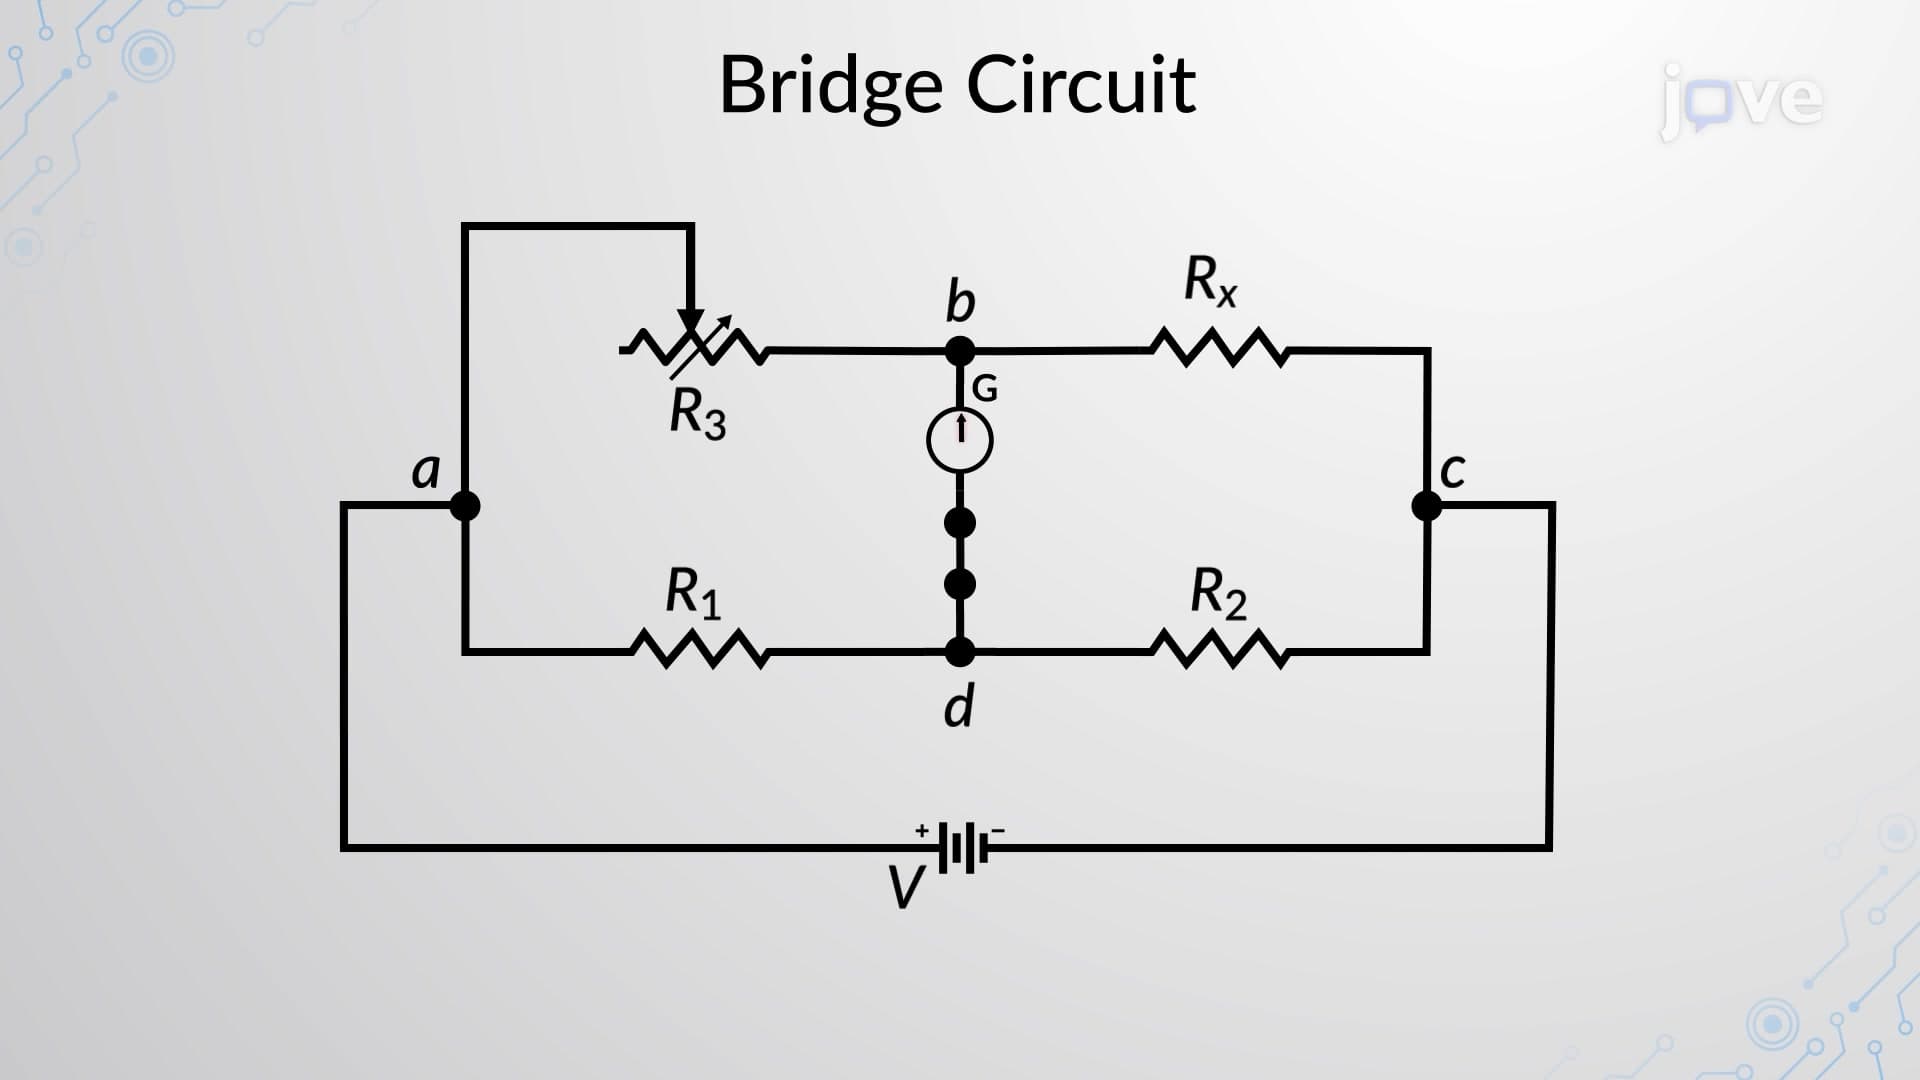
Wheatstone Bridge
Thus, for accurate resistance measurements, a...
 01:24
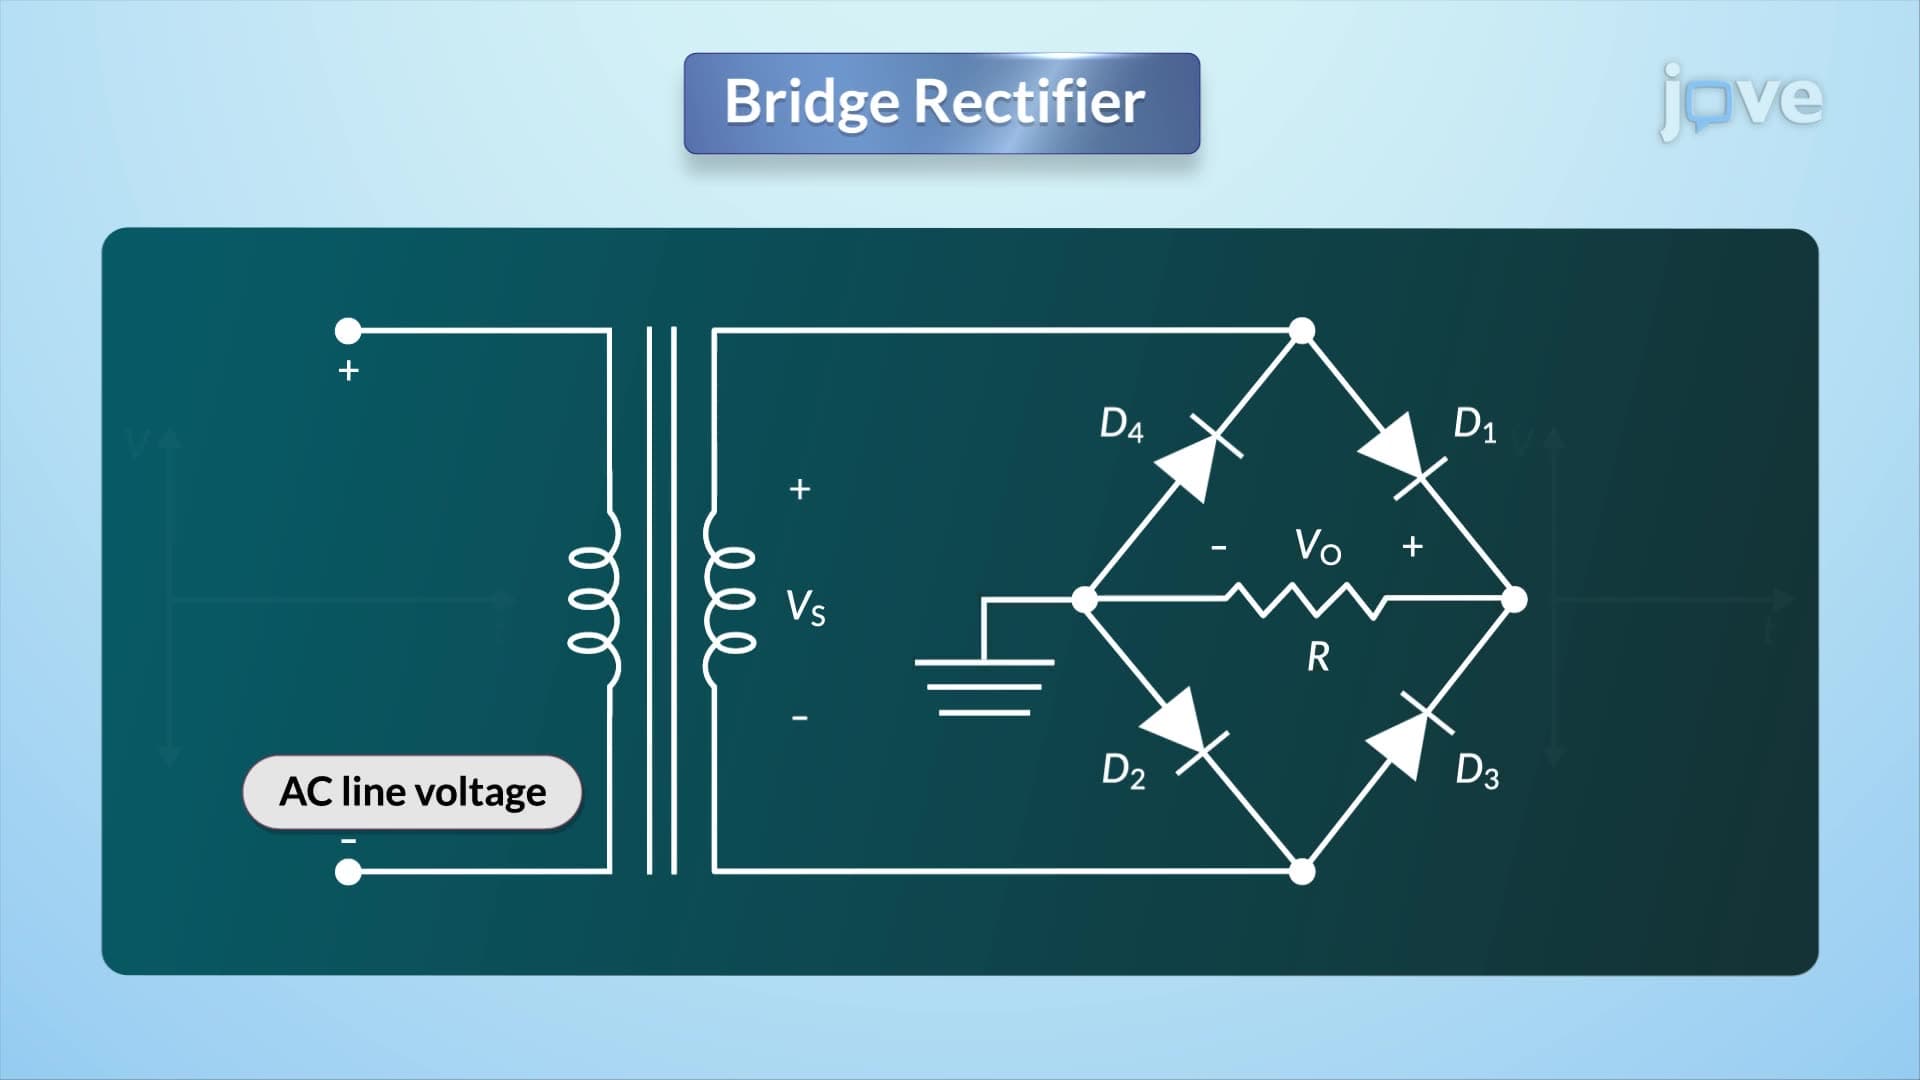
Bridge rectifier
Operationally, the bridge rectifier allows current flow through two of its diodes during each...
 02:35
RACE - Rapid Amplification of cDNA Ends