Related Experiment Video
Updated: Feb 6, 2026
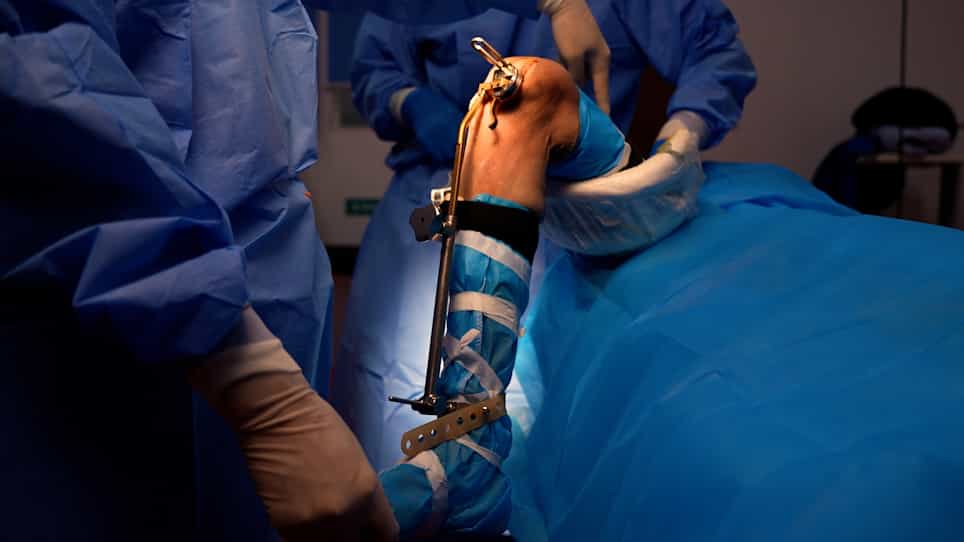

In Vitro Application of a Wireless Sensor in Flexion-Extension Gap Balance of Unicompartmental Knee Arthroplasty
Published on: May 5, 2023
An innovative three-dimensional method for identifying a proper femoral intramedullary entry point in total knee
Lu-Yao Ma1, Hong-Yu Wei2, Fu-Yin Wan3
1Department of Orthopaedics, Second Hospital of Shanxi Medical University, Taiyuan, Shanxi 030001, China.

Background::
Identification of the proper femoral intramedullary (IM) access point is an important determinant of final implant position in IM-guided total knee arthroplasty (TKA). The aim of this study was to identify the optimal entry point in Chinese participants using a new three-dimensional method.
Methods::
A series of computed tomography scans of 44 femurs in Chinese participants from October 2014 to October 2015 were imported into Mimics 17.0 software to identify the optimal entry point. The apex of the intercondylar notch (AIN) was used as the reference bony anatomical landmark to identify the proper entry point to insert the IM rod. The statistical significance was calculated on the basis of a 5% level (P < 0.05) using the Student's t-test.
Results::
For the males, the average ideal entry point was 1.49 mm medial and 13.39 mm anterior to the AIN. The values were 1.77 mm medial and 15.29 mm anterior to the AIN in females. A significant difference was present between males and females (13.39 ± 2.46 mm vs. 15.29 ± 3.44 mm, t = 2.124, P = 0.040). When using the recommended location as the entry point for the IM rod, the mean potential error differed significantly from the femoral trochlear groove (the potential error of IM in males in coronal plane: 0.93° ± 0.24° vs. 1.27° ± 0.32°, t = -4.166, P <0.001; the potential error of IM in males in sagittal plane: 1.40° ± 0.42° vs. 2.79° ± 0.70°, t = 7.155, P < 0.001; the potential error of IM in females in coronal plane: 0.73° ± 0.28° vs. 1.15° ± 0.35°, t = 3.940, P < 0.001; and the potential error of IM in females in sagittal plane: 1.48° ± 0.47° vs. 2.76° ± 0.83°, t =5.574, P < 0.001). A significant difference was present between the recommended point and the point 10 mm anterior to the origin of the posterior cruciate ligament (the potential error of IM in males in coronal plane: 0.93° ± 0.24° vs. 1.53° ± 0.43°, t = 5.948, P < 0.001; the potential error of IM in males in sagittal plane: 1.40° ± 0.42° vs. 2.15° ± 0.75°, t = 3.152, P = 0.003; the potential error of IM in females in coronal plane: 0.73° ± 0.28° vs. 1.28° ± 0.42°, t = -4.632, P < 0.001; and the potential error of IM in females in sagittal plane: 1.48° ± 0.47° vs. 2.40° ± 0.93°, t = 3.763, P = 0.001).
Conclusions:
The technique described here is an innovative method for swift, easy, and accurate access to the medullary canal during TKA, and it can optimize the position and orientation of the prosthetic components in knee arthroplasty.


Related Concept Videos
 01:23
Knee Joint
A total of seven ligaments support the knee joint. The patellar ligament, which is also attached to the quadriceps femoris...
 01:25
Overview of Connective Tissues Proper
The loose connective tissues have a meshwork of thin collagen and elastin fibers, which provide tensile strength for support and enough elasticity to move...
 01:21
Layers of Connective Tissue Proper
 03:40
Dimensional Analysis
Conversion Factors and Dimensional Analysis
The unit...
 01:27
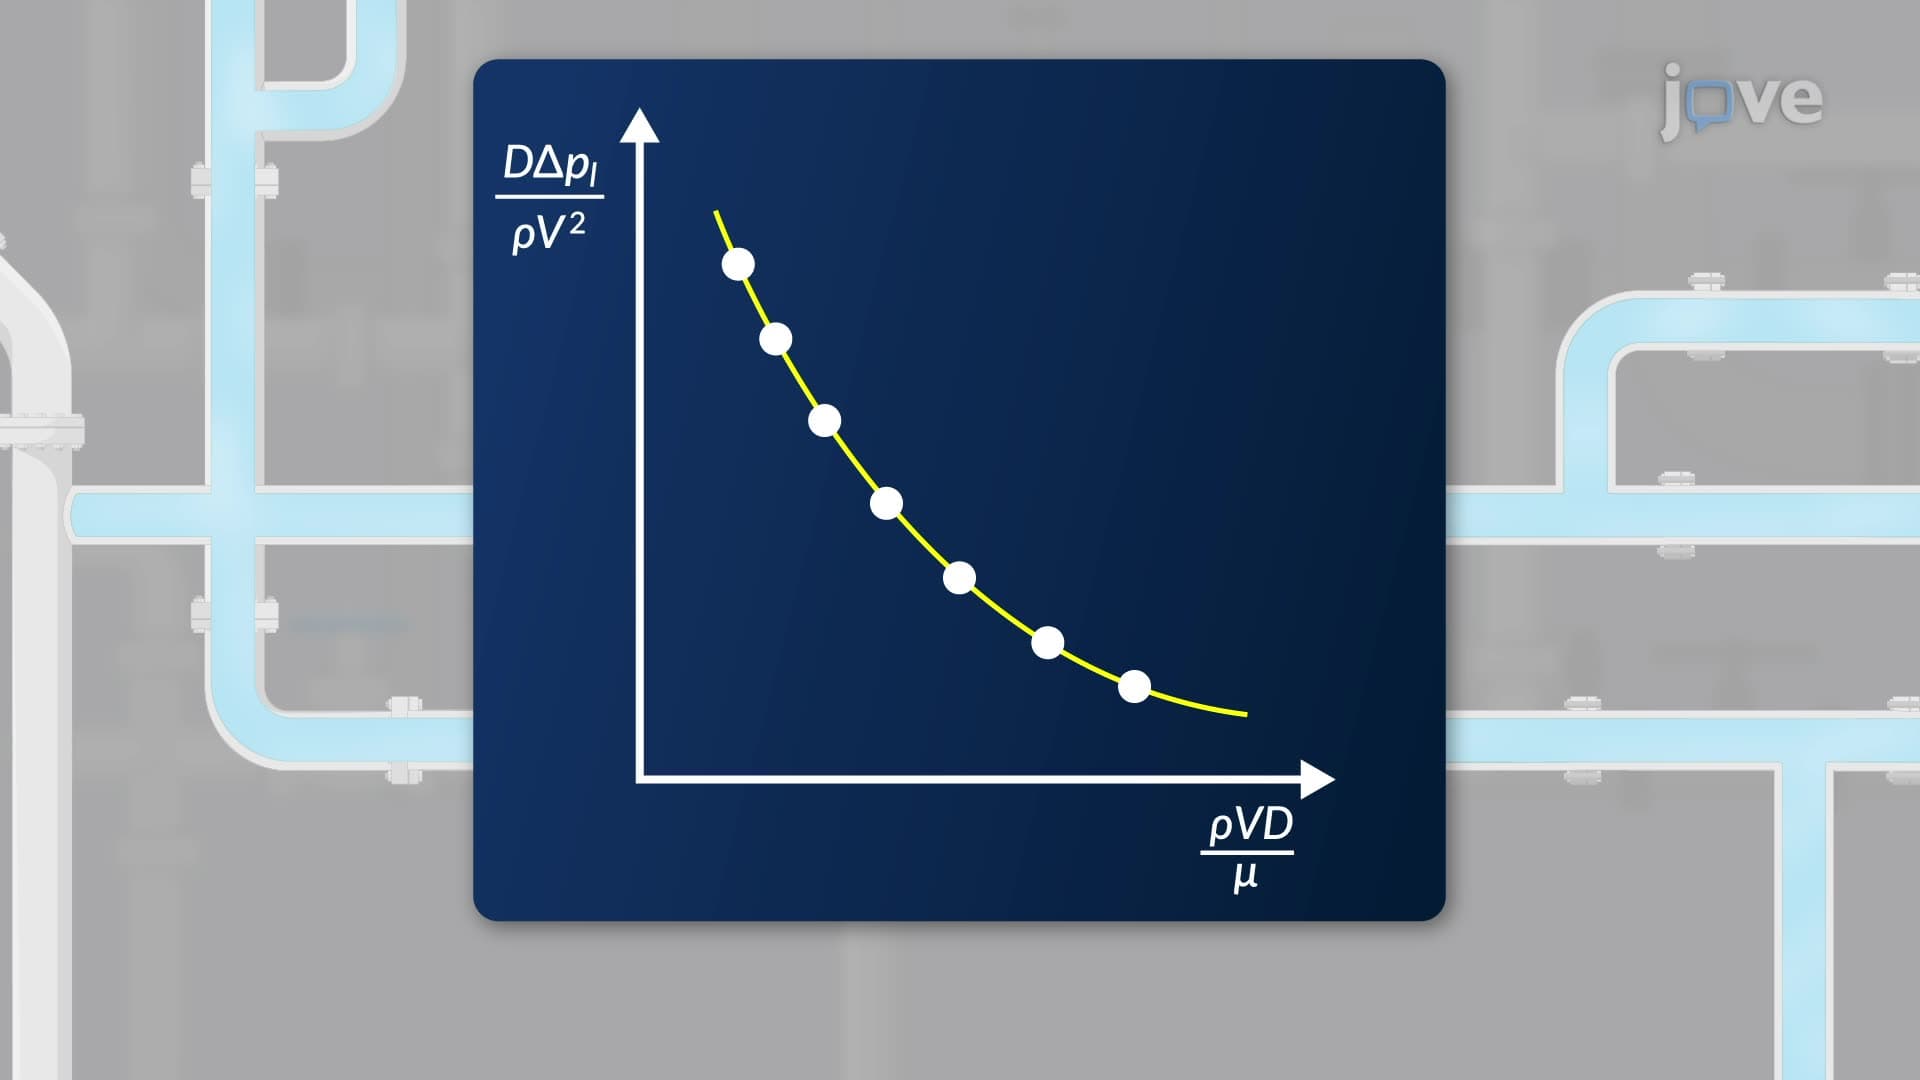
Dimensional Analysis
In fluid mechanics, dimensional...
 01:12
Total Voids in Concrete