Do auras predict seizure outcome after temporal lobe epilepsy surgery?
Related Experiment Video
Updated: Feb 5, 2026
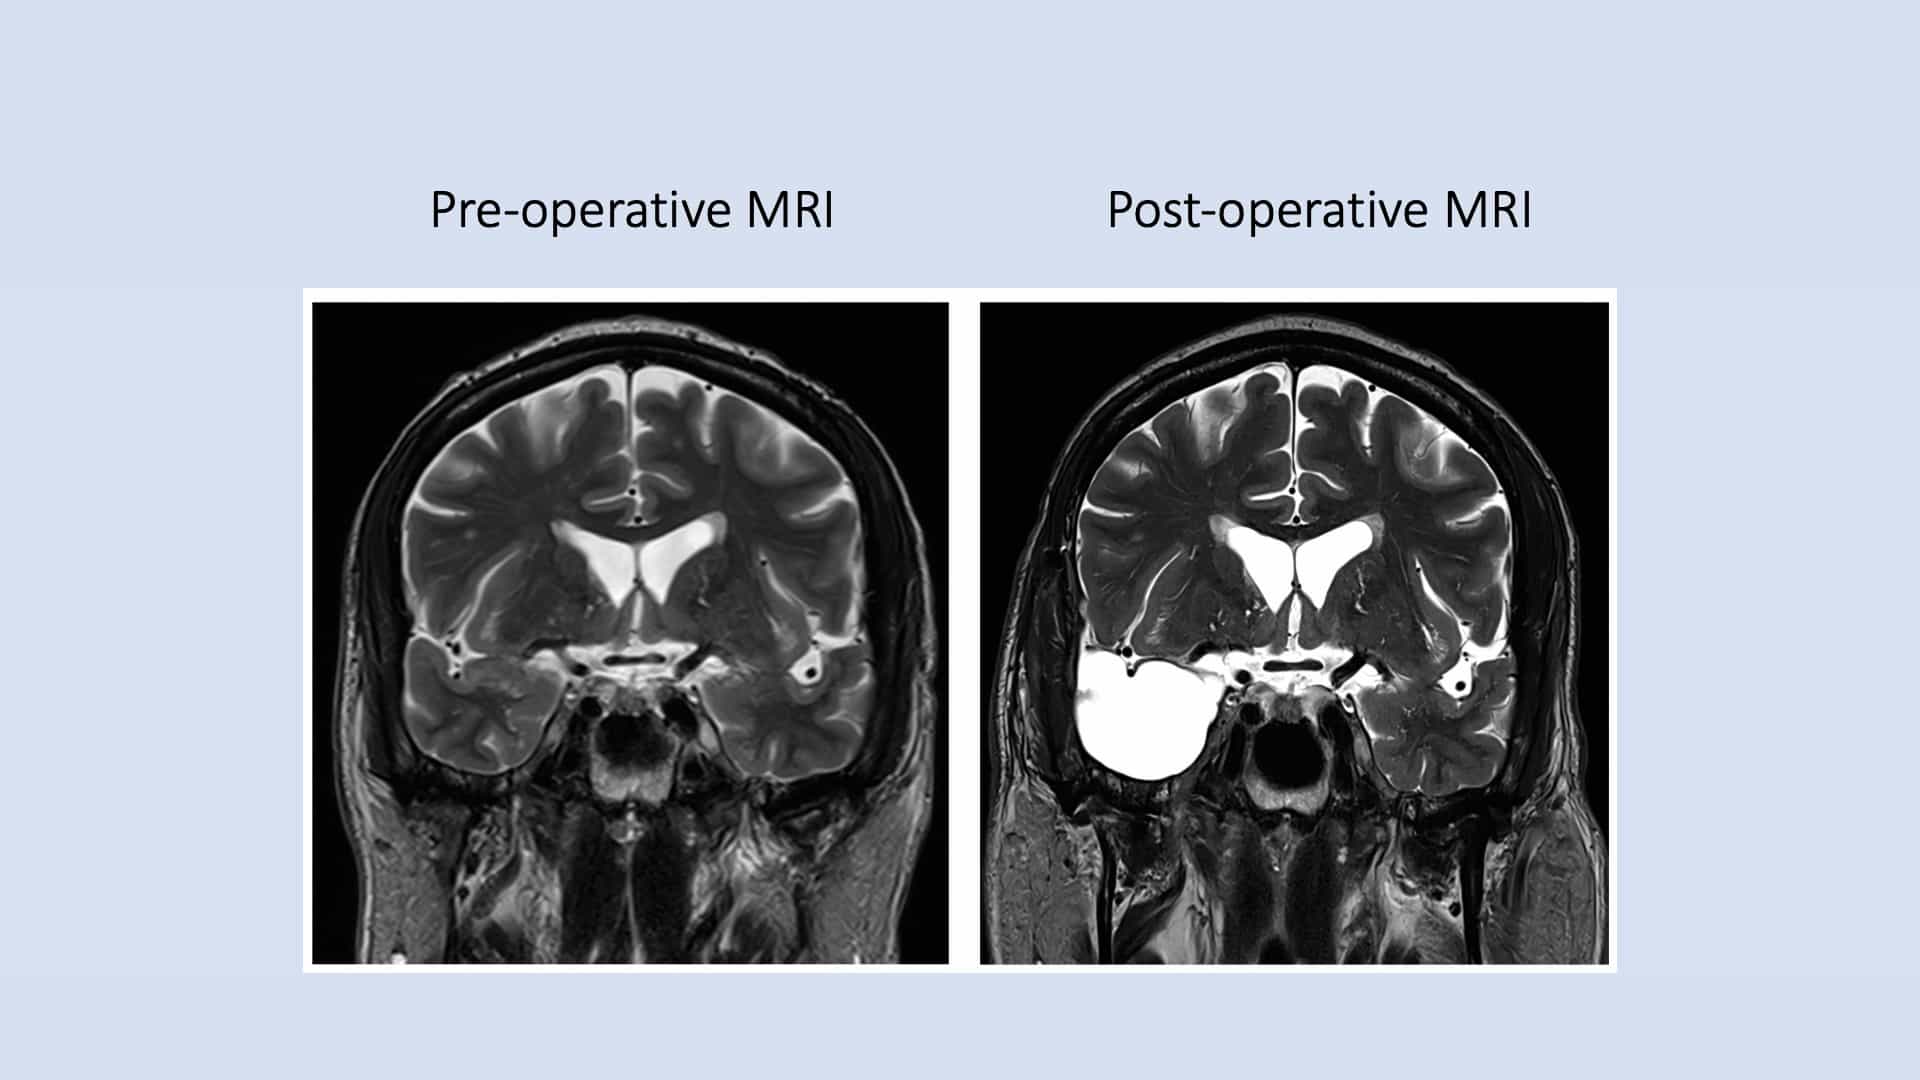
Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Radhakrishnan Ashalatha1, Ramshekhar N Menon1, Anuvitha Chandran1
1R. Madhavan Nayar Center for Comprehensive Epilepsy Care, Department of Neurology, Sree Chitra Tirunal Institute for Medical Sciences and Technology, Thiruvananthapuram, Kerala, India.

Purpose:
The success of epilepsy surgery lies in identifying the ictal onset zone accurately. The significance of auras has little been explored on surgical outcome in drug-resistant epilepsy. This study focuses on the clinicopathological correlation of aura(s) and its role in predicting surgical outcome in drug-resistant temporal lobe epilepsy (TLE). We compared surgical outcome in TLE between patients with and without aura and identified the clinico-pathological, radiological and surgical differences between the two groups.
Methods:
Consecutive patients who underwent presurgical evaluation from January 2009 to December 2014 for drug-resistant TLE who underwent anterior temporal lobectomy (ATL) were included. Patients were followed up at 3months, 12 months and then annually.
Results:
Among 456 patients, 344(75%) had aura. Multivariate logistic regression showed that prototype EEG pattern at ictal onset (OR 2.12, 95% CI 1.18-3.06, p = 0.012) and right sided epileptogenic zone (OR 1.82 95% CI 1.18-3.78, p = 0.007) were significantly associated with presence of aura. There was no difference in surgical outcome between those with and without aura. But patients with auditory aura (OR 7.28, CI 2.80-18.95, p = 0.0002) and vertiginous aura (OR 3.01, CI 1.55-7.85, p = 0.028) had a poor surgical outcome. Bivariate analysis showed that normal MRI (p = 0.028) and normal/indeterminate pathology (p = 0.001) were significantly more common with auditory/vertiginous auras.
Conclusions:
Mere presence of aura does not affect outcome after TLE surgery. However, auditory and vertiginous auras are predictors of poor surgical outcome. These patients require more extensive screening for an ictal onset zone beyond standard limits of ATL before surgery.
More Related Videos

Related Concept Videos
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 02:24
Predicting Reaction Outcomes
 01:22
Lobes of the Cerebrum
Frontal lobe
The frontal lobes, located behind the forehead, are the command center of our brain, controlling personality, intelligence, and voluntary muscle movements....
 02:27
Predicting Molecular Geometry
 01:13
Outcomes of Glycolysis
Cellular respiration can occur aerobically (with oxygen) or anaerobically (without oxygen). In the presence of oxygen, cellular respiration starts with glycolysis and continues with pyruvate...
 01:13
Seizures: Classification
Seizures are typically classified into two main categories: focal and generalized seizures.
Focal Seizures
Focal seizures originate from specific regions of the brain. These seizures are further sub-classified into two types: