Related Experiment Video
Updated: Feb 5, 2026


Four-Dimensional Computed Tomography-Guided Valve Sizing for Transcatheter Pulmonary Valve Replacement
Published on: January 20, 2022
Implications of Transcatheter Heart Valve Selection on Early and Late Pacemaker Rate and on Length of Stay
Janarthanan Sathananthan1, Lillian Ding2, Maggie Yu2
1Centre for Heart Valve Innovation, Vancouver, British Columbia, Canada.

Insights
Transcatheter aortic valve replacement (TAVR) device type significantly impacts pacemaker needs and hospital stay duration. Balloon-expandable valves show lower rates of permanent pacemaker implantation compared to self-expandable and mechanical valves.
Area of Science:
- Cardiovascular Medicine
- Interventional Cardiology
- Biomaterials Science
Background:
- Transcatheter aortic valve replacement (TAVR) is a common procedure for aortic stenosis.
- TAVR can lead to conduction system disturbances requiring pacemaker implantation.
- The type of transcatheter heart valve (THV) used may influence these complications.
Purpose of the Study:
- To evaluate the impact of different transcatheter heart valve (THV) types on pacemaker implantation rates after TAVR.
- To assess the effect of THV type on hospital length of stay following TAVR.
Main Methods:
- A registry-based study of 1141 patients undergoing transfemoral TAVR between 2012 and 2016.
- Comparison of outcomes based on three THV types: balloon-expandable (BEV), self-expandable (SEV), and mechanically-expandable (MEV).
- Analysis included temporary and permanent pacemaker implantation rates at 30 days and 1 year, and median hospital length of stay.
Main Results:
- Temporary pacemaker use varied significantly: BEV (4.0%), SEV (69.3%), MEV (63.0%).
- Permanent pacemaker implantation rates at 1 year were substantially higher for SEV (26.9%) and MEV (35.9%) compared to BEV (8.9%).
- Median hospital stay was shortest for BEV (1 day) versus SEV (3 days) and MEV (4 days).
Conclusions:
- THV device choice significantly influences post-TAVR pacemaker requirements and hospital length of stay.
- These device-dependent differences have implications for patient morbidity and healthcare resource utilization.
Background:
Transcatheter aortic valve replacement (TAVR) can cause injury to the atrioventricular conduction system. We evaluated the effect of transcatheter heart valve (THV) type on the rate of new pacemaker implantation and length of hospital stay.
Methods:
Patients across all hospitals performing transfemoral TAVR in the province of British Columbia between 2012 and 2016 participated in a mandated registry with linkages to provincial health databases. We evaluated 1141 patients undergoing successful transfemoral TAVR for native aortic valve stenosis with 5 commonly used valves.
Results:
Valves implanted were balloon-expandable (BEV) (n = 728), self-expandable (SEV) (n = 341), and mechanically-expandable (MEV) (n = 72). Baseline clinical characteristics were similar between groups: mean age 82.5 years with multiple comorbidities. The mean Society of Thoracic Surgeons predicted risk of mortality was 6.0%. Indwelling temporary pacemakers after TAVR varied by THV type: (BEV) 4.0%, (SEV) 69.3%, and (MEV) 63.0% (P < 0.002). The need for a new permanent pacemaker varied by THV type: (BEV) 6.6%, (SEV) 24.0%, and (MEV) 32.8% at 30 days (P < 0.001). At 1 year, permanent pacemaker rates continued to rise, and remained divergent: (BEV) 8.9%, (SEV) 26.9%, and (MEV) 35.9% (P < 0.001). Median length of stay varied according to THV type: (BEV) 1, (SEV) 3, and (MEV) 4 days (P < 0.001 across groups). Crude mortality rates were not statistically different by THV type, either at 30 days (BEV 3.0%, SEV 2.9%, and MEV 0.0%; P = 0.33), or at 1 year (BEV 10.3%, SEV 15.0%, and MEV 8.3%; P = 0.11).
Conclusions:
The choice of a THV device was associated with significant differences in the need for post-TAVR temporary pacemakers, hospital length of stay, and both early and late pacemaker implantation rates. These differences may have an impact on patient morbidity and resource utilization.
More Related Videos
 05:31
Transcatheter Pulmonary Valve Replacement from Autologous Pericardium with a Self-Expandable Nitinol Stent in an Adult Sheep Model
Published on: June 8, 2022
 06:04
Upper-extremity Approach for Secondary Access in Transfemoral Transcatheter Aortic Valve Implantation
Published on: August 8, 2025
Related Concept Videos
 01:16
Heart Valves
The AV valves prevent the backflow of blood from the ventricles to the atria during ventricular contraction. These valves function with the assistance of the chordae tendineae and papillary muscles. When the ventricles are relaxed, the chordae tendineae are slack, allowing blood to flow from the atria into the...
 01:31
Regulation of Heart Rates
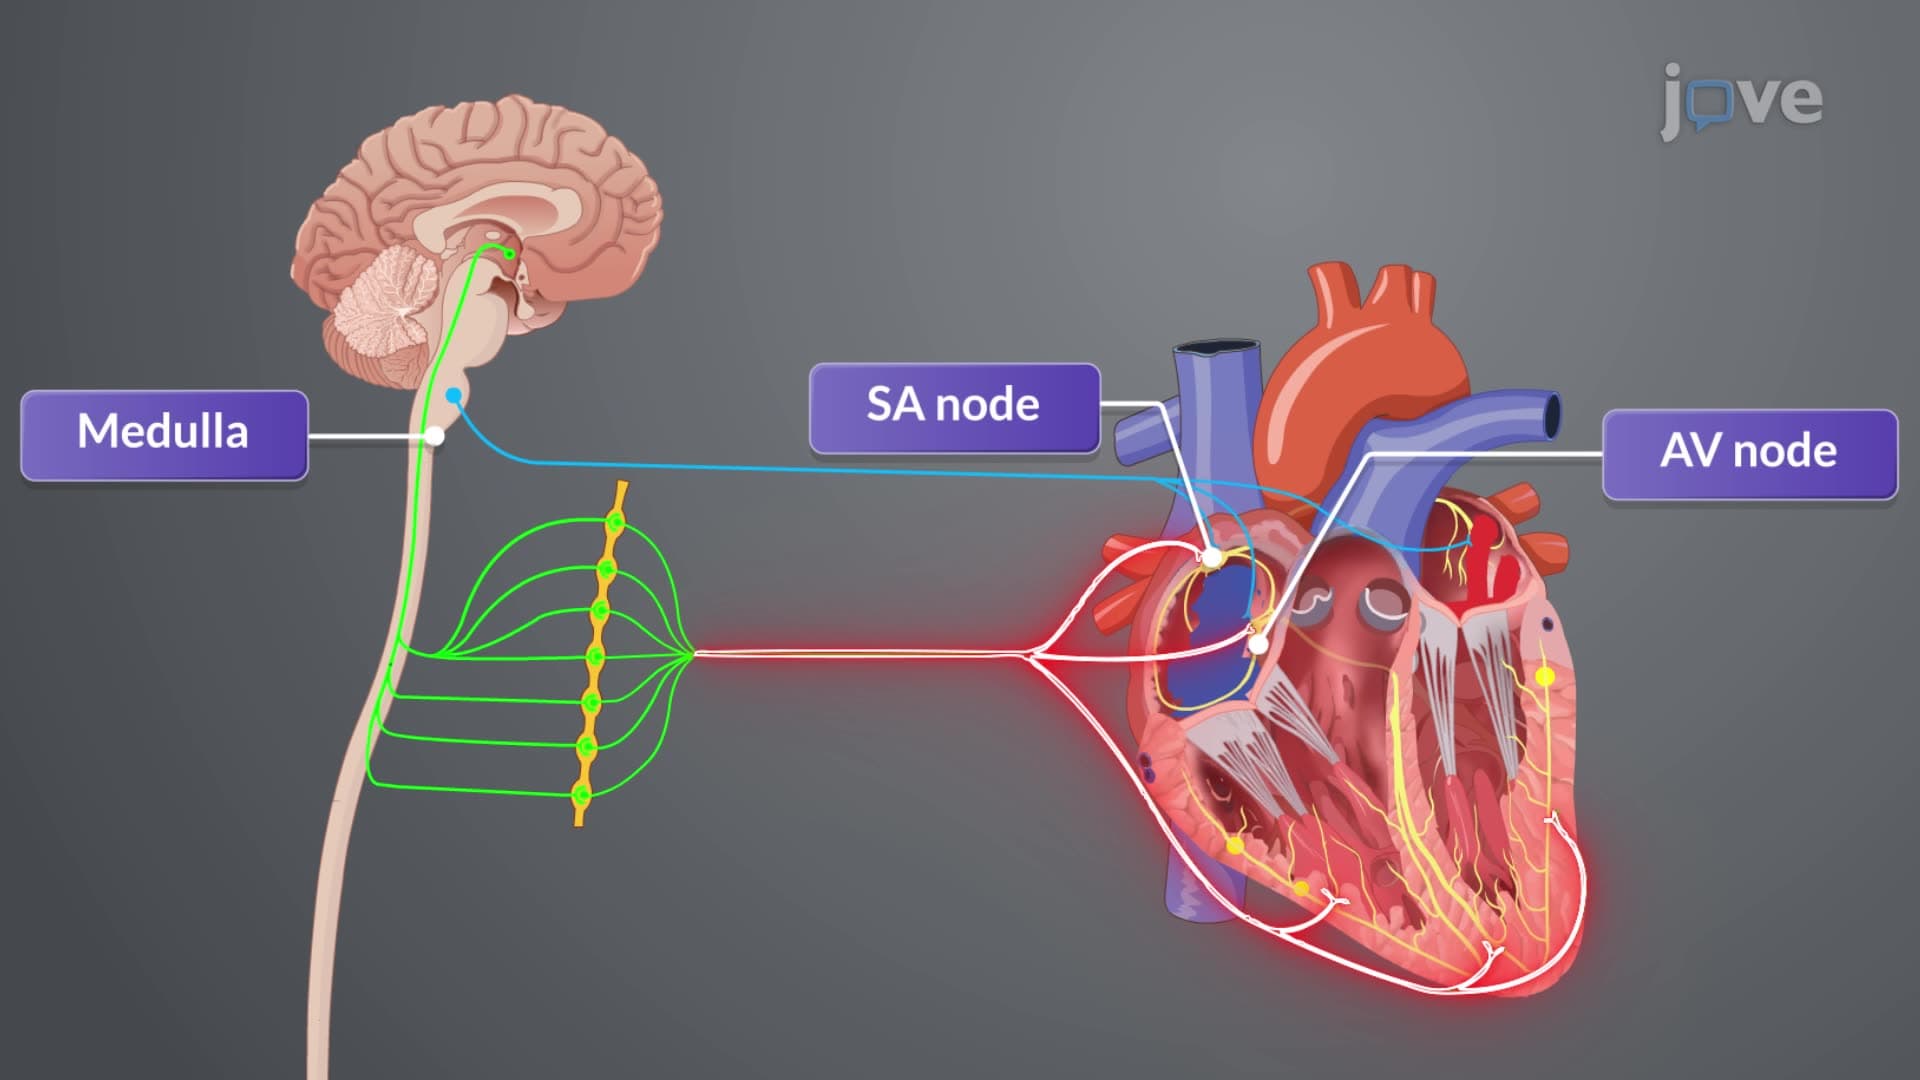
The SNS increases heart rate through the release of norepinephrine and epinephrine, which act on beta-1 adrenergic receptors in the heart. This action increases the rate of depolarization in the sinoatrial (SA) node, the heart's...
 01:30
Factors Influencing Heart Rate
Let us explore the significant factors affecting heart rate, including age, body temperature, posture, acute pain, chemical influences,...
 01:27
Anatomy of the Heart
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 02:53
Reaction Rate
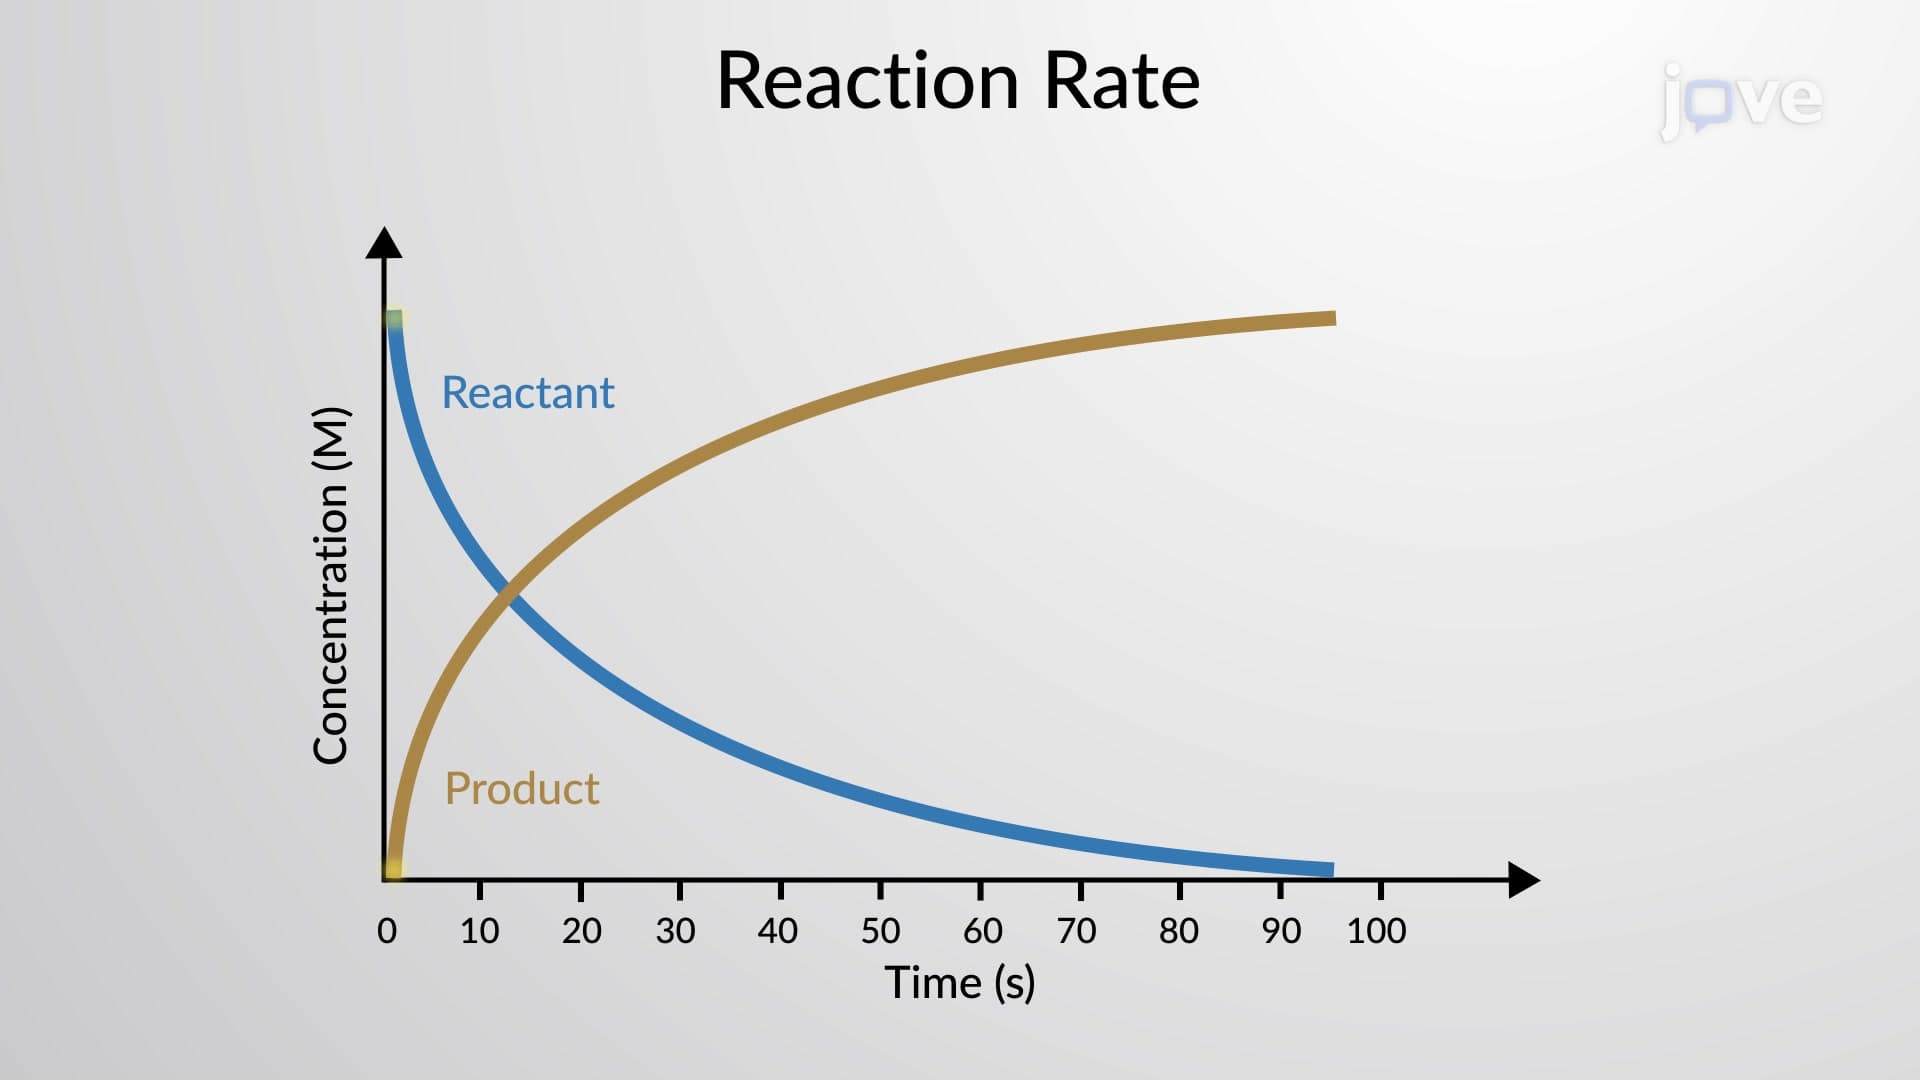
The mathematical representation of the change in the concentration of reactants and products, over time, is the rate...