Related Experiment Video
Updated: Feb 5, 2026


Objective Nociceptive Assessment in Ventilated ICU Patients: A Feasibility Study Using Pupillometry and the Nociceptive Flexion Reflex
Published on: July 4, 2018
Predicting ICU readmission among surgical ICU patients: Development and validation of a clinical nomogram
Luke A Martin1, Julie A Kilpatrick1, Ragheed Al-Dulaimi2
1Department of Surgery, University of Utah School of Medicine, Salt Lake City, UT.

Background:
Unplanned intensive care unit readmission within 72 hours is an established metric of hospital care quality. However, it is unclear what factors commonly increase the risk of intensive care unit readmission in surgical patients. The objective of this study was to evaluate predictors of readmission among a diverse sample of surgical patients and develop an accurate and clinically applicable nomogram for prospective risk prediction.
Methods:
We retrospectively evaluated patient demographic characteristics, comorbidities, and physiologic variables collected within 48 hours before discharge from a surgical intensive care unit at an academic center between April 2010 and July 2015. Multivariable regression models were used to assess the association between risk factors and unplanned readmission back to the intensive care unit within 72 hours. Model selection was performed using lasso methods and validated using an independent data set by receiver operating characteristic area under the curve analysis. The derived nomogram was then prospectively assessed between June and August 2017 to evaluate the correlation between perceived and calculated risk for intensive care unit readmission.
Results:
Among 3,109 patients admitted to the intensive care unit by general surgery (34%), transplant (9%), trauma (43%), and vascular surgery (14%) services, there were 141 (5%) unplanned readmissions within 72 hours. Among 179 candidate predictor variables, a reduced model was derived that included age, blood urea nitrogen, serum chloride, serum glucose, atrial fibrillation, renal insufficiency, and respiratory rate. These variables were used to develop a clinical nomogram, which was validated using 617 independent admissions, and indicated moderate performance (area under the curve: 0.71). When prospectively assessed, intensive care unit providers' perception of respiratory risk was moderately correlated with calculated risk using the nomogram (ρ: 0.44; P < .001), although perception of electrolyte abnormalities, hyperglycemia, renal insufficiency, and risk for arrhythmias were not correlated with measured values.
Conclusion:
Intensive care unit readmission risk for surgical patients can be predicted using a simple clinical nomogram based on 7 common demographic and physiologic variables. These data underscore the potential of risk calculators to combine multiple risk factors and enable a more accurate risk assessment beyond perception alone.


Related Concept Videos
 01:29
Reliability and Validity
 01:10
In Vitro Drug Release Testing: Overview, Development and Validation
 02:27
Predicting Molecular Geometry
 01:23
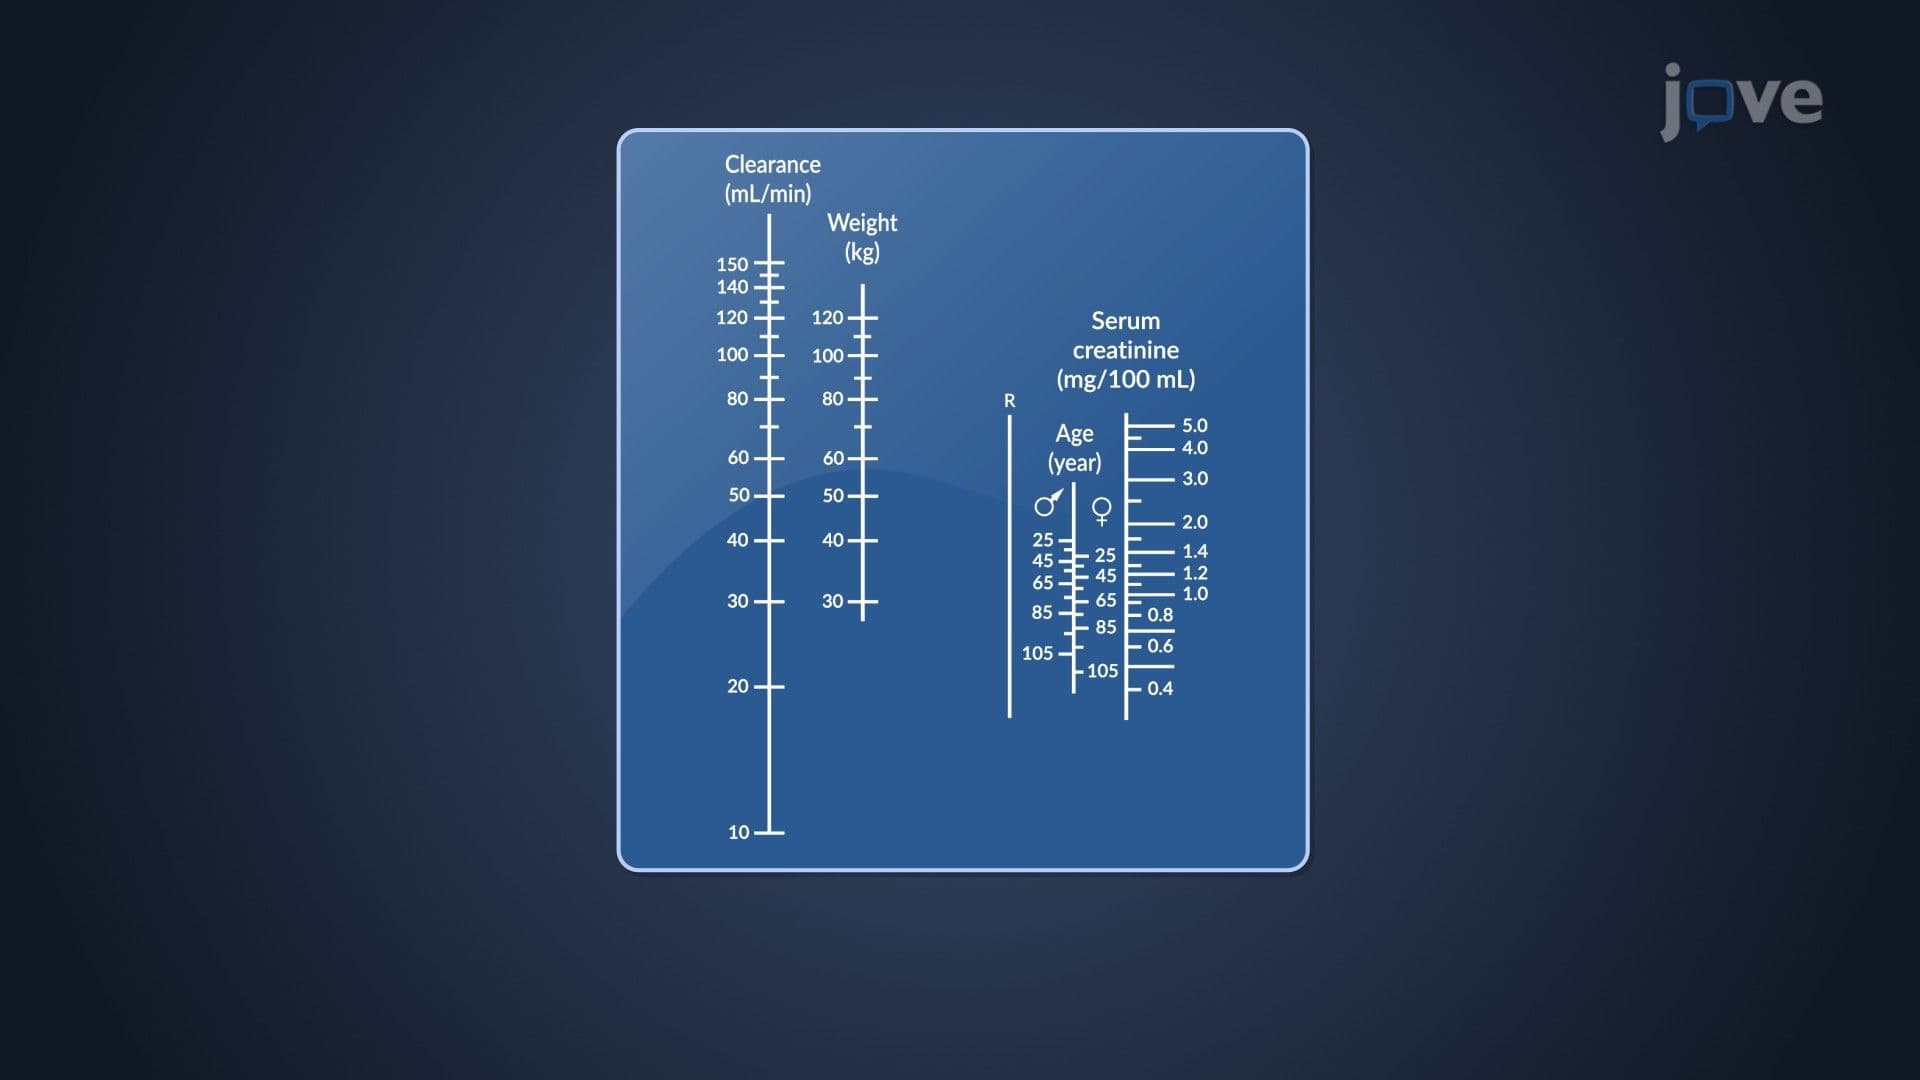
Dosage Regimen Designs: Nomograms and Tabulations
 01:03
Prediction Intervals
However, the point estimate is most likely not the exact value of the population parameter, but close to it. After calculating point estimates, we construct interval estimates, called confidence intervals or prediction intervals. This prediction interval comprises a range of values unlike the point estimate and is a better predictor of the observed sample value, y.
 01:15
Data Validation
Key parameters for method validation include: