Related Experiment Video
Updated: Feb 5, 2026
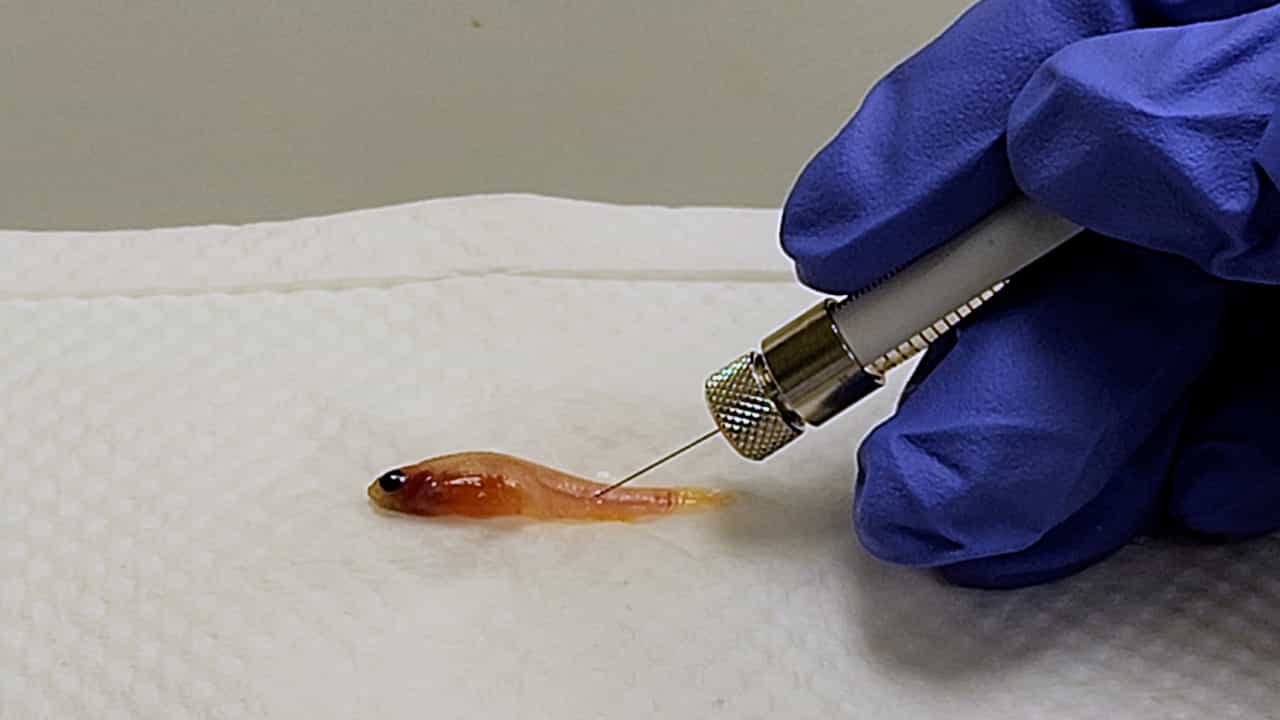
Optimized Intravenous Injection in Adult Zebrafish
Published on: December 20, 2024
High dose oral and intravenous rifampicin for improved survival from adult tuberculous meningitis: a phase II
Fiona V Cresswell1,2, Kenneth Ssebambulidde2, Daniel Grint3
1Clinical Research Department, London School of Hygiene and Tropical Medicine, London, WC1E 7HT, UK.

Abstract:
Background: Tuberculous meningitis (TBM) has 44% (95%CI 35-52%) in-hospital mortality with standard therapy in Uganda. Rifampicin, the cornerstone of TB therapy, has 70% oral bioavailability and ~10-20% cerebrospinal fluid (CSF) penetration. With current WHO-recommended TB treatment containing 8-12mg/kg rifampicin, CSF rifampicin exposures frequently fall below the minimal inhibitory concentration for M. tuberculosis. Two Indonesian phase II studies, the first investigating intravenous rifampicin 600mg and the second oral rifampicin ~30mg/kg, found the interventions were safe and resulted in significantly increased CSF rifampicin exposures and a reduction in 6-month mortality in the investigational arms. Whether such improvements can be replicated in an HIV-positive population remains to be determined. Protocol: We will perform a phase II, open-label randomised controlled trial, comparing higher-dose oral and intravenous rifampicin with current standard of care in a predominantly HIV-positive population. Participants will be allocated to one of three parallel arms (I:I:I): (i) intravenous rifampicin 20mg/kg for 2-weeks followed by oral rifampicin 35mg/kg for 6-weeks; (ii) oral rifampicin 35mg/kg for 8-weeks; (iii) standard of care, oral rifampicin 10mg/kg/day for 8-weeks. Primary endpoints will be: (i) pharmacokinetic parameters in plasma and CSF; (ii) safety. We will also examine the effect of higher-dose rifampicin on survival time, neurological outcomes and incidence of immune reconstitution inflammatory syndrome. We will enrol 60 adults with suspected TBM, from two hospitals in Uganda, with follow-up to 6 months post-enrolment. Discussion: HIV co-infection affects the bioavailability of rifampicin in the initial days of therapy, risk of drug toxicity and drug interactions, and ultimately mortality from TBM. Our study aims to demonstrate, in a predominantly HIV-positive population, the safety and pharmacokinetic superiority of one or both investigational arms compared to current standard of care. The most favourable dose may ultimately be taken forward into an adequately powered phase III trial. Trial registration: ISRCTN42218549 (24 th April 2018).

Related Concept Videos
 01:22
Phase-lead and Phase-lag Controllers
 01:19
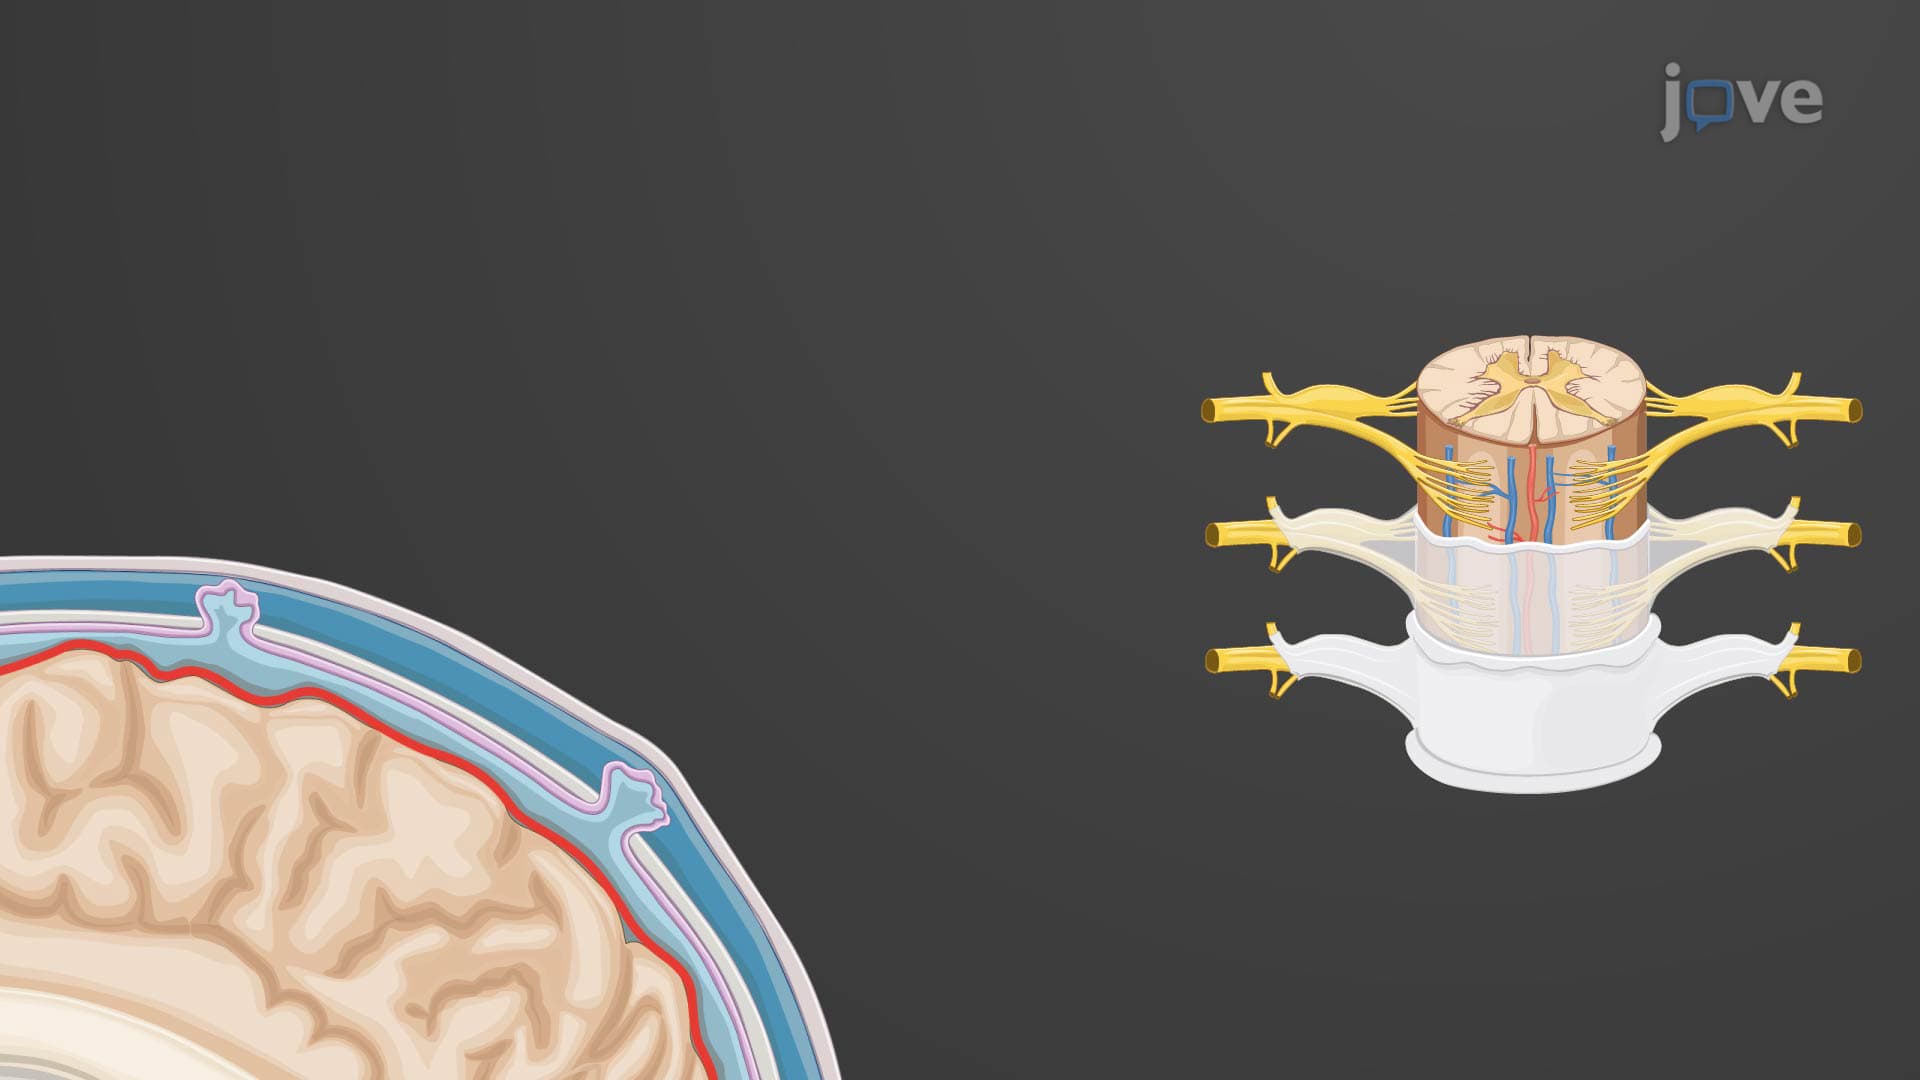
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:11
Bioavailability Study Design: Single Versus Multiple Dose Studies
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast,...
 01:24
Time and frequency -Domain Interpretation of Phase-lead Control
The design of phase-lead control involves the strategic placement of poles and zeros to balance steady-state error and system...