Related Experiment Video
Updated: Feb 5, 2026


Standardized Technique of Aortic Valve Re-implantation for Valve-sparing Aortic Root Replacement
Published on: December 11, 2017
The Learning Curve and Annual Procedure Volume Standards for Optimum Outcomes of Transcatheter Aortic Valve
Anthony W A Wassef1, Josep Rodes-Cabau2, Yaqing Liu1
1Division of Cardiology, Department of Medicine, St. Michael's Hospital, Toronto, Canada.

Objectives:
The authors aimed to determine the procedural learning curve and minimum annual institutional volumes associated with optimum clinical outcomes for transcatheter aortic valve replacement (TAVR).
Background:
Transcatheter aortic valve replacement (TAVR) is a complex procedure requiring significant training and experience for successful outcome. Despite increasing use of TAVR across institutions, limited information is available for its learning curve characteristics and minimum annual volumes required to optimize clinical outcomes.
Methods:
The study collected data for patients at 16 centers participating in the international TAVR registry since initiation of the respective TAVR program. All cases were chronologically ordered into initial (1 to 75), early (76 to 150), intermediate (151 to 225), high (226 to 300), and very high (>300) experience operators for TAVR learning curve characterization. In addition, participating institutions were stratified by annual TAVR case volume into low-volume (<50), moderate-volume (50 to 100), and high-volume (>100) groups for comparative analysis. Procedural and 30-day clinical outcomes were collected and multivariate regression analysis performed for 30-day mortality and the early safety endpoint.
Results:
A total of 3,403 patients comprised the study population. On multivariate analysis, all-cause mortality was significantly higher for initial (odds ratio [OR]: 3.83; 95% confidence interval [CI]: 1.93 to 7.60), early (OR: 2.41; 95% CI: 1.51 to 5.03), and intermediate (OR: 2.53; 95% CI: 1.19 to 5.40) experience groups compared with the very high experience operators. In addition, the early safety endpoint was significantly worse for all experience groups compared with the very high experience operators. Low annual volume (<50) TAVR institutions had significantly higher all-cause 30-day mortality (OR: 2.70; 95% CI: 1.44 to 5.07) and worse early safety endpoint (OR: 1.60; 95% CI: 1.17 to 2.17) compared with the moderate- and high-volume groups. There was no difference in patient outcomes between intermediate and high annual volume groups.
Conclusions:
TAVR procedures display important learning curve characteristics with both greater procedural safety and a lower mortality when performed by experienced operators. In addition, TAVR performed at low annual volume (<50 procedures) institutions is associated with decreased procedural safety and higher patient mortality. These findings have important implications for operator training and patient care at centers performing TAVR.
More Related Videos
 09:57
Four-Dimensional Computed Tomography-Guided Valve Sizing for Transcatheter Pulmonary Valve Replacement
Published on: January 20, 2022
 07:46
Author Spotlight: Revolutionizing Remote Surgery with Augmented Reality and Robotics for Enhanced Precision and Accessibility
Published on: August 9, 2024
Related Concept Videos
 01:24
Finding Volume Using Cross-Sectional Area
 01:26
Field Procedure for Staking Out Curves
 02:00
Internal Energy
 01:31
Internal Receptors
 02:41
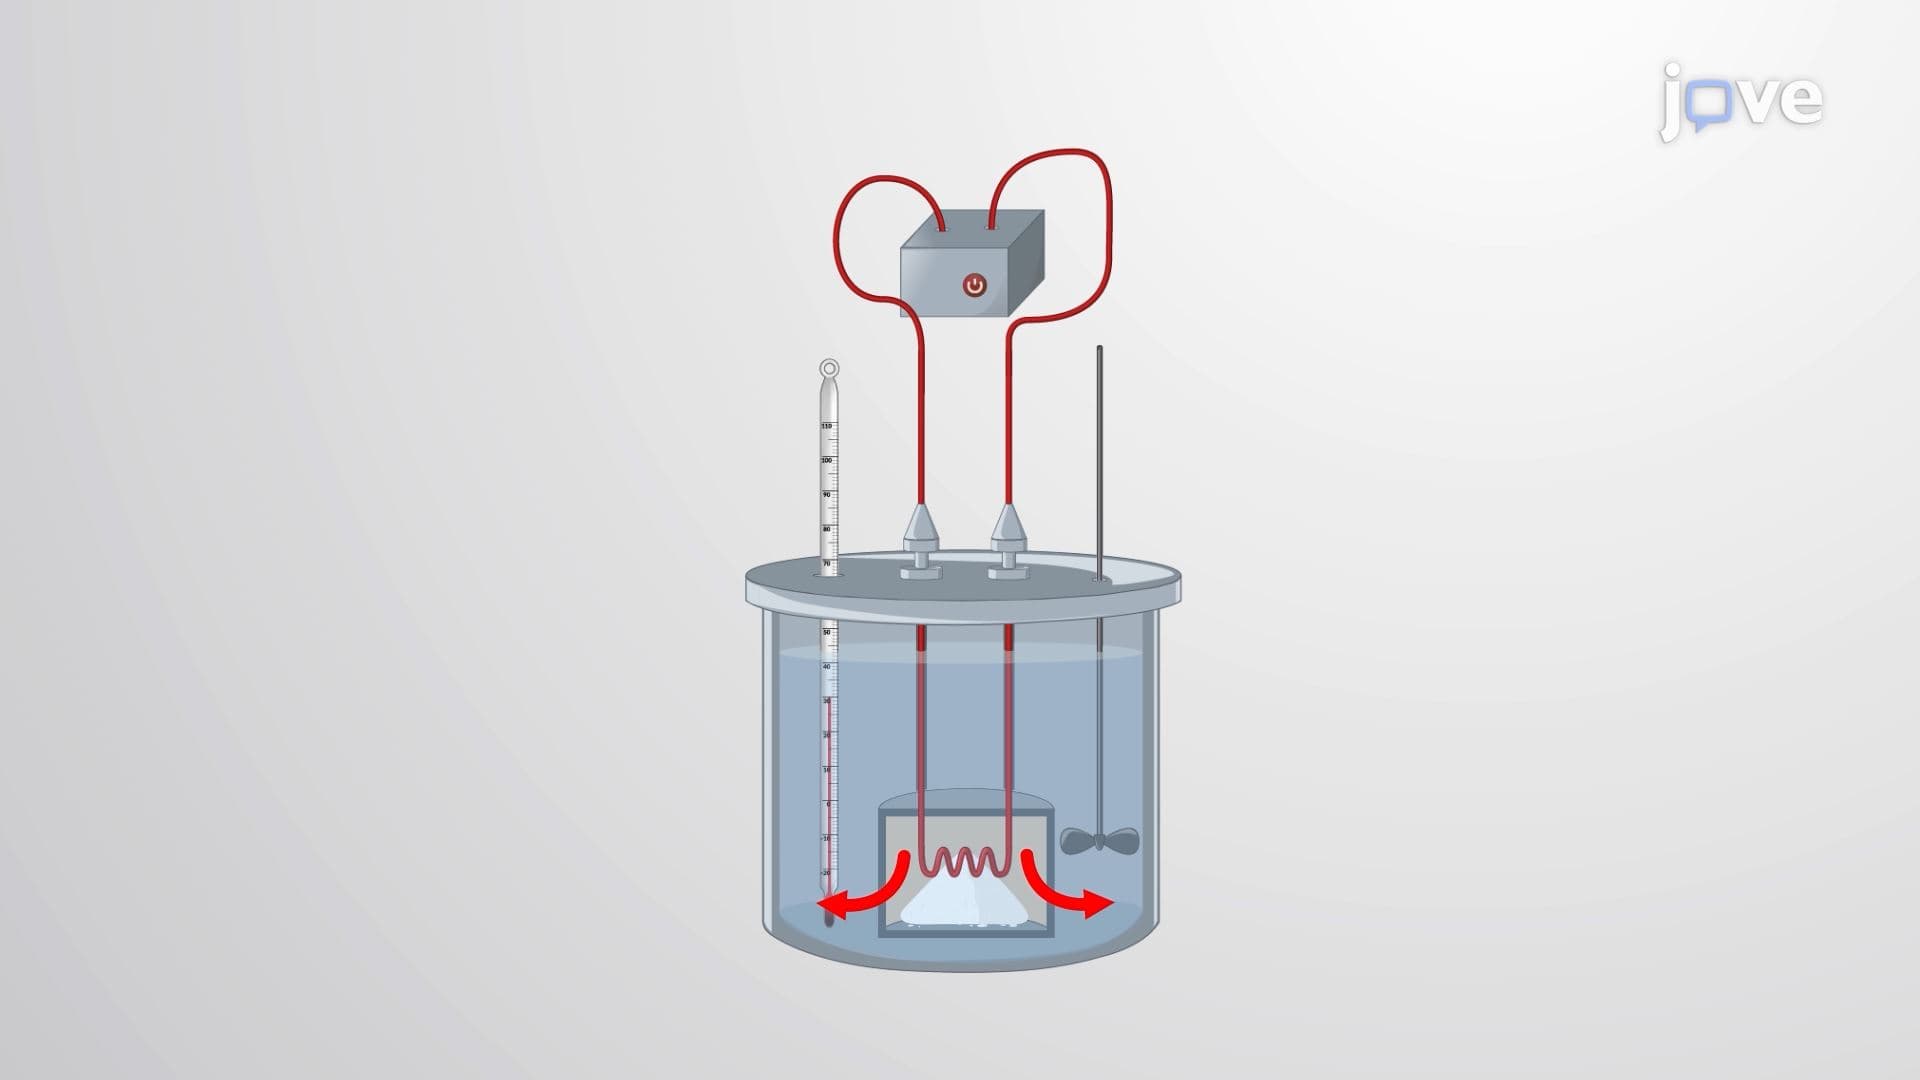
Constant Volume Calorimetry
 01:16
Heart Valves
The AV valves prevent the backflow of blood from the ventricles to the atria during ventricular contraction. These valves function with the assistance of the chordae tendineae and papillary muscles. When the ventricles are relaxed, the chordae tendineae are slack, allowing blood to flow from the atria into the...