Related Experiment Video
Updated: Feb 5, 2026


Postconditioning with Lactate-enriched Blood for Cardioprotection in ST-segment Elevation Myocardial Infarction
Published on: May 28, 2019
Network Meta-Analysis of Percutaneous Intervention-Based Revascularization Strategies for ST-Elevation Myocardial
Urooj Fatima1, Safi U Khan2, Olabisi Akanbi1
1Howard University Hospital, United States of America.

Insights
Instant complete revascularization (CR-I) in ST-elevation myocardial infarction (STEMI) patients with multi-vessel disease (MVD) reduces mortality and re-infarction compared to infarct-related artery (IRA) PCI. This strategy offers significant benefits over staged complete revascularization (CR-S) and IRA-only approaches.
Area of Science:
- Cardiology
- Interventional Cardiology
- Clinical Research
Background:
- ST-elevation myocardial infarction (STEMI) with multi-vessel disease (MVD) requires reperfusion, typically via percutaneous coronary intervention (PCI) of the culprit artery.
- Optimal timing for revascularizing non-culprit arteries in STEMI patients with MVD remains uncertain.
Purpose of the Study:
- To compare different PCI-based revascularization strategies in STEMI patients with MVD using a Bayesian network meta-analysis (NMA).
Main Methods:
- A Bayesian network meta-analysis (NMA) was conducted, including 11 randomized controlled trials (RCTs) identified from MEDLINE, EMBASE, and CENTRAL.
- The analysis calculated odds ratios and 95% credible intervals, utilizing the Surface under the Cumulative Ranking Curve (SUCRA) for intervention ranking.
- Sensitivity analyses were performed to assess the robustness of findings, particularly regarding the timing of staged interventions.
Main Results:
- Instant complete revascularization (CR-I) was associated with a 40% relative risk reduction in all-cause mortality compared to infarct-related artery (IRA) PCI.
- CR-I demonstrated superiority over staged complete revascularization (CR-S) and IRA PCI in reducing re-infarction risk.
- Both CR-I and CR-S reduced the need for repeat revascularization compared to IRA PCI, with similar rates of contrast-induced nephropathy and major bleeding across strategies.
Conclusions:
- Instant complete revascularization (CR-I) is associated with reduced all-cause mortality and re-infarction in STEMI patients with MVD compared to IRA-only PCI.
- CR-I appears to be a more effective strategy than CR-S and IRA PCI for improving clinical outcomes in this patient population.
Background:
In patients with ST elevation myocardial infarction (STEMI) and concomitant multi-vessel disease (MVD), primary percutaneous coronary intervention (PCI) of the culprit vessel is the preferred reperfusion strategy. However, optimum timing of revascularization for non-culprit artery is unclear. In this Bayesian network meta-analysis (NMA), we compared different PCI-based revascularization strategies in STEMI patients with MVD.
Methods:
11 randomized controlled trials (RCTs) were selected using MEDLINE, EMBASE and CENTRAL (Inception to September 2017). For all outcomes, median estimate of odds ratio from posterior distribution with corresponding 95% credible interval was calculated. The Surface under the Cumulative Ranking Curve (SUCRA) metric was used to estimate the relative ranking probability of each intervention. Sensitivity analysis was conducted by excluding the RCTs in which the staged intervention was performed after two weeks of the index procedure or post discharge.
Results:
In this NMA of 3172 patients, CR-I (instant complete revascularization) was associated with 40% relative risk reduction in all-cause mortality compared with IRA (infarct related artery) [0.60 (0.31-0.89)]. CR-I was superior to CR-S (staged complete revascularization) [0.42 (0.22-0.70)] and IRA [0.50(0.29-0.72)] in reducing the risk of re- infarction. Both CR-I and CR-S significantly reduced the risk of repeat revascularization compared to IRA, whereas the risk of CIN (contrast induced nephropathy) and major bleeding was similar across all interventions. Sensitivity analysis showed, that CR-I was a better strategy compared with CR-S [0.34 (0.12-0.74)] and IRA (0.60 [0.36-0.97]) in reducing all-cause mortality.
Conclusions:
In this NMA, CR-I was associated with reduction in all-cause mortality and re- infarction compared with IRA.

Related Concept Videos
 01:30
Community Based Intervention
Foundations of Community Mental Health Programs
Central to the success of community-based interventions is the...
 03:12
Freezing Point Depression and Boiling Point Elevation
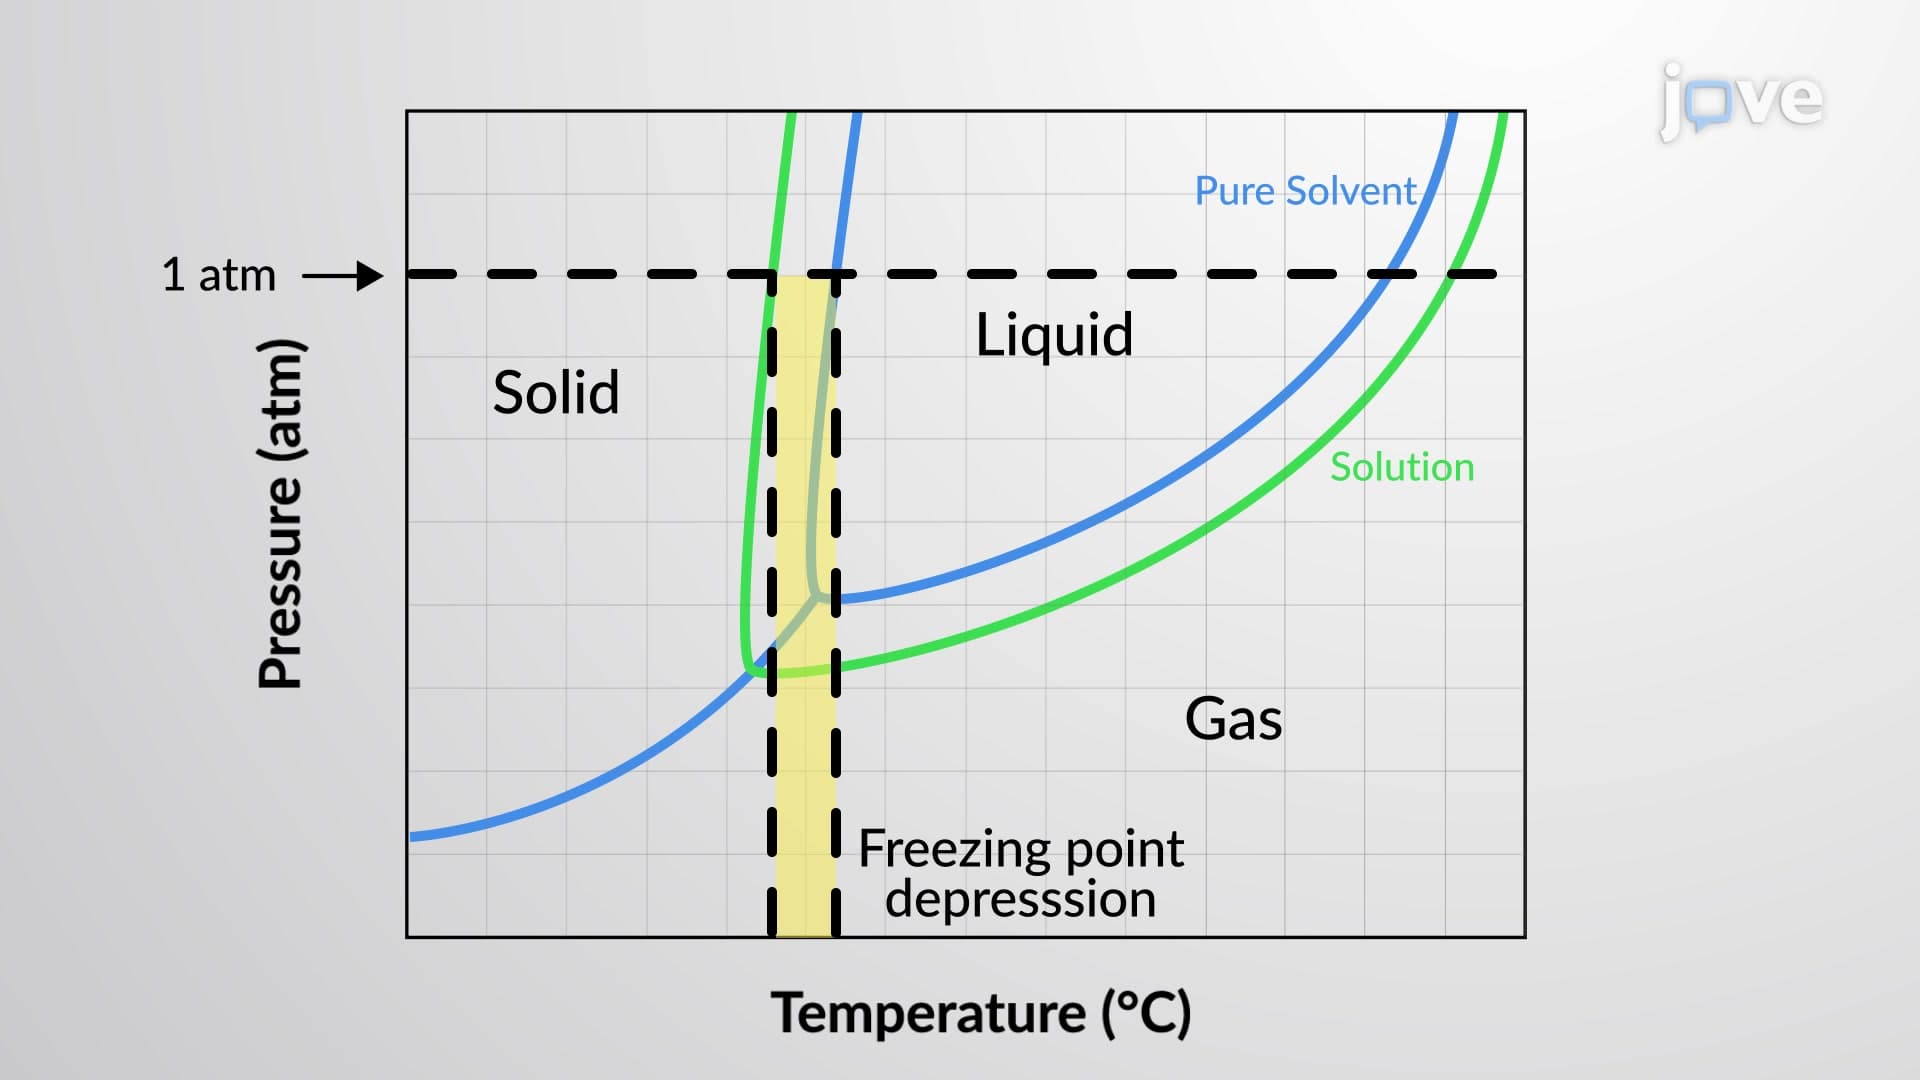
The boiling point of a liquid is the temperature at which its vapor pressure is equal to ambient atmospheric pressure. Since the vapor pressure of a solution is lowered due to the presence of nonvolatile solutes, it stands to reason that the solution’s boiling point will subsequently be increased. Vapor pressure increases with temperature, and so a solution will require a higher temperature than will pure solvent to achieve any given vapor pressure, including one...
 01:03
Nursing Interventions I: Taxonomy of Nursing Interventions
A nursing intervention is a treatment or action based on scientific concepts and knowledge from the nursing, behavioral, and physical sciences. Identifying and prioritizing nursing interventions based on the desired outcome...
 02:26
Protein Networks
These interactions can be represented through maps depicting protein-protein interaction networks, represented as nodes and edges. Nodes are circles that are representative of a protein,...
 01:29
Nursing Interventions II: Selecting and Classifying the Nursing Interventions
 01:09
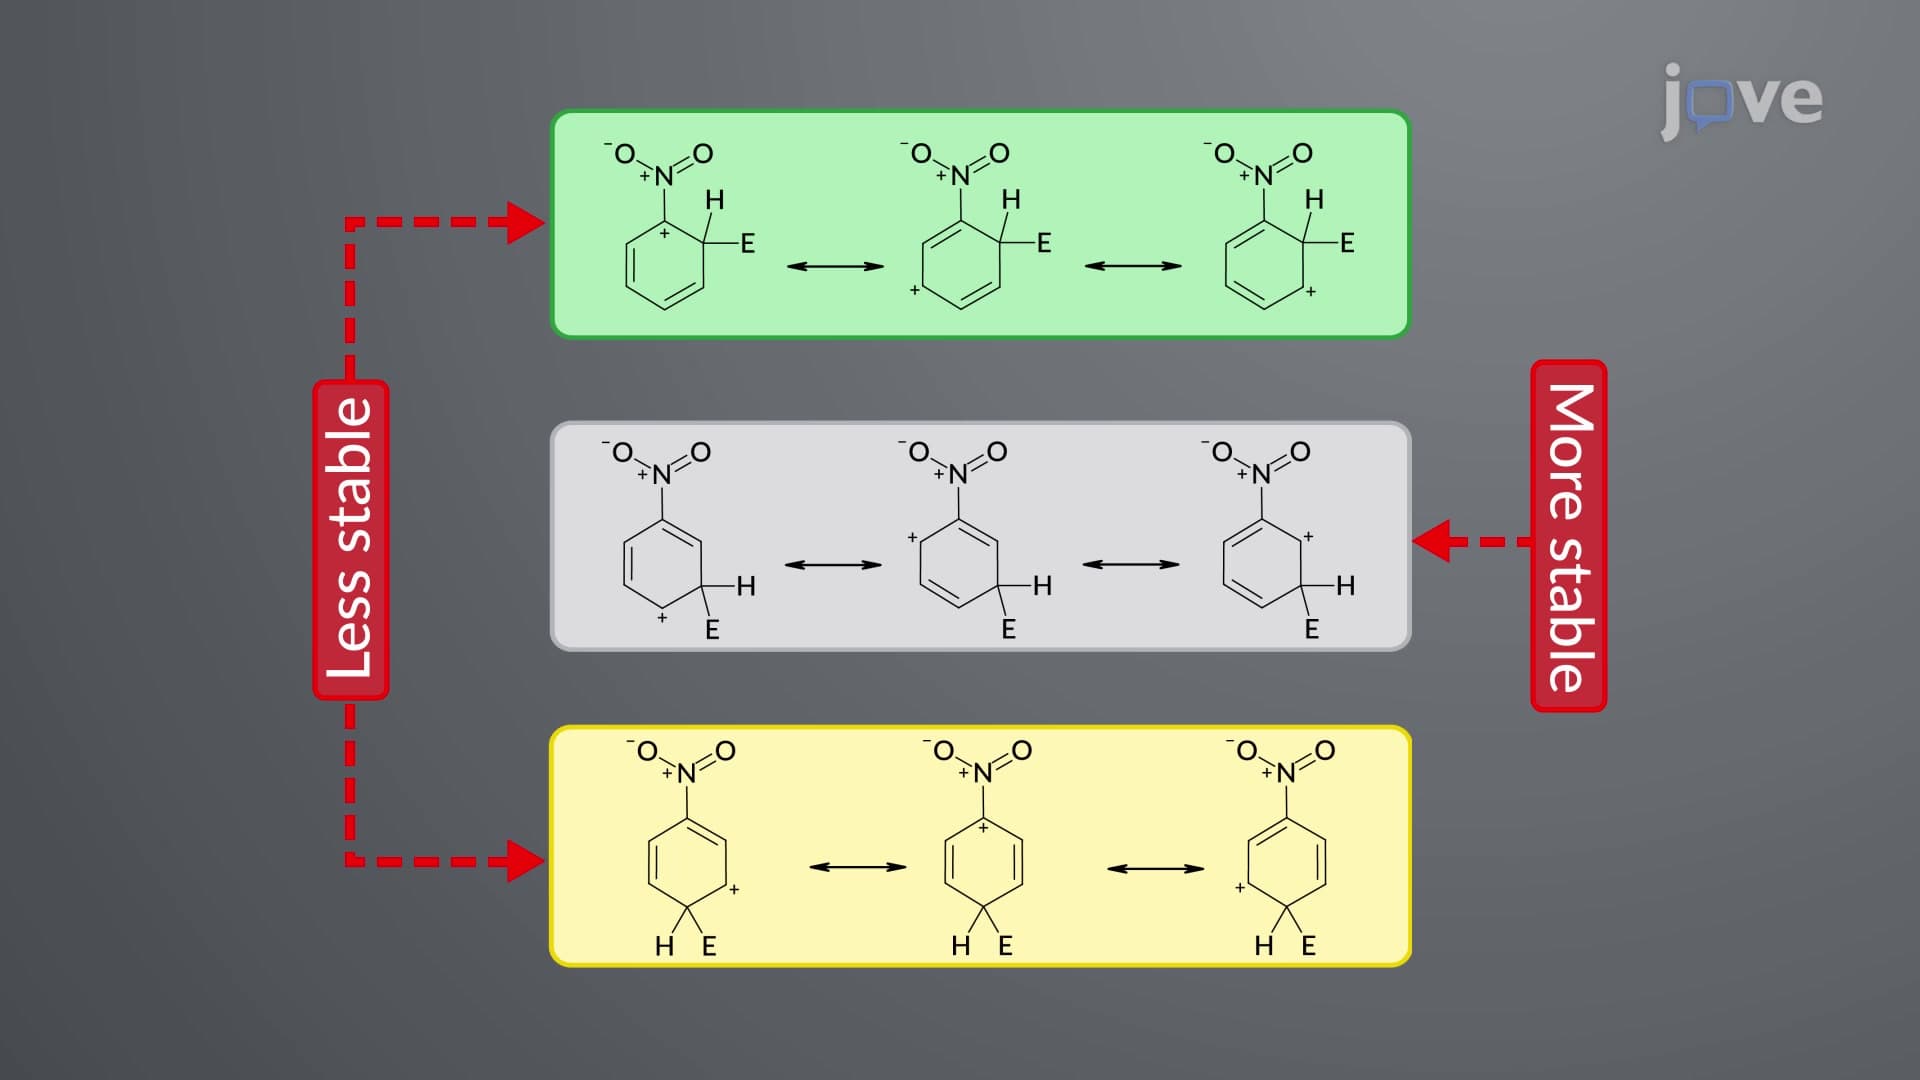
Directing Effect of Substituents: meta-Directing Groups