Related Experiment Video
Updated: Feb 5, 2026
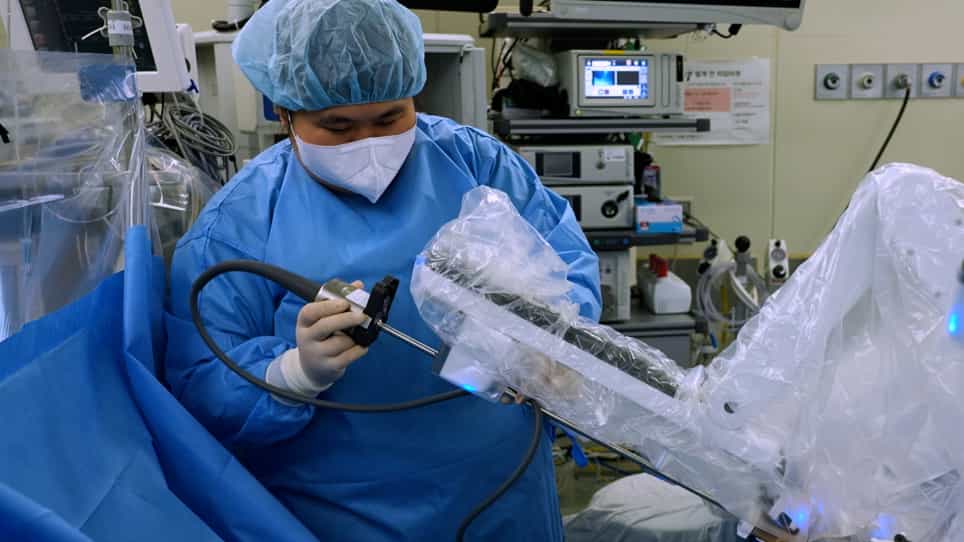

Robot-Assisted Kidney Transplantation
Published on: July 19, 2021
Transplantation of a Gitelman Syndrome Kidney Ameliorates Hypertension: A Case Report
Daniel Stewart1, Daniela Iancu2, Emma Ashton3
1South West Transplant Centre, Derriford Hospital, Plymouth, Devon.

Abstract:
Gitelman syndrome is caused by inactivating mutations of the gene that encodes the renal sodium/chloride cotransporter (NCC; encoded by SLC12A3), resulting in hypokalemia, hypomagnesemia, hypocalciuria, and metabolic alkalosis. Renal salt wasting commonly provokes mild hypotension. The paucity of previous kidney transplants from donors with known tubulopathies suggests that such conditions may be considered contraindications to donation. A 76-year-old man received a live unrelated kidney transplant from a donor with known Gitelman syndrome secondary to a pathogenic mutation of SLC12A3. Immediate graft function preceded the emergence of the Gitelman syndrome biochemical phenotype and blood pressure subsequently improved. The recipient developed unexpected hyponatremia. Potential causes are discussed, including the possibility that it paralleled the physiologic changes seen in the high-volume state of thiazide-induced hyponatremia. Transplanted kidneys are subject to nephrotoxicity from the use of calcineurin inhibitors. Acquired Gitelman syndrome may confer a potential long-term advantage to the recipient through both improved blood pressure control and protection against the calcineurin inhibitor-induced side-effect profile caused by NCC overactivation. Both the donor and recipient remain well. In conclusion, Gitelman syndrome need not preclude kidney donation and transference of the phenotype may have benefits for the recipient.

Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:26
Kidney Transplant II: Surgical Procedure
 01:16
Kidney Transplant III: Nursing Management
 01:45
Kidney Structure
 01:28
Hypertension I: Introduction
 01:29
Hypertension II: Pathophysiology