Related Experiment Video
Updated: Jan 27, 2026
Author Spotlight: Assessing Ischemic Stroke Damage Through Middle Cerebral Artery Occlusion Model
Published on: August 11, 2023
Mechanical Thrombectomy in Acute Stroke Due to Carotid Occlusion: A Series of 153 Consecutive Patients
Jose Díaz-Pérez1, Guillermo Parrilla2,3, Mariano Espinosa de Rueda4,5
1Department of Neurology, Hospital Clínico Universitario Virgen de la Arrixaca, Murcia, Spain.

Insights
Mechanical thrombectomy (MT) for carotid artery occlusion (CAO) strokes shows high recanalization rates but poor functional outcomes. Bridging therapy (BT) and primary MT (PMT) yield similar results, with symptomatic hemorrhage predicting mortality.
Area of Science:
- Neurology
- Interventional Neuroradiology
- Vascular Surgery
Background:
- Carotid artery occlusion (CAO) strokes have poor prognosis and limited response to thrombolysis.
- Mechanical thrombectomy (MT) is a treatment option, but data on CAO-specific outcomes are limited.
- Few studies compare bridging therapy (BT) and primary MT (PMT) in CAO patients.
Purpose of the Study:
- To evaluate the clinical outcomes of MT in patients with acute ischemic stroke due to CAO.
- To compare the efficacy and safety of BT versus PMT in this patient cohort.
- To identify predictors of mortality and functional outcome after MT for CAO.
Main Methods:
- Retrospective review of 153 patients with acute ischemic stroke due to CAO treated with MT (BT or PMT) within 4.5 hours of symptom onset.
- Analysis of baseline characteristics, procedural outcomes (TICI 2b-3), intrahospital mortality, symptomatic intracranial hemorrhage, and 3-month functional outcome (mRS).
- Comparison of outcomes between BT and PMT groups, and identification of independent predictors for mortality and functional outcome.
Main Results:
- High recanalization rates (TICI 2b-3) of 87.6% were achieved.
- Intrahospital mortality was 26.8%, with 26.8% achieving a favorable 3-month mRS (0-2).
- Symptomatic intracranial hemorrhage (8.5%) and high admission NIHSS were associated with worse outcomes. No significant difference was found between BT and PMT.
Conclusions:
- Mechanical thrombectomy for carotid artery occlusion strokes achieves high recanalization but is associated with poor functional outcomes.
- Bridging therapy and primary mechanical thrombectomy show similar clinical outcomes.
- Poor perfusion-CT mismatch, symptomatic hemorrhage, and high admission NIHSS are independent predictors of mortality and poor functional outcome.
Background:
Strokes due to carotid artery occlusion (CAO) are associated with bad clinical prognosis and poor response to intravenous thrombolysis. Several studies in the past have shown the benefits of mechanical thrombectomy (MT) and compared bridging therapy (BT) and primary MT (PMT) in large vessel occlusions, but only a few studies have focused on the specific population of CAO and their response to endovascular treatment.
Methods:
Retrospective review of patients treated at our center between January 2010 and June 2017 that (1) presented with acute ischemic stroke caused by CAO in the first 4.5 h since symptom onset, and (2) were treated with MT (BT or PMT). Baseline characteristics of the population, comparison between BT and PMT, intrahospital mortality, symptomatic intracranial hemorrhage, and functional outcome were investigated.
Results:
A total of 153 patients were included. Baseline characteristics: 51.6% were male, and the median age was 71 years. The most frequent risk factor was hypertension (71.9%). The main stroke etiology was atherothrombotic (40.5%). The mean admission National Institute of Health Severity Score (NIHSS) was 19, mean discharge NIHSS was 7. Isolated occlusion of the Extracranial or Intracranial Internal Carotid Artery was the most frequent occlusion location (52.3%). TICI 2b-3 was achieved in 87.6%, intrahospital mortality was 26.8%, symptomatic hemorrhage was 8.5%, and 3 months-modified Rankin Score (mRS) 0-2 was 26.8%. Definitive carotid stenting was needed in 33.3% of the cases. BT versus PMT: Patients treated with PMT presented a higher incidence of atrial fibrillation, anticoagulation, and cardioembolic stroke compared to those treated with BT. No differences in TICI 2b-3, 3 months-mRS or symptomatic hemorrhage were found between both groups. Intrahospital mortality: Poor perfusion-CT mismatch (p = 0.005), isolated Internal carotid artery location (p = 0.024), and symptomatic hemorrhage (p < 0.001) were independent predictors. Symptomatic intracranial hemorrhage: Patients with post-treatment symptomatic hemorrhage had higher intrahospital mortality (p < 0.001) and worse 3 months-mRS (p = 0.033). Functional outcome: Admission NIHSS (p = 0.012) independently predicted 3 months-mRS.
Conclusions:
In our population, patients with CAO clinically present with severe strokes. Isolated occlusions of the extra- or intracranial segments of the carotid are more frequent than tandem occlusions. Successful recanalization after thrombectomy is achieved in most of the patients, but association with favorable functional outcome is poor. Clinical evolution is similar in patients treated with PMT and BT. Intracranial symptomatic hemorrhage after treatment is associated with higher intrahospital mortality and worse 3 months-mRS. Poor perfusion-CT mismatch, symptomatic hemorrhage, and isolated CAO are independent predictors of intrahospital mortality. Admission NIHSS is an independent predictor of 3 months-mRS.


Related Concept Videos
 01:10
Resistors In Series
In a series circuit, the...
 01:17
Series Resonance
 01:17
Trigonometric Fourier series
The trigonometric Fourier series specifically expresses a periodic function with a defined period T using sine...
 01:21
Convergence of Fourier Series
The Gibbs phenomenon refers to the persistent oscillations and overshoots that occur near discontinuities...
 01:22
Series R—L Circuit Transients
Using Kirchhoff's Voltage Law (KVL) to analyze this circuit helps determine the total asymmetrical fault current, which consists...
 01:14
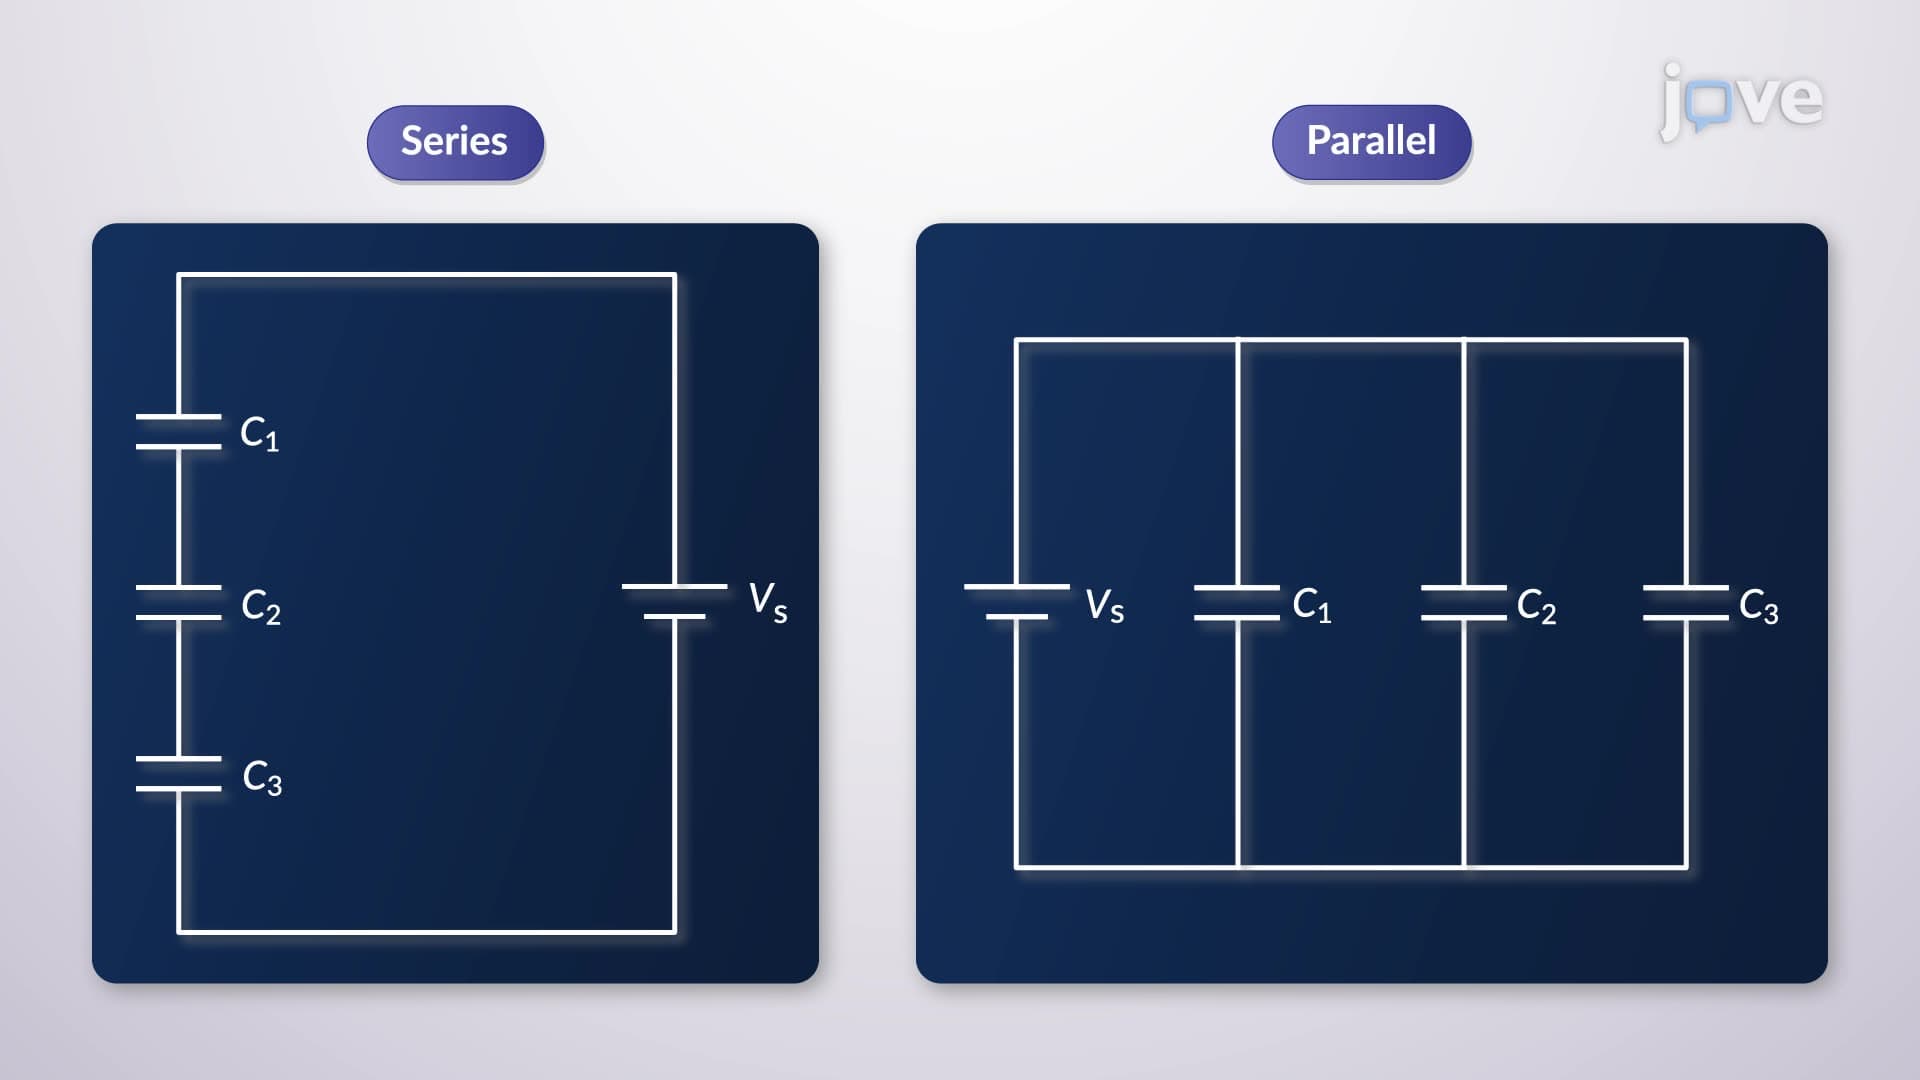
Series and Parallel Capacitors
First, consider capacitors connected in series to a battery. In this configuration, the plate connected to the battery's positive terminal develops a positive charge, while the plate attached to the negative terminal becomes negatively charged. An equal magnitude of charge is induced on the...