Related Experiment Video
Updated: Feb 5, 2026
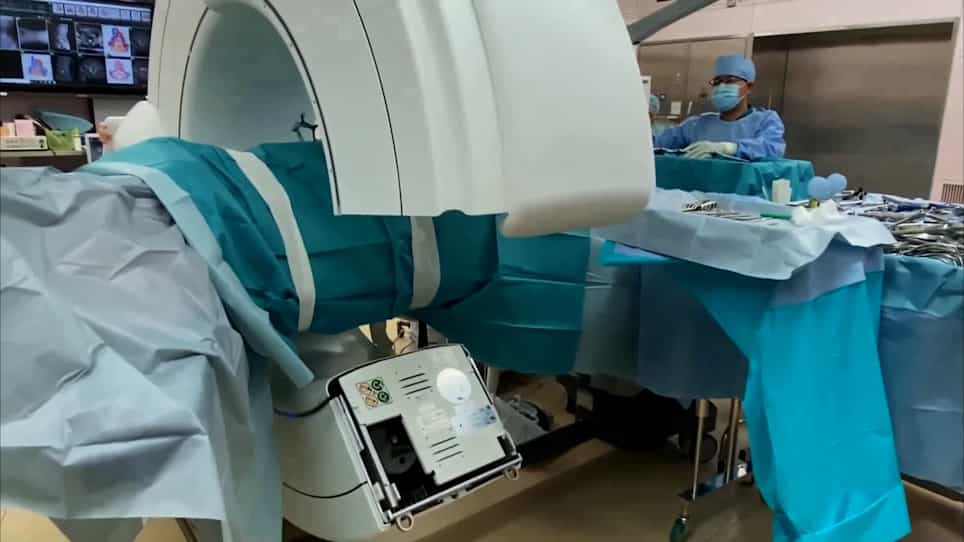

Transtubular Endoscopic Posterolateral Decompression for L5-S1 Lumbar Lateral Disc Herniation
Published on: October 14, 2022
Revised Cardiac Risk Index versus ASA Status as a Predictor for Noncardiac Events After Posterior Lumbar
Rachel S Bronheim1, Eric K Oermann2, David S Bronheim3
1Department of Medical Education, Icahn School of Medicine at Mount Sinai, New York, New York, USA.

Insights
The Revised Cardiac Risk Index (RCRI) predicts many noncardiac complications after posterior lumbar decompression (PLD). However, the American Society of Anesthesiologists (ASA) score better predicts overall noncardiac complications.
Area of Science:
- Neurosurgery
- Anesthesiology
- Cardiology
Background:
- The Revised Cardiac Risk Index (RCRI) is established for predicting cardiac events post-noncardiac surgery.
- Limited research exists on RCRI's effectiveness for noncardiac outcomes following posterior lumbar decompression (PLD).
Purpose of the Study:
- To evaluate the Revised Cardiac Risk Index's (RCRI) capability in predicting noncardiac adverse events after posterior lumbar decompression (PLD).
Main Methods:
- Utilized the American College of Surgeons National Surgical Quality Improvement Program database (2006-2014).
- Identified patients undergoing PLD.
- Employed multivariate and receiver operating characteristic analyses to assess RCRI associations with postoperative complications.
Main Results:
- RCRI=1 and RCRI=2 cohorts predicted numerous complications, including unplanned intubation, renal insufficiency, acute renal failure, urinary tract infection (UTI), sepsis, and readmission.
- RCRI=3 cohort strongly predicted unplanned intubation, prolonged ventilation, acute renal failure, and UTI.
- RCRI demonstrated poor discriminative ability (AUC=0.623) for composite noncardiac complications, while ASA status showed fair ability (AUC=0.770).
Conclusions:
- The RCRI predicts various noncardiac complications after PLD.
- The American Society of Anesthesiologists (ASA) score offers superior discriminative ability for composite noncardiac complications compared to RCRI.
- Integrating RCRI into preoperative risk assessment may help reduce patient morbidity and mortality after lumbar decompression.
Background:
The Revised Cardiac Risk Index (RCRI) was designed to predict risk for cardiac events after noncardiac surgery. However, there is a paucity of literature that directly addresses the relationship between RCRI and noncardiac outcomes after posterior lumbar decompression (PLD). The objective of this study is to determine the ability of RCRI to predict noncardiac adverse events after PLD.
Methods:
The American College of Surgeons National Surgical Quality Improvement Program was used to identify patients undergoing PLD from 2006 to 2014. Multivariate and receiver operating characteristic analysis was used to identify associations between RCRI and postoperative complications.
Results:
A total of 52,066 patients met the inclusion criteria. Membership in the RCRI=1 cohort independently predicted unplanned intubation, ventilation >48 hours, progressive renal insufficiency, acute renal failure, urinary tract infection (UTI), sepsis, septic shock, and readmission. Membership in the RCRI=2 cohort independently predicted for superficial surgical site infection, pneumonia, unplanned intubation, ventilation >48 hours, bleeding transfusion, progressive renal insufficiency, acute renal failure, UTI, sepsis, septic shock, and readmission. Membership in the RCRI=3 cohort independently predicted unplanned intubation (odds ratio [OR], 11.8), ventilation >48 hours (OR, 23.0), acute renal failure (OR, 84.5), and UTI (OR, 3.6). RCRI had a poor discriminative ability (DA) (area under the curve = 0.623), and American Society of Anesthesiologists status had a fair DA (area under the curve = 0.770) to predict a composite of noncardiac complications.
Conclusions:
RCRI was predictive of a wide range of noncardiac complications after PLD but had a diminished DA to predict a composite of any noncardiac complication than did American Society of Anesthesiologists score. Consideration of the RCRI as a component of preoperative surgical risk stratification can minimize patient morbidity and mortality after lumbar decompression.
More Related Videos
 08:28
Methods for ECG Evaluation of Indicators of Cardiac Risk, and Susceptibility to Aconitine-induced Arrhythmias in Rats Following Status Epilepticus
Published on: April 5, 2011
 05:17
Author Spotlight: Scope of LE-ULBD as a Safe, Effective, and Minimally Invasive Approach to Treat Lumbar Spinal Stenosis
Published on: February 9, 2024
Related Concept Videos
 01:12
Relative Risk
 01:26
Marcia's Theory of Identity Status
 01:28
Integration of Synaptic Events
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:21
Schwarzschild Radius and Event Horizon
The minimum speed required to launch a projectile from the surface of an object to which it is gravitationally bound so that it eventually escapes the object’s gravitational field is called the escape velocity. The escape velocity is independent of the mass of the object. Merging the idea of escape...
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...