Related Experiment Video
Updated: Feb 3, 2026


Isolation and Culture of Resident Cardiac Macrophages from the Murine Sinoatrial and Atrioventricular Node
Published on: May 7, 2021
Outcome of Cardiac Sarcoidosis Presenting With High-Grade Atrioventricular Block
Hanna-Kaisa Nordenswan1, Jukka Lehtonen1, Kaj Ekström1
1Heart and Lung Center (H.-K.N., J.L., K.E., R.K., P.S., M.K.).

Insights
Cardiac sarcoidosis with high-grade atrioventricular block (AVB) carries a significant risk of sudden cardiac death. Early implantation of an intracardiac cardioverter defibrillator is recommended for patients needing permanent pacing.
Area of Science:
- Cardiology
- Electrophysiology
- Immunology
Background:
- Symptomatic high-grade atrioventricular block (AVB) is a primary manifestation of cardiac sarcoidosis.
- The risk of fatal arrhythmias, particularly in lone AVB, is not well-established.
- Current recommendations favor intracardiac cardioverter defibrillator (ICD) over pacemakers for cardiac sarcoidosis.
Purpose of the Study:
- To analyze presentations, left ventricular (LV) function, and arrhythmias in cardiac sarcoidosis patients.
- To determine the incidence of sudden cardiac death and ventricular arrhythmias in relation to AVB severity and LV dysfunction.
- To evaluate the risk stratification for fatal arrhythmias in cardiac sarcoidosis.
Main Methods:
- Utilized the Myocardial Inflammatory Diseases in Finland Study Group Registry (1988-2015).
- Analyzed 325 cardiac sarcoidosis cases, focusing on 143 patients with high-grade AVB (Mobitz II or third degree) without other cardiac causes.
- Assessed LV function, ventricular arrhythmias, and outcomes including sudden cardiac death during a median 2.8-year follow-up.
Main Results:
- Of 143 patients, 90 presented with lone AVB, 29 with nonsevere LV dysfunction, and 20 with severe LV dysfunction or ventricular tachycardia.
- The 5-year composite incidence of arrhythmic events was 56% in severe LV dysfunction/VT group, 24% in nonsevere LV dysfunction group, and 24% in lone AVB group.
- The 5-year incidence of sudden cardiac death was 34% in the severe LV dysfunction/VT group, 14% in the nonsevere LV dysfunction group, and 9% in the lone AVB group.
Conclusions:
- Cardiac sarcoidosis with high-grade AVB presents a substantial risk of sudden cardiac death, irrespective of LV dysfunction or ventricular tachycardia.
- The findings support the consensus recommendation for ICD implantation in patients with cardiac sarcoidosis requiring permanent pacing.
- Risk stratification based on LV function and arrhythmias is crucial for managing these patients.
Background:
Symptomatic high-grade atrioventricular block (AVB) is the most common and often the only presenting manifestation (lone AVB) of cardiac sarcoidosis. Implantation of an intracardiac cardioverter defibrillator instead of a pacemaker is recommended, but the true risk of fatal arrhythmia, one incident to lone AVB in particular, remains poorly known.
Methods:
We used Myocardial Inflammatory Diseases in Finland Study Group Registry to analyze the presentations, left ventricular (LV) function, pacemaker therapy, and ventricular arrhythmias in cardiac sarcoidosis. From year 1988 to 2015, altogether 325 cases of cardiac sarcoidosis were diagnosed in Finland. Of them, 143 patients (112 women, mean age 52 years) presented with Mobitz II second degree or third degree AVB in the absence of other explanatory cardiac disease.
Results:
Concomitant with AVB at presentation, 20 patients had either ventricular tachycardia or severe LV dysfunction with ejection fraction <35% and 29 patients had nonsevere LV dysfunction (ejection fraction, 35%-50%) while 90 patients presented with AVB alone. During a median of 2.8 years' follow-up, 23 sudden cardiac deaths (fatal or aborted) and 19 ventricular tachycardias were recorded as arrhythmic end point events. Their composite 5-year incidence (95% confidence interval) was 56% (36%-88%) in the AVB subgroup with ventricular tachycardia or severe LV dysfunction versus 24% (12%-49%) in the subgroup with nonsevere LV dysfunction and 24% (15%-38%) with lone AVB ( P=0.019). The 5-year incidence of sudden cardiac death was 34% (16%-71%), 14% (6%-35%), and 9% (4%-22%) in the respective subgroups ( P=0.060).
Conclusions:
The risk of sudden cardiac death is significant in cardiac sarcoidosis presenting with high-grade AVB with or without ventricular tachycardia or LV dysfunction. The consensus recommendation to implant an intracardiac cardioverter defibrillator whenever permanent pacing is needed seems well-founded.
More Related Videos
 05:16
Whole-Mount Immunofluorescence Staining, Confocal Imaging and 3D Reconstruction of the Sinoatrial and Atrioventricular Node in the Mouse
Published on: December 22, 2020
 07:02
Utilizing the Modified T-Maze to Assess Functional Memory Outcomes After Cardiac Arrest
Published on: January 5, 2018
Related Concept Videos
 01:19
Graded Potential
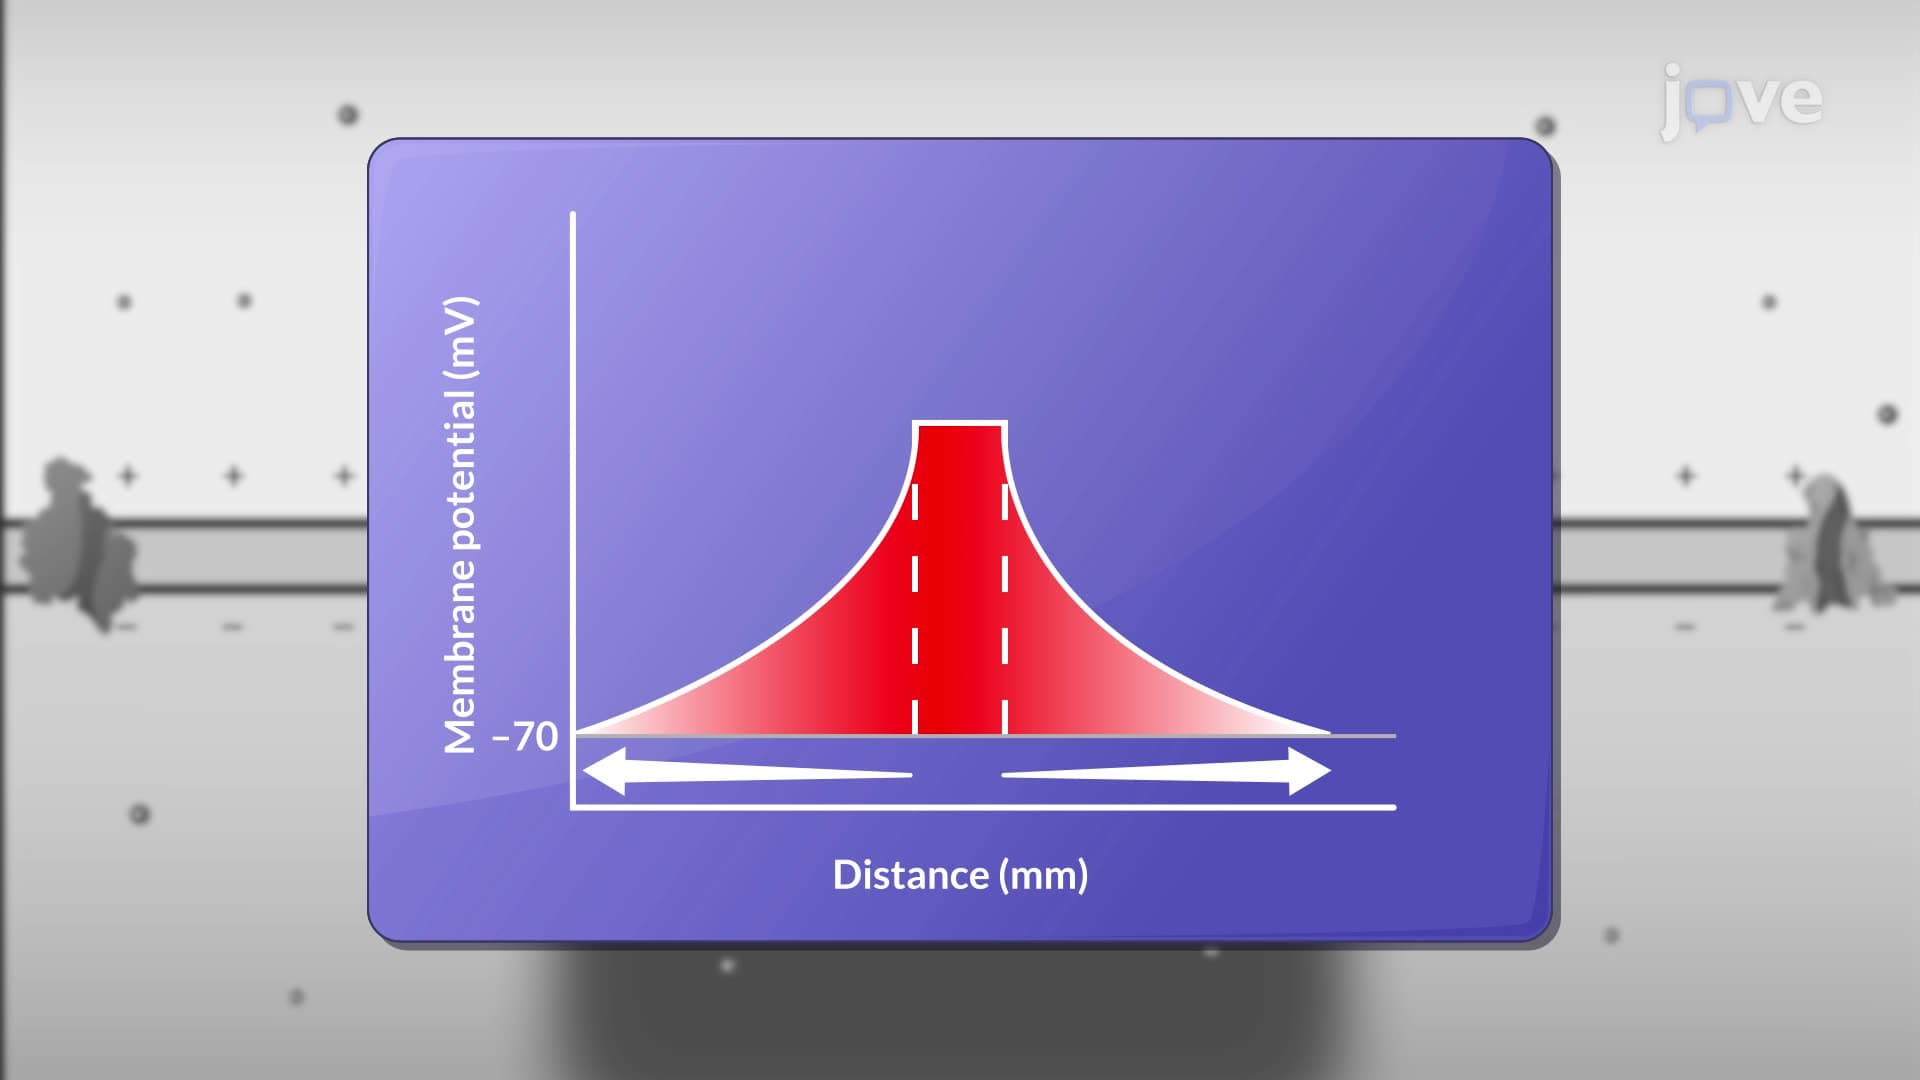
Graded potentials fall into two categories: depolarizing and hyperpolarizing. Depolarizing graded potentials typically occur when sodium (Na+) or...
 02:24
Predicting Reaction Outcomes
 01:13
Outcomes of Glycolysis
Cellular respiration can occur aerobically (with oxygen) or anaerobically (without oxygen). In the presence of oxygen, cellular respiration starts with glycolysis and continues with pyruvate...
 01:15
Types of Aggregate Grading
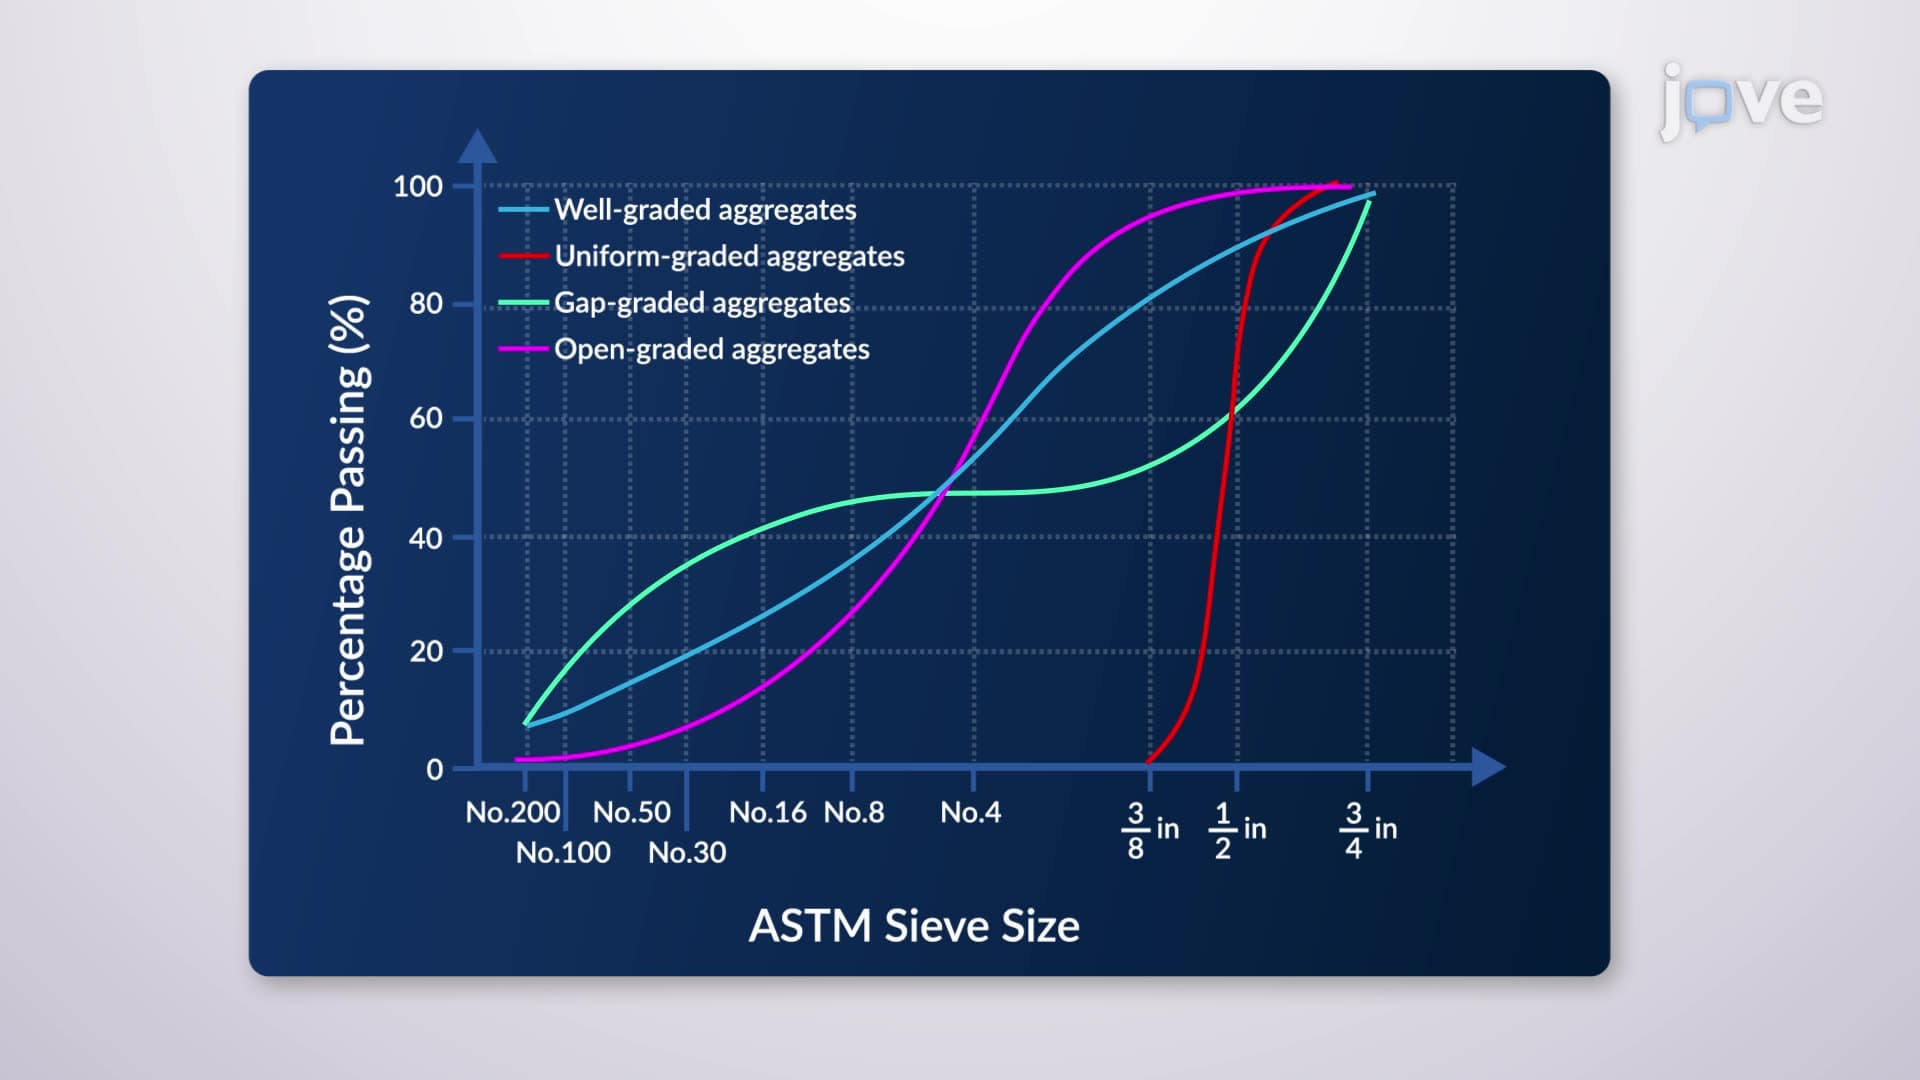
Well-graded aggregates include a complete range of necessary size fractions that fit together to create a dense matrix with minimal voids, represented by a smooth, continuous gradation curve. This type of grading ensures good...
 01:19
Sieve Analysis and Grading Curves
 01:11
Guidelines for Writing Outcome
Patient outcomes reflect the patient's response to the goal rather than what the nurse aims to achieve. Terminology should be observable and measurable to avoid the reader's interpretation. The desired outcome should be realistic and achievable in the designated care timeframe. Expected outcomes should align with adjunctive therapies. The outcome should enhance care...