Related Experiment Video
Updated: Feb 3, 2026

Preclinical Model of Hind Limb Ischemia in Diabetic Rabbits
Published on: June 2, 2019
Outcomes after first-time lower extremity revascularization for chronic limb-threatening ischemia in
Jeremy D Darling1, Thomas F X O'Donnell2, Sarah E Deery2
1Division of Vascular and Endovascular Surgery, Beth Israel Deaconess Medical Center, Harvard Medical School, Boston, Mass.

Insights
For diabetic patients with chronic limb-threatening ischemia, a bypass graft (BPG) strategy showed similar short-term outcomes but lower rates of restenosis and reintervention compared to percutaneous transluminal angioplasty/stenting (PTA/S). This suggests BPG may be superior for select patients.
Area of Science:
- Vascular Surgery
- Diabetic Limb Complications
- Revascularization Strategies
Background:
- Open surgical bypass historically offered durable repair for diabetic patients with chronic limb-threatening ischemia (CLTI).
- Long-term outcomes of initial revascularization strategies in insulin-dependent diabetes mellitus (IDDM) patients with CLTI remain unclear in the current endovascular era.
Purpose of the Study:
- To compare long-term outcomes of first-time infrainguinal bypass graft (BPG) versus percutaneous transluminal angioplasty/stenting (PTA/S) for CLTI in patients with IDDM.
- To evaluate differences in wound healing, restenosis, reintervention, amputation, and mortality rates between BPG and PTA/S.
Main Methods:
- Retrospective review of 655 infrainguinal revascularizations (316 BPG, 339 PTA/S) in 580 IDDM patients with CLTI (2005-2014).
- Comparison of outcomes including wound healing, restenosis, reintervention, amputation, and mortality.
- Statistical analyses included chi-squared, Kaplan-Meier, Cox regression, and propensity score inverse probability weighting.
Main Results:
- BPG patients had longer hospital stays but similar perioperative complications and mortality compared to PTA/S.
- BPG-first strategy was associated with significantly lower unadjusted rates of incomplete wound healing, restenosis, and reintervention.
- Adjusted analyses confirmed PTA/S-first intervention was linked to higher risks of restenosis and reintervention.
Conclusions:
- In IDDM patients with CLTI, a bypass-first strategy yields similar 30-day outcomes but reduced rates of restenosis and reintervention.
- A bypass-first approach may be optimal for carefully selected, anatomically suitable IDDM patients requiring revascularization for pedal ischemia.
Objective:
Historically, open surgical bypass provided a durable repair among diabetic patients with chronic limb-threatening ischemia (CLTI). In the current endovascular era, however, the difference in long-term outcomes between first-time revascularization strategies among patients with insulin-dependent diabetes mellitus (IDDM) is poorly understood.
Methods:
We reviewed the records of all patients with IDDM undergoing a first-time infrainguinal bypass graft (BPG) or percutaneous transluminal angioplasty with or without stenting (PTA/S) for CLTI at our institution from 2005 to 2014. We defined IDDM as use of chronic insulin administration at baseline to control blood glucose levels and recorded the most recent glycated hemoglobin value available within 3 months before the procedure and fasting blood glucose level on the day of the procedure. We compared rates of wound healing, restenosis, reintervention, major amputation, and mortality between BPG and PTA/S in our population using χ2, Kaplan-Meier, and Cox regression analyses. As a sensitivity analysis, we calculated propensity scores and employed inverse probability weighting to account for nonrandom assignment to BPG vs PTA/S.
Results:
Of 2869 infrainguinal revascularizations from 2005 to 2014, 655 limbs (316 BPG, 339 PTA/S) in 580 patients fit our criteria and underwent a first-time revascularization for CLTI. Patients undergoing BPG, compared with PTA/S, were similar in age (69 vs 68 years; P = .55), had similar rates of tissue loss (87% vs 91%; P = .07) and dialysis dependence (26% vs 28%; P = .55), were less likely to be hypertensive (84% vs 92%; P < .001), and were more likely to be current smokers (21% vs 14%; P = .02). There were no differences between BPG and PTA/S patients in mean glycated hemoglobin levels (8.1% vs 8.0%; P = .51) or mean fasting blood glucose levels (158 vs 150 mg/dL; P = .18). Although total hospital length of stay was significantly longer among BPG patients (11 vs 8 days; P < .001), perioperative complications did not differ, including acute kidney injury (19% vs 23%; P = .24), hematoma (6.0% vs 3.8%; P = .20), acute myocardial infarction (1.3% vs 2.1%; P = .43), and mortality (3.8% vs 3.0%; P = .55). BPG-first patients had significantly lower unadjusted 6-month rates of incomplete wound healing (49% vs 57%) and 5-year rates of restenosis (53% vs 72%) and reintervention (47% vs 58%; all P < .05). After adjustment, multivariable analysis suggested PTA/S-first intervention to be significantly associated with higher risk of restenosis (hazard ratio, 1.9; 95% confidence interval, 1.3-2.7) and reintervention (1.9 [1.2-2.7]). These results remained robust after inverse probability weighting.
Conclusions:
Among patients with IDDM and CLTI, a bypass-first strategy is associated with similar 30-day outcomes and lower restenosis and reintervention rates. These data suggest that a bypass-first approach may best serve appropriately selected, anatomically suitable patients with IDDM and pedal ischemia that requires revascularization.
More Related Videos
 03:55
Author Spotlight: Enhancing Grasping Abilities for Hemiplegic Patients with Flexible Robotic Limbs
Published on: October 27, 2023
 07:25
Predicting Amputation using Local Circulating Mononuclear Progenitor Cells in Angioplasty-treated Patients with Critical Limb Ischemia
Published on: September 22, 2020
Related Concept Videos
 01:20
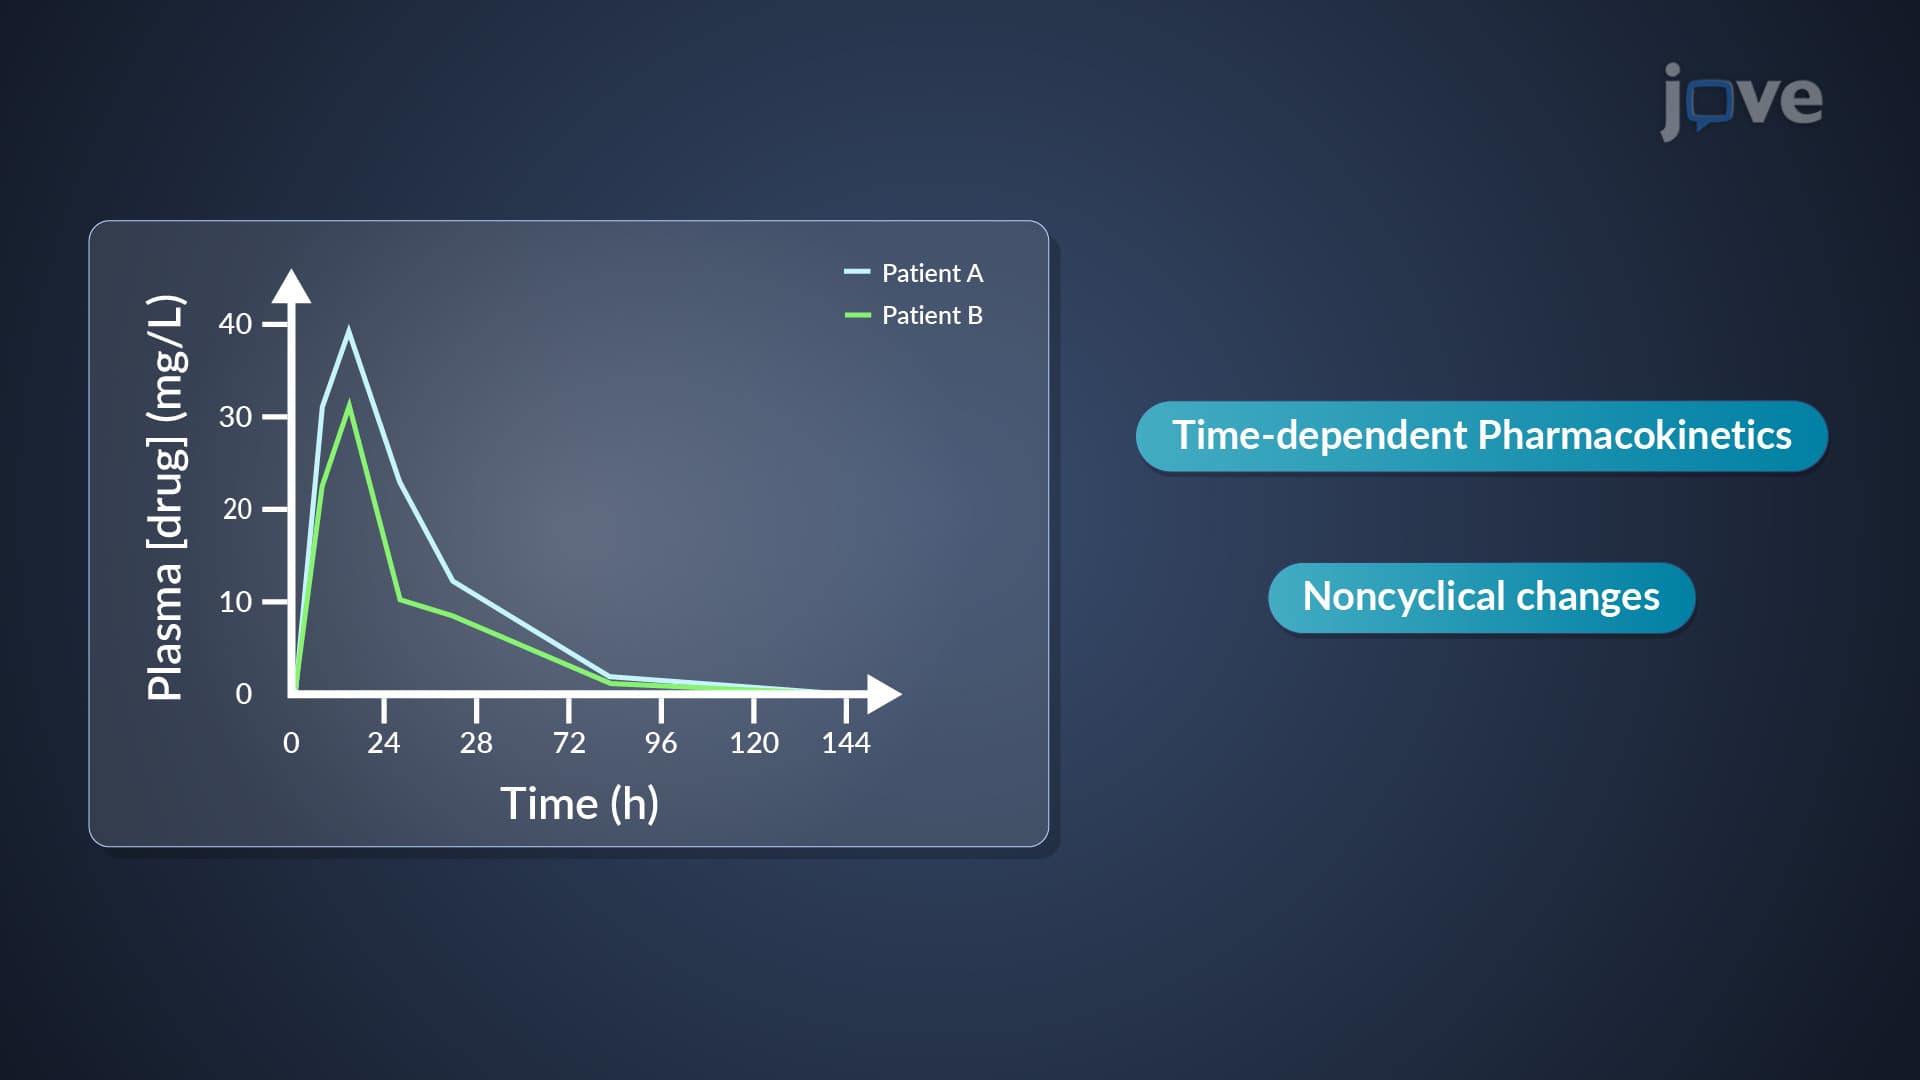
Chronopharmacokinetics: Time-Dependent Pharmacokinetics
Time-dependent pharmacokinetics refers to non-cyclical changes in drug rate processes over a period of time. It can lead to nonlinear pharmacokinetics, where the relationship between drug concentration and time is not proportional. Non-cyclical...
 02:39
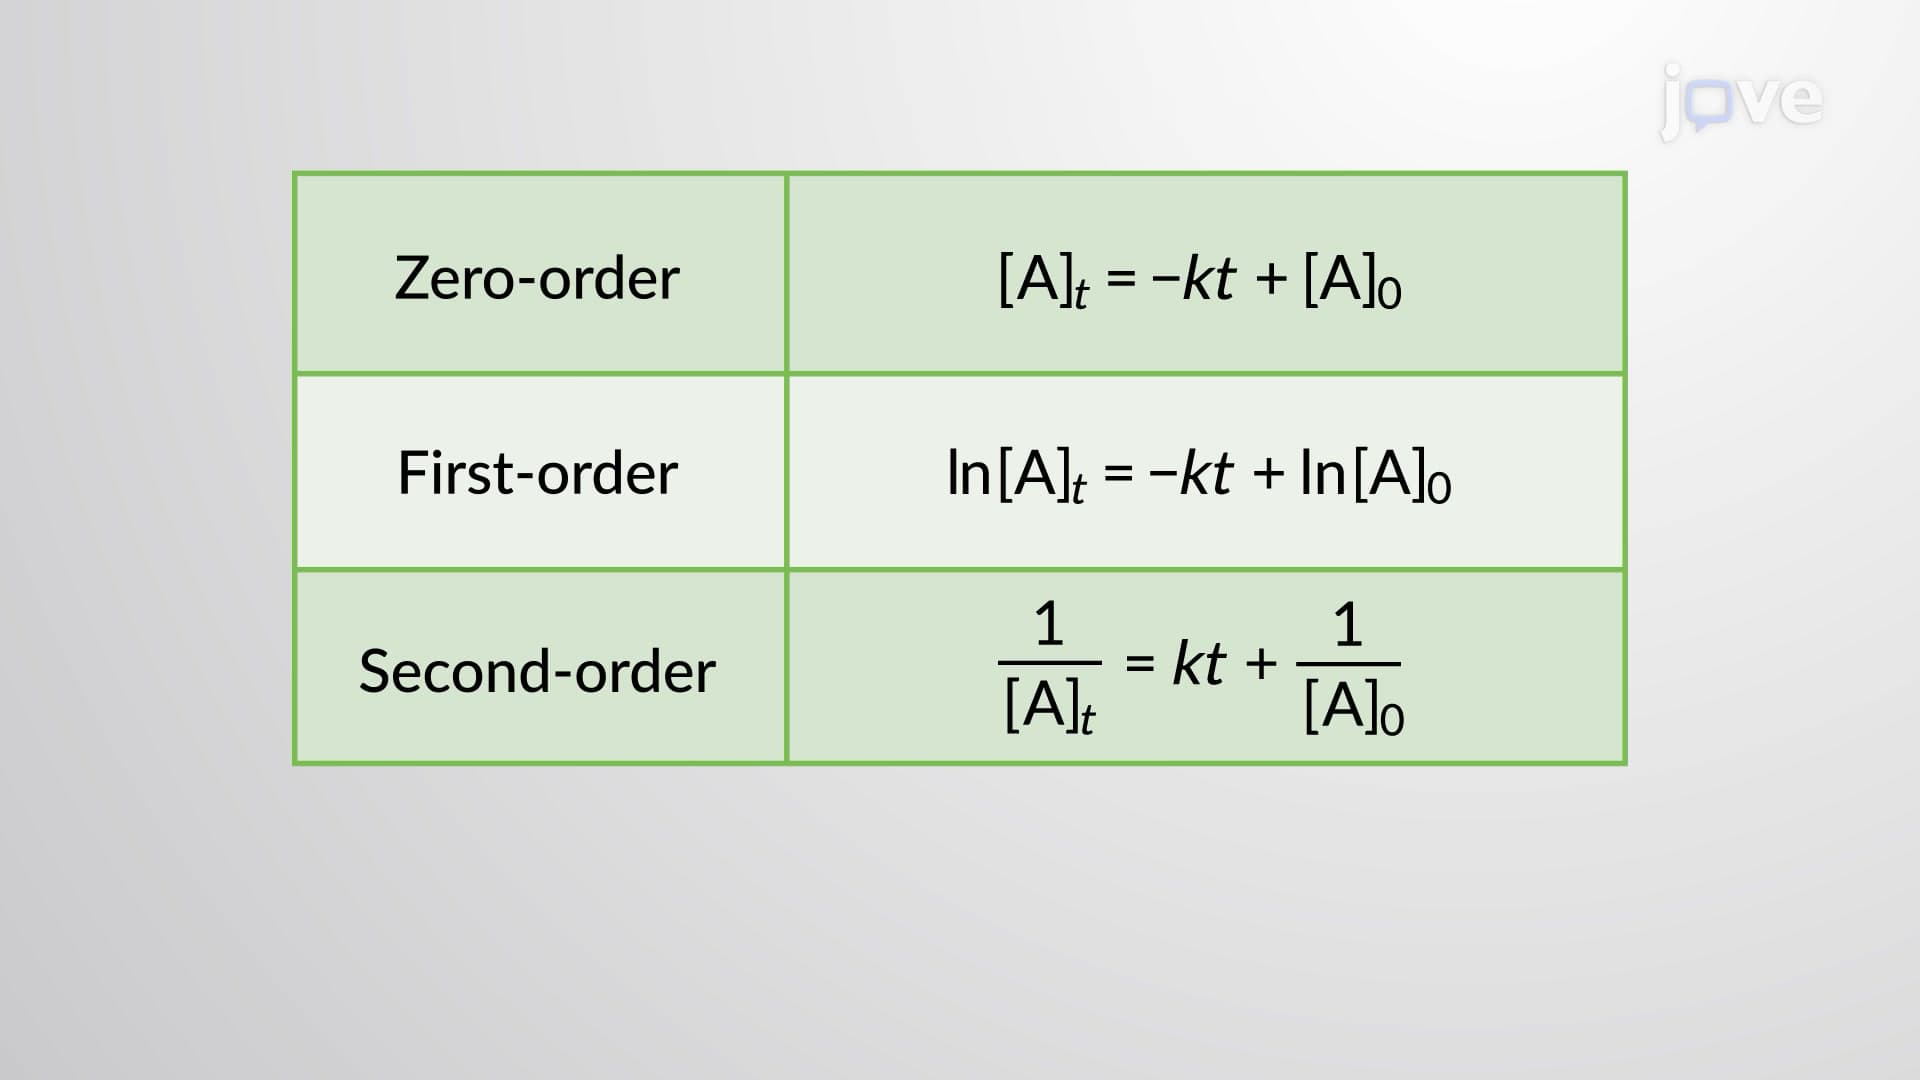
The Integrated Rate Law: The Dependence of Concentration on Time
 02:24
Predicting Reaction Outcomes
 01:13
Outcomes of Glycolysis
Cellular respiration can occur aerobically (with oxygen) or anaerobically (without oxygen). In the presence of oxygen, cellular respiration starts with glycolysis and continues with pyruvate...
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility,...
 01:22
Absolute and Local Extreme Values