Related Experiment Video
Updated: Feb 2, 2026


Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Robotic total meso-rectal excision for rectal cancer: A systematic review following the publication of the ROLARR
Katie Jones1, Mohamed G Qassem1, Parv Sains1
1Department of General and Laparoscopic Colorectal Surgery, Brighton and Sussex University Hospitals NHS Trust, the Royal Sussex County Hospital, Brighton, West Sussex BN2 5BE, United Kingdom.

Aim:
To compare outcomes in patients undergoing rectal resection by robotic total meso-rectal excision (RTME) vs laparoscopic total meso-rectal excision (LTME).
Methods:
Standard medical electronic databases such as PubMed, MEDLINE, EMBASE and Scopus were searched to find relevant articles. The data retrieved from all types of included published comparative trials in patients undergoing RTME vs LTME was analysed using the principles of meta-analysis. The operative, post-operative and oncological outcomes were evaluated to assess the effectiveness of both techniques of TME. The summated outcome of continuous variables was expressed as standardized mean difference (SMD) and dichotomous data was presented in odds ratio (OR).
Results:
One RCT (ROLARR trial) and 27 other comparative studies reporting the non-oncological and oncological outcomes following RTME vs LTME were included in this review. In the random effects model analysis using the statistical software Review Manager 5.3, the RTME was associated with longer operation time (SMD, 0.46; 95%CI: 0.25, 0.67; z = 4.33; P = 0.0001), early passage of first flatus (P = 0.002), lower risk of conversion (P = 0.00001) and shorter hospitalization (P = 0.01). The statistical equivalence was seen between RTME and LTME for non-oncological variables like blood loss, morbidity, mortality and re-operation risk. The oncological variables such as recurrence (P = 0.96), number of harvested nodes (P = 0.49) and positive circumferential resection margin risk (P = 0.53) were also comparable in both groups. The length of distal resection margins was similar in both groups.
Conclusion:
RTME is feasible and oncologically safe but failed to demonstrate any superiority over LTME for many surgical outcomes except early passage of flatus, lower risk of conversion and shorter hospitalization.
More Related Videos
 05:32
Povidone Iodine Rectal Preparation at Time of Prostate Needle Biopsy is a Simple and Reproducible Means to Reduce Risk of Procedural Infection
Published on: September 21, 2015
 05:45
Diagnosis of Hirschsprung's Disease by Immunostaining Rectal Suction Biopsies for Calretinin, S100 Protein and Protein Gene Product 9.5
Published on: April 26, 2019
Related Concept Videos
 01:27
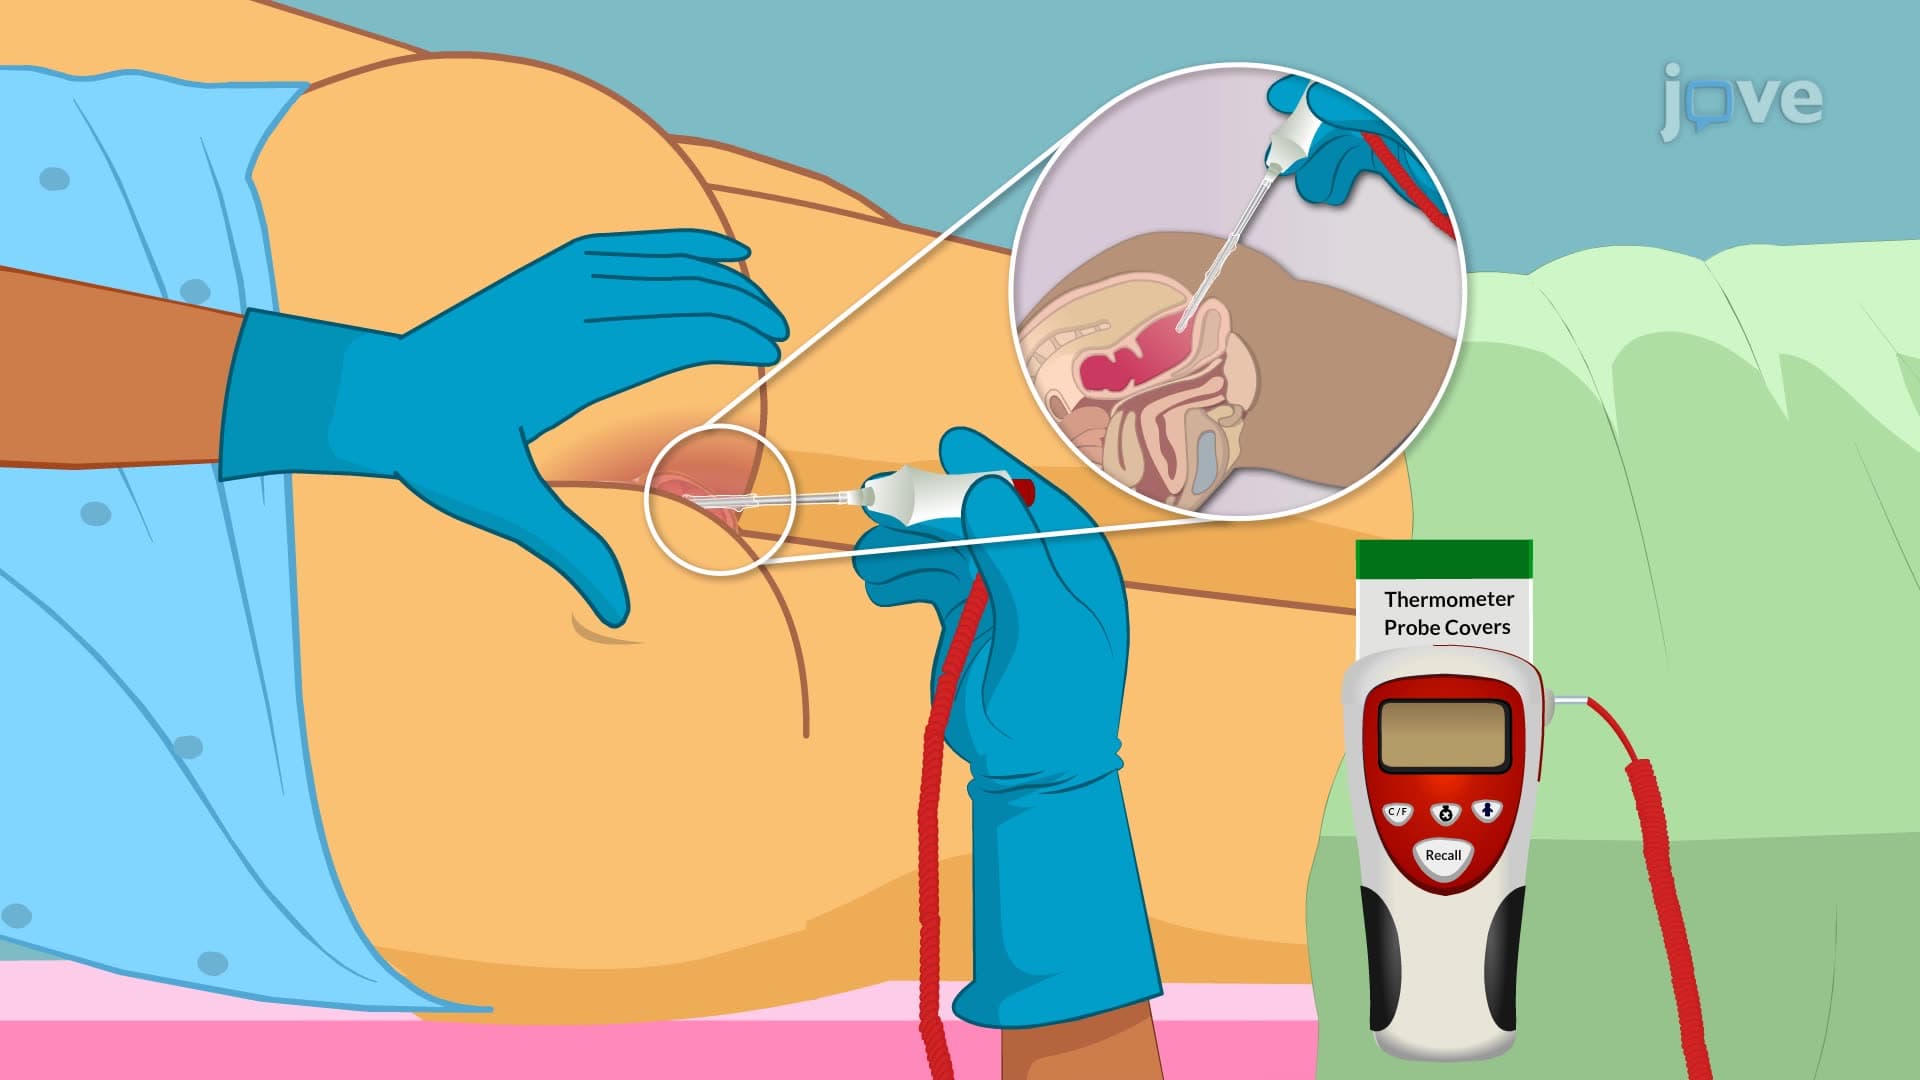
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 01:54
Base Excision Repair
The first step of...
 01:10
Review and Preview
Percentiles are a type of fractile that partition data into...
 01:13
Review and Preview
 01:08
Nucleotide Excision Repair
 01:11
Clinical Trials: Overview