Related Experiment Video
Updated: Feb 1, 2026

Author Spotlight: Unveiling the Potential of TUBE Technique in Spinal Surgery
Published on: November 17, 2023
Implications of anesthetic approach, spinal versus general, for the treatment of spinal disc herniation
Nikhil Sharma1, Matthew Piazza1, Paul J Marcotte1,2
11Department of Neurosurgery, Hospital of the University of Pennsylvania, Philadelphia, Pennsylvania; and.

Abstract:
OBJECTIVEHealthcare costs continue to escalate. Approaches to care that have comparable outcomes and complications are increasingly assessed for quality improvement and, when possible, cost containment. Efforts to identify components of care to reduce length of stay (LOS) have been ongoing. Spinal anesthesia (SA), for select lumbar spine procedures, has garnered interest as an alternative to general anesthesia (GA) that might reduce cost and in-hospital LOS and accelerate recovery. While clinical outcomes with SA or GA have been studied extensively, few authors have looked at the cost-analysis in relation to clinical outcomes. The authors' objectives were to compare the clinical perioperative outcomes of patients who received SA and GA, as well as the direct costs associated with each modality of care, and to determine which, in a retrospective analysis, can serve as a dominant procedural approach.METHODSThe authors retrospectively analyzed a homogeneous surgical population of 550 patients who underwent hemilaminotomy for disc herniation and who received either SA (n = 91) or GA (n = 459). All clinical and billing data were obtained via each patient's chart and the hospital's billing database, respectively. Additionally, the authors prospectively assessed patient-reported outcome measures for a subgroup of consecutively treated patients (n = 75) and compared quality-adjusted life year (QALY) gains between the two cohorts. Furthermore, the authors performed a propensity score-matching analysis to compare the two cohorts (n = 180).RESULTSDirect hospital costs for patients receiving SA were 40% higher, in the hundreds of dollars, than for patients who received GA (p < 0.0001). Furthermore, there was a significant difference with regard to LOS (p < 0.0001), where patients receiving SA had a considerably longer hospital LOS (27.6% increase in hours). Patients undergoing SA had more comorbidities (p = 0.0053), specifically diabetes and hypertension. However, metrics of complications, including readmission (p = 0.3038) and emergency department (ED) visits at 30 days (p = 1.0), were no different. Furthermore, in a small pilot group, QALY gains were statistically no different (n = 75, p = 0.6708). Propensity score-matching analysis demonstrated similar results as the univariate analysis: there was no difference between the cohorts regarding 30-day readmission (p = 1.0000); ED within 30 days could not be analyzed as there were no patients in the SA group; and total direct costs and LOS were significantly different between the two cohorts (p < 0.0001 and p = 0.0126, respectively).CONCLUSIONSBoth SA and GA exhibit the qualities of a good anesthetic, and the utilization of these modalities for lumbar spine surgery is safe and effective. However, this work suggests that SA is associated with increased LOS and higher direct costs, although these differences may not be clinically or fiscally meaningful.
Related Concept Videos
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:26
Spinal Cord
 01:54
The Spinal Cord
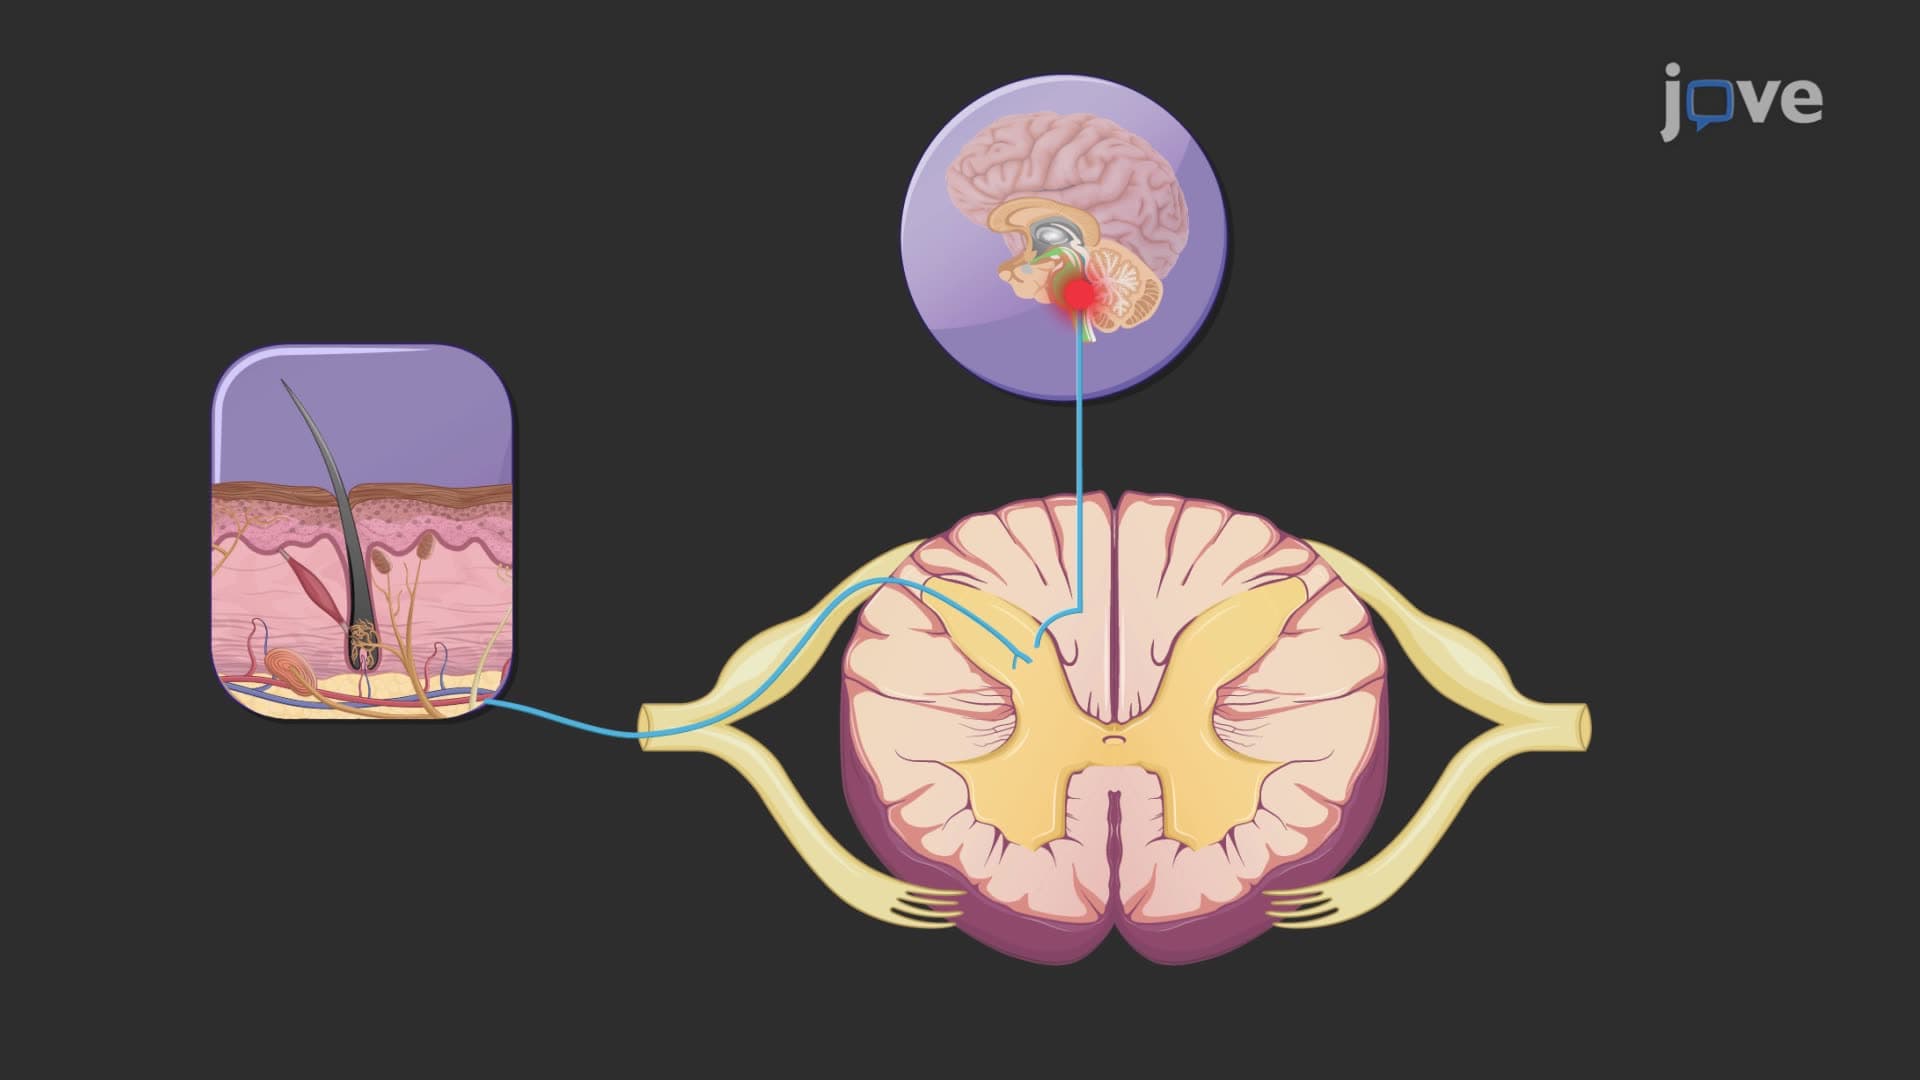 01:10
Spinal Cord: Information Processing
Sensory Information Processing
Sensory information processing begins at the sensory receptors located in the skin and other tissues, which detect somatic sensory stimuli such as touch, temperature, or pain. These receptors function as catalysts, initiating...
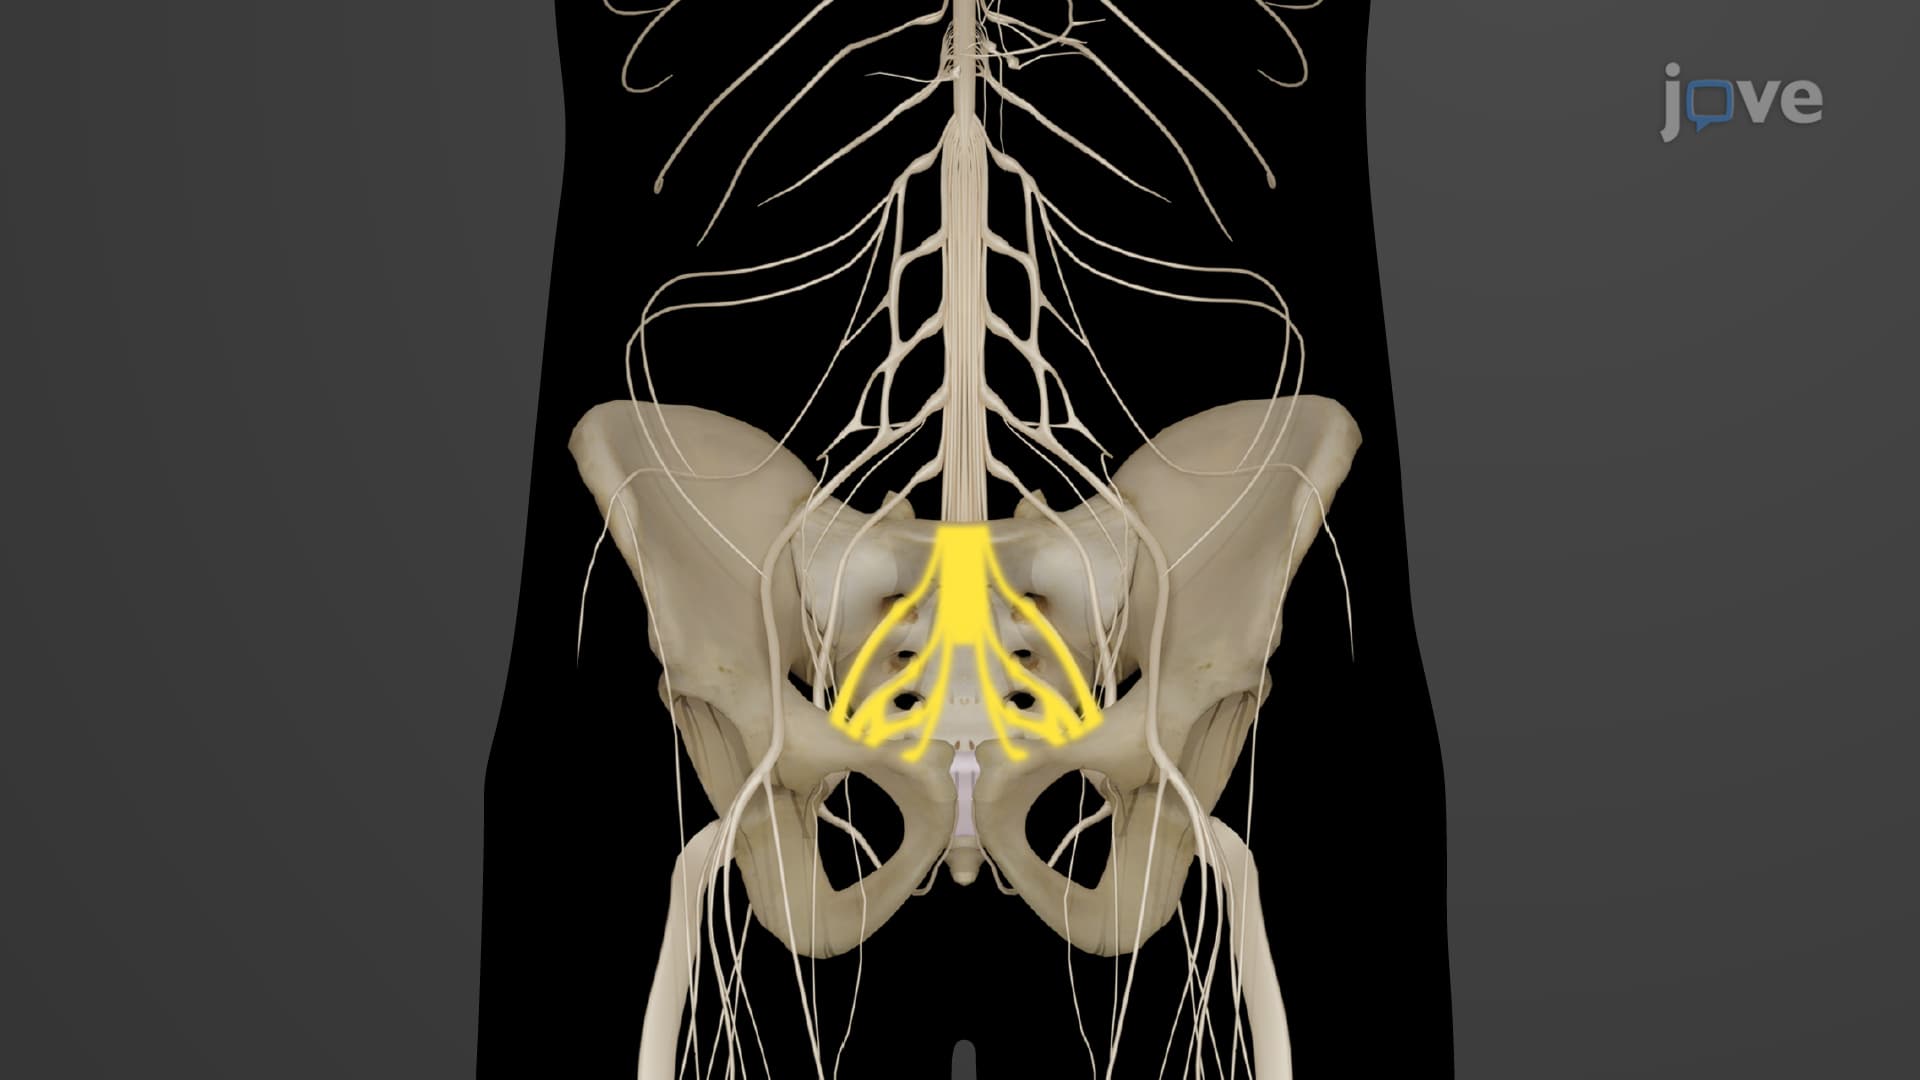 01:21
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
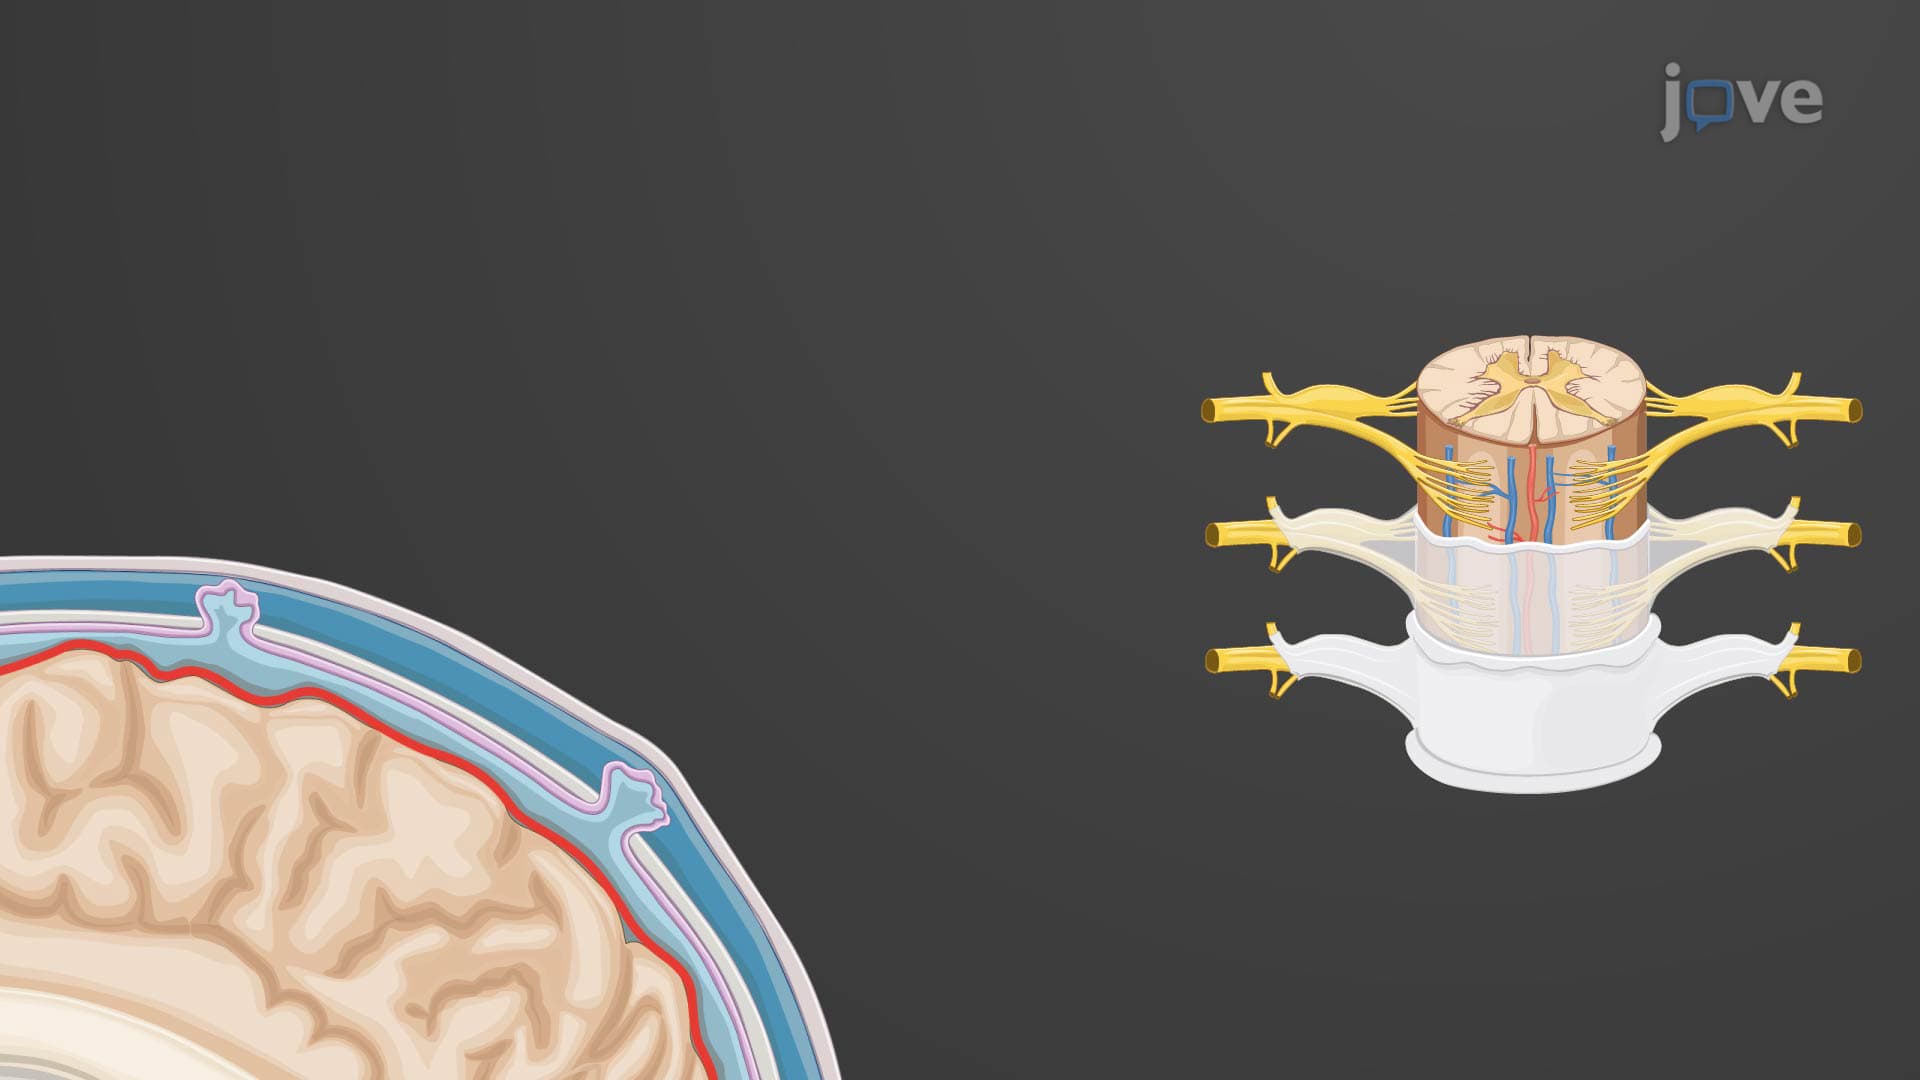 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...