Related Experiment Video
Updated: Feb 1, 2026


An Adoptive Transfer Model of Rheumatoid Arthritis in Mice
Published on: June 6, 2025
Cost-effective Tapering Algorithm in Patients with Rheumatoid Arthritis: Combination of Multibiomarker Disease
Melanie Hagen1,2, Matthias Englbrecht1,2, Judith Haschka1,2
1From the Friedrich-Alexander-University Erlangen-Nuremberg (FAU), Department of Internal Medicine 3 - Rheumatology and Immunology, Universitätsklinikum Erlangen, Erlangen, Germany; St. Vincent Hospital, Vinforce Study Group, Medical University of Vienna, Vienna, Austria; Institutio de Rheumatologia, São Paolo, Brazil; University of Würzburg, Internal Medicine 2, Würzburg; University Medical Center Freiburg, Rheumatology and Clinical Immunology, Freiburg; Rheumatology Clinical Practice Erlangen, Erlangen; Rheumatology Practice and Department of Internal Medicine 2, Clinic Burghausen, Burghausen; Asklepios Medical Center, Department of Rheumatology and clinical Immunology, Bad Abbach; Rheumatology Practice Bamberg, Bamberg; Rheumatology Practice Bayreuth, Bayreuth; University of Heidelberg, Medicine 5, Heidelberg; Rheumatology Practice Nuremberg, Nuremberg; Schlosspark Klinik, Internal Medicine/Rheumatology, Berlin; University of Tübingen, Centre for Interdisciplinary Clinical Immunology, Tübingen; Praxiszentrum St. Bonifatius, Munich, Germany.

Objective:
To analyze the effect of a risk-stratified disease-modifying antirheumatic drug (DMARD)-tapering algorithm based on multibiomarker disease activity (MBDA) score and anticitrullinated protein antibodies (ACPA) on direct treatment costs for patients with rheumatoid arthritis (RA) in sustained remission.
Methods:
The study was a posthoc retrospective analysis of direct treatment costs for 146 patients with RA in sustained remission tapering and stopping DMARD treatment, in the prospective randomized RETRO study. MBDA scores and ACPA status were determined in baseline samples of patients continuing DMARD (arm 1), tapering their dose by 50% (arm 2), or stopping after tapering (arm 3). Patients were followed over 1 year, and direct treatment costs were evaluated every 3 months. MBDA and ACPA status were used as predictors creating a risk-stratified tapering algorithm based on relapse rates.
Results:
RA patients with a low MBDA score (< 30 units) and negative ACPA showed the lowest relapse risk (19%), while double-positive patients showed high relapse risk (61%). In ACPA-negative and MBDA-negative (< 30 units), and ACPA or MBDA single-positive (> 30 units) groups, DMARD tapering appears feasible. Considering only patients without flare, direct costs for synthetic and biologic DMARD in the ACPA/MBDA-negative and single positive groups (n = 41) would have been €372,245.16 for full-dose treatment over 1 year. Tapering and stopping DMARD in this low-risk relapse group allowed a reduction of €219,712.03 of DMARD costs. Average reduction of DMARD costs per patient was €5358.83.
Conclusion:
Combining MBDA score and ACPA status at baseline may allow risk stratification for successful DMARD tapering and cost-effective use of biologic DMARD in patients in deep remission as defined by the 28-joint count Disease Activity Score using erythrocyte sedimentation rate.
More Related Videos
 07:44
Author Spotlight: Implementation of BIVA for Analyzing Disease Risk Factors in Patients with Low Body Cell Mass
Published on: July 14, 2023
 09:31
Generation of Induced-pluripotent Stem Cells Using Fibroblast-like Synoviocytes Isolated from Joints of Rheumatoid Arthritis Patients
Published on: October 16, 2016
Related Concept Videos
 01:27
Combined Effects of Drugs: Synergism
Such synergistic combinations...
 01:30
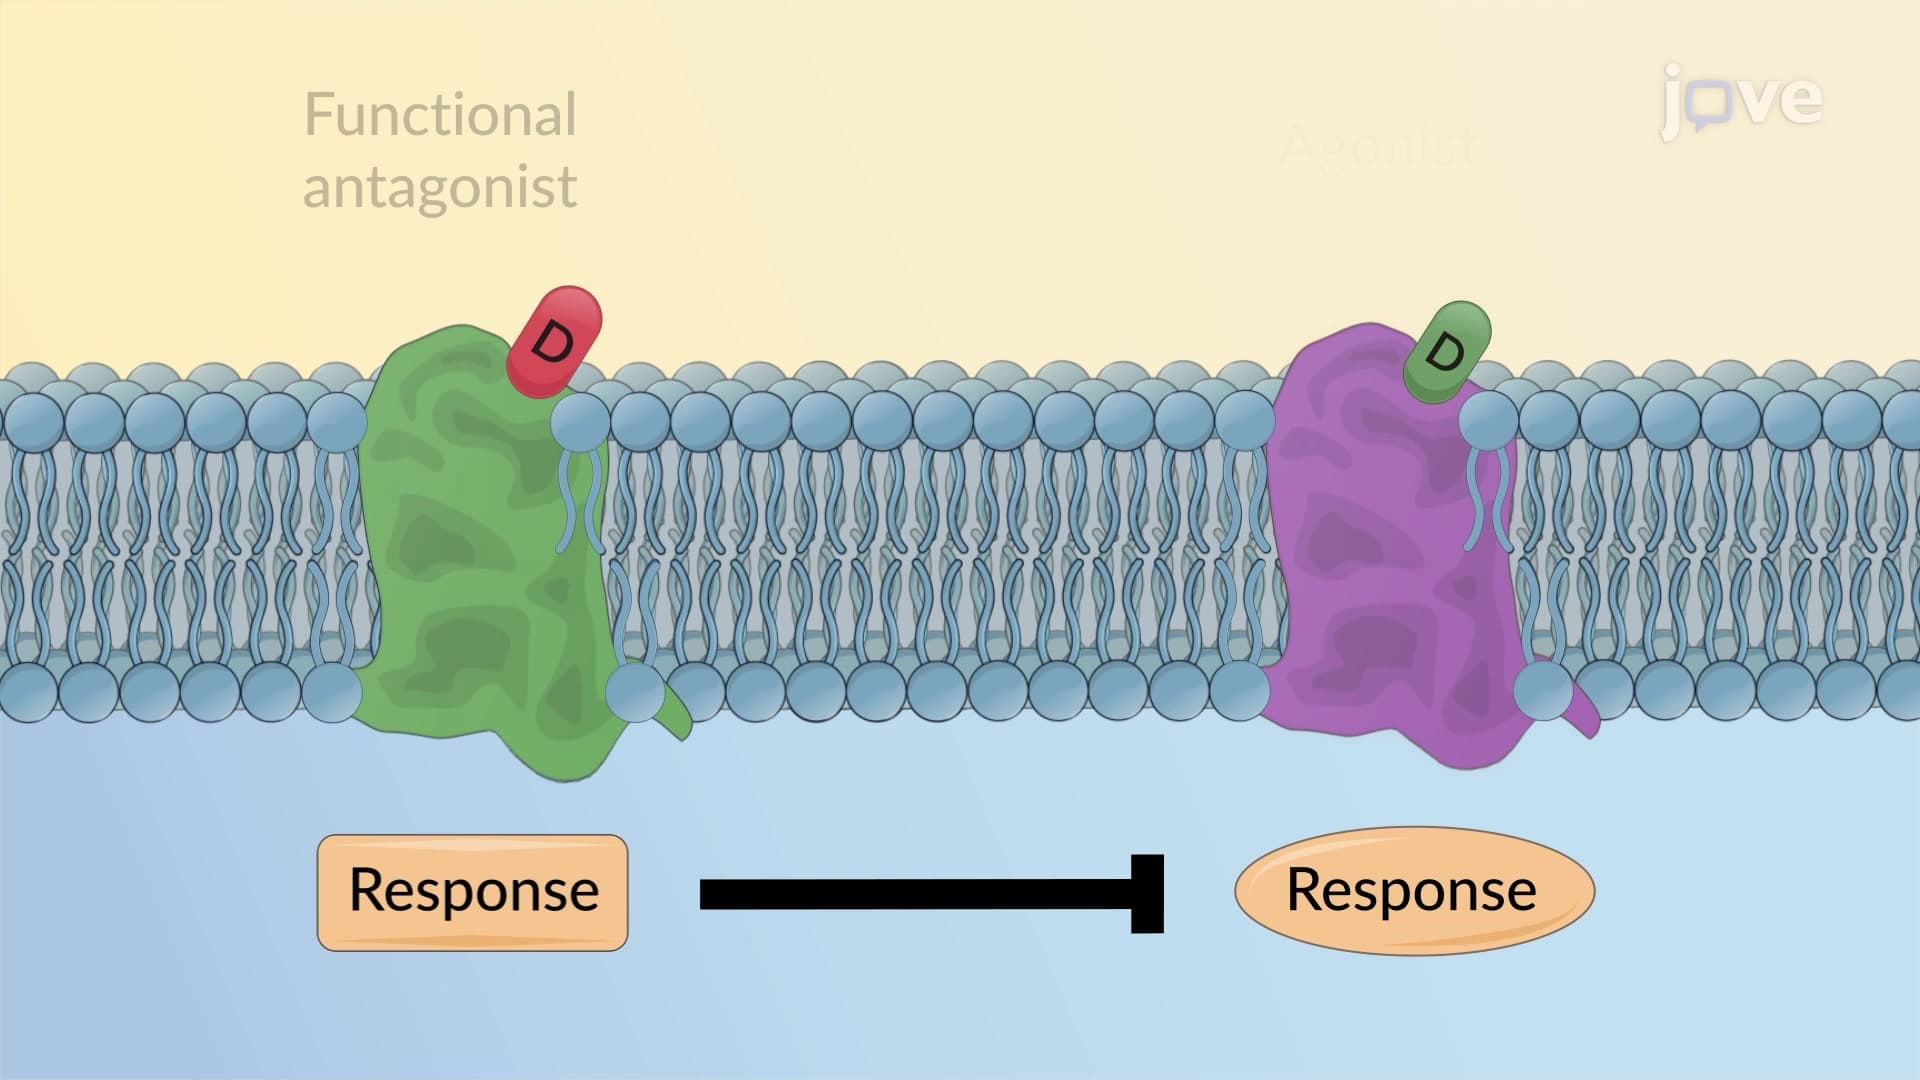
Combined Effects of Drugs: Antagonism
The most common type is receptor antagonism, where one drug acts as an antagonist to block the effects of another drug by...
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age
 01:06
Introduction to z Scores
z scores...
 01:05
Introduction to z Scores
z scores...
 01:17
z Scores and Area Under the Curve