Related Experiment Video
Updated: Aug 16, 2026

Nerve Excitability Assessment in Chemotherapy-induced Neurotoxicity
Published on: April 26, 2012
Vancomycin ototoxicity and nephrotoxicity. A review
1University of Manchester, Department of Pharmacy, Hope Hospital, Salford, England.

Abstract:
Vancomycin has been in clinical use as a potent antistaphylococcal antibiotic for over 30 years. Most reports of ototoxicity and nephrotoxicity have been associated with early, relatively impure, formulations of vancomycin. This paper reviews the literature concerning vancomycin ototoxocity and nephrotoxicity and the evidence for their correlation with the therapeutic serum concentration range. There have been 28 reports of vancomycin-associated ototoxicity published in the medical literature since 1958. It remains unclear whether any diminution in hearing is permanent or reversible. Few patients in the literature had follow-up audiometry and the hearing impairment tends to be at higher frequencies. Several authors reported peak serum vancomycin concentrations, but the exact time these were drawn with respect to the last dose is mostly unclear. In other reports, the 'peak' concentrations noted 3 to 6 hours after the last dose are probably indicative of much higher concentrations because of vancomycin's rapid phase of distribution. More than half the 57 cases of reported nephrotoxicity due to vancomycin occurred within the first 6 years of the drug's use. Many of these patients also had pre-existing renal dysfunction or were concomitantly receiving other nephrotoxic agents. It is unclear whether the coadministration of aminoglycosides produces a synergistic toxicity. The exact incidence of nephrotoxicity is uncertain, but is probably less with the current, relatively pure, product. The correlation of nephrotoxicity with certain serum vancomycin concentrations remains to be clarified. Other aspects also require clarification, such as when to draw samples to determine peak serum concentrations and whether or not routine measurements are necessary at all. In the absence of better guidelines, efforts should be made to tailor individual patient's regimens to produce peak and trough serum vancomycin concentrations to within the widely accepted ranges of 30 to 40 and 5 to 10 mg/L, respectively. In addition, the concomitant use of other potentially nephrotoxic and ototoxic agents should be avoided.
Insights
Vancomycin ototoxicity and nephrotoxicity are linked to early formulations. Current research reviews literature, suggesting careful monitoring of vancomycin serum concentrations to minimize risks.
Area of Science:
- Pharmacology
- Nephrology
- Ototoxicology
Background:
- Vancomycin, an antistaphylococcal antibiotic, has been used clinically for over 30 years.
- Early, less pure vancomycin formulations were associated with ototoxicity and nephrotoxicity.
- The correlation between therapeutic serum concentrations and these toxicities requires further clarification.
Purpose of the Study:
- To review the medical literature on vancomycin-associated ototoxicity and nephrotoxicity.
- To examine the evidence linking these toxicities to therapeutic serum vancomycin concentrations.
- To identify areas requiring further clarification regarding vancomycin toxicity monitoring.
Main Methods:
- Literature review of published reports on vancomycin ototoxicity and nephrotoxicity.
- Analysis of case studies detailing patient outcomes and serum vancomycin concentrations.
- Evaluation of factors contributing to vancomycin-induced toxicities, including co-administration of other agents.
Main Results:
- 28 reports of vancomycin-associated ototoxicity since 1958; hearing impairment often affects higher frequencies and may be reversible.
- Over half of 57 reported nephrotoxicity cases occurred early in vancomycin's use, often with pre-existing renal dysfunction or concurrent nephrotoxic agents.
- The precise incidence and correlation of nephrotoxicity with serum concentrations remain uncertain, especially with current purer formulations.
Conclusions:
- While early vancomycin formulations posed risks, current products are likely safer.
- Optimal timing for serum concentration sampling and necessity of routine monitoring require further investigation.
- Tailoring vancomycin regimens to achieve target peak (30-40 mg/L) and trough (5-10 mg/L) concentrations and avoiding co-administration of other nephrotoxic/ototoxic agents are recommended.

Related Concept Videos
 01:15
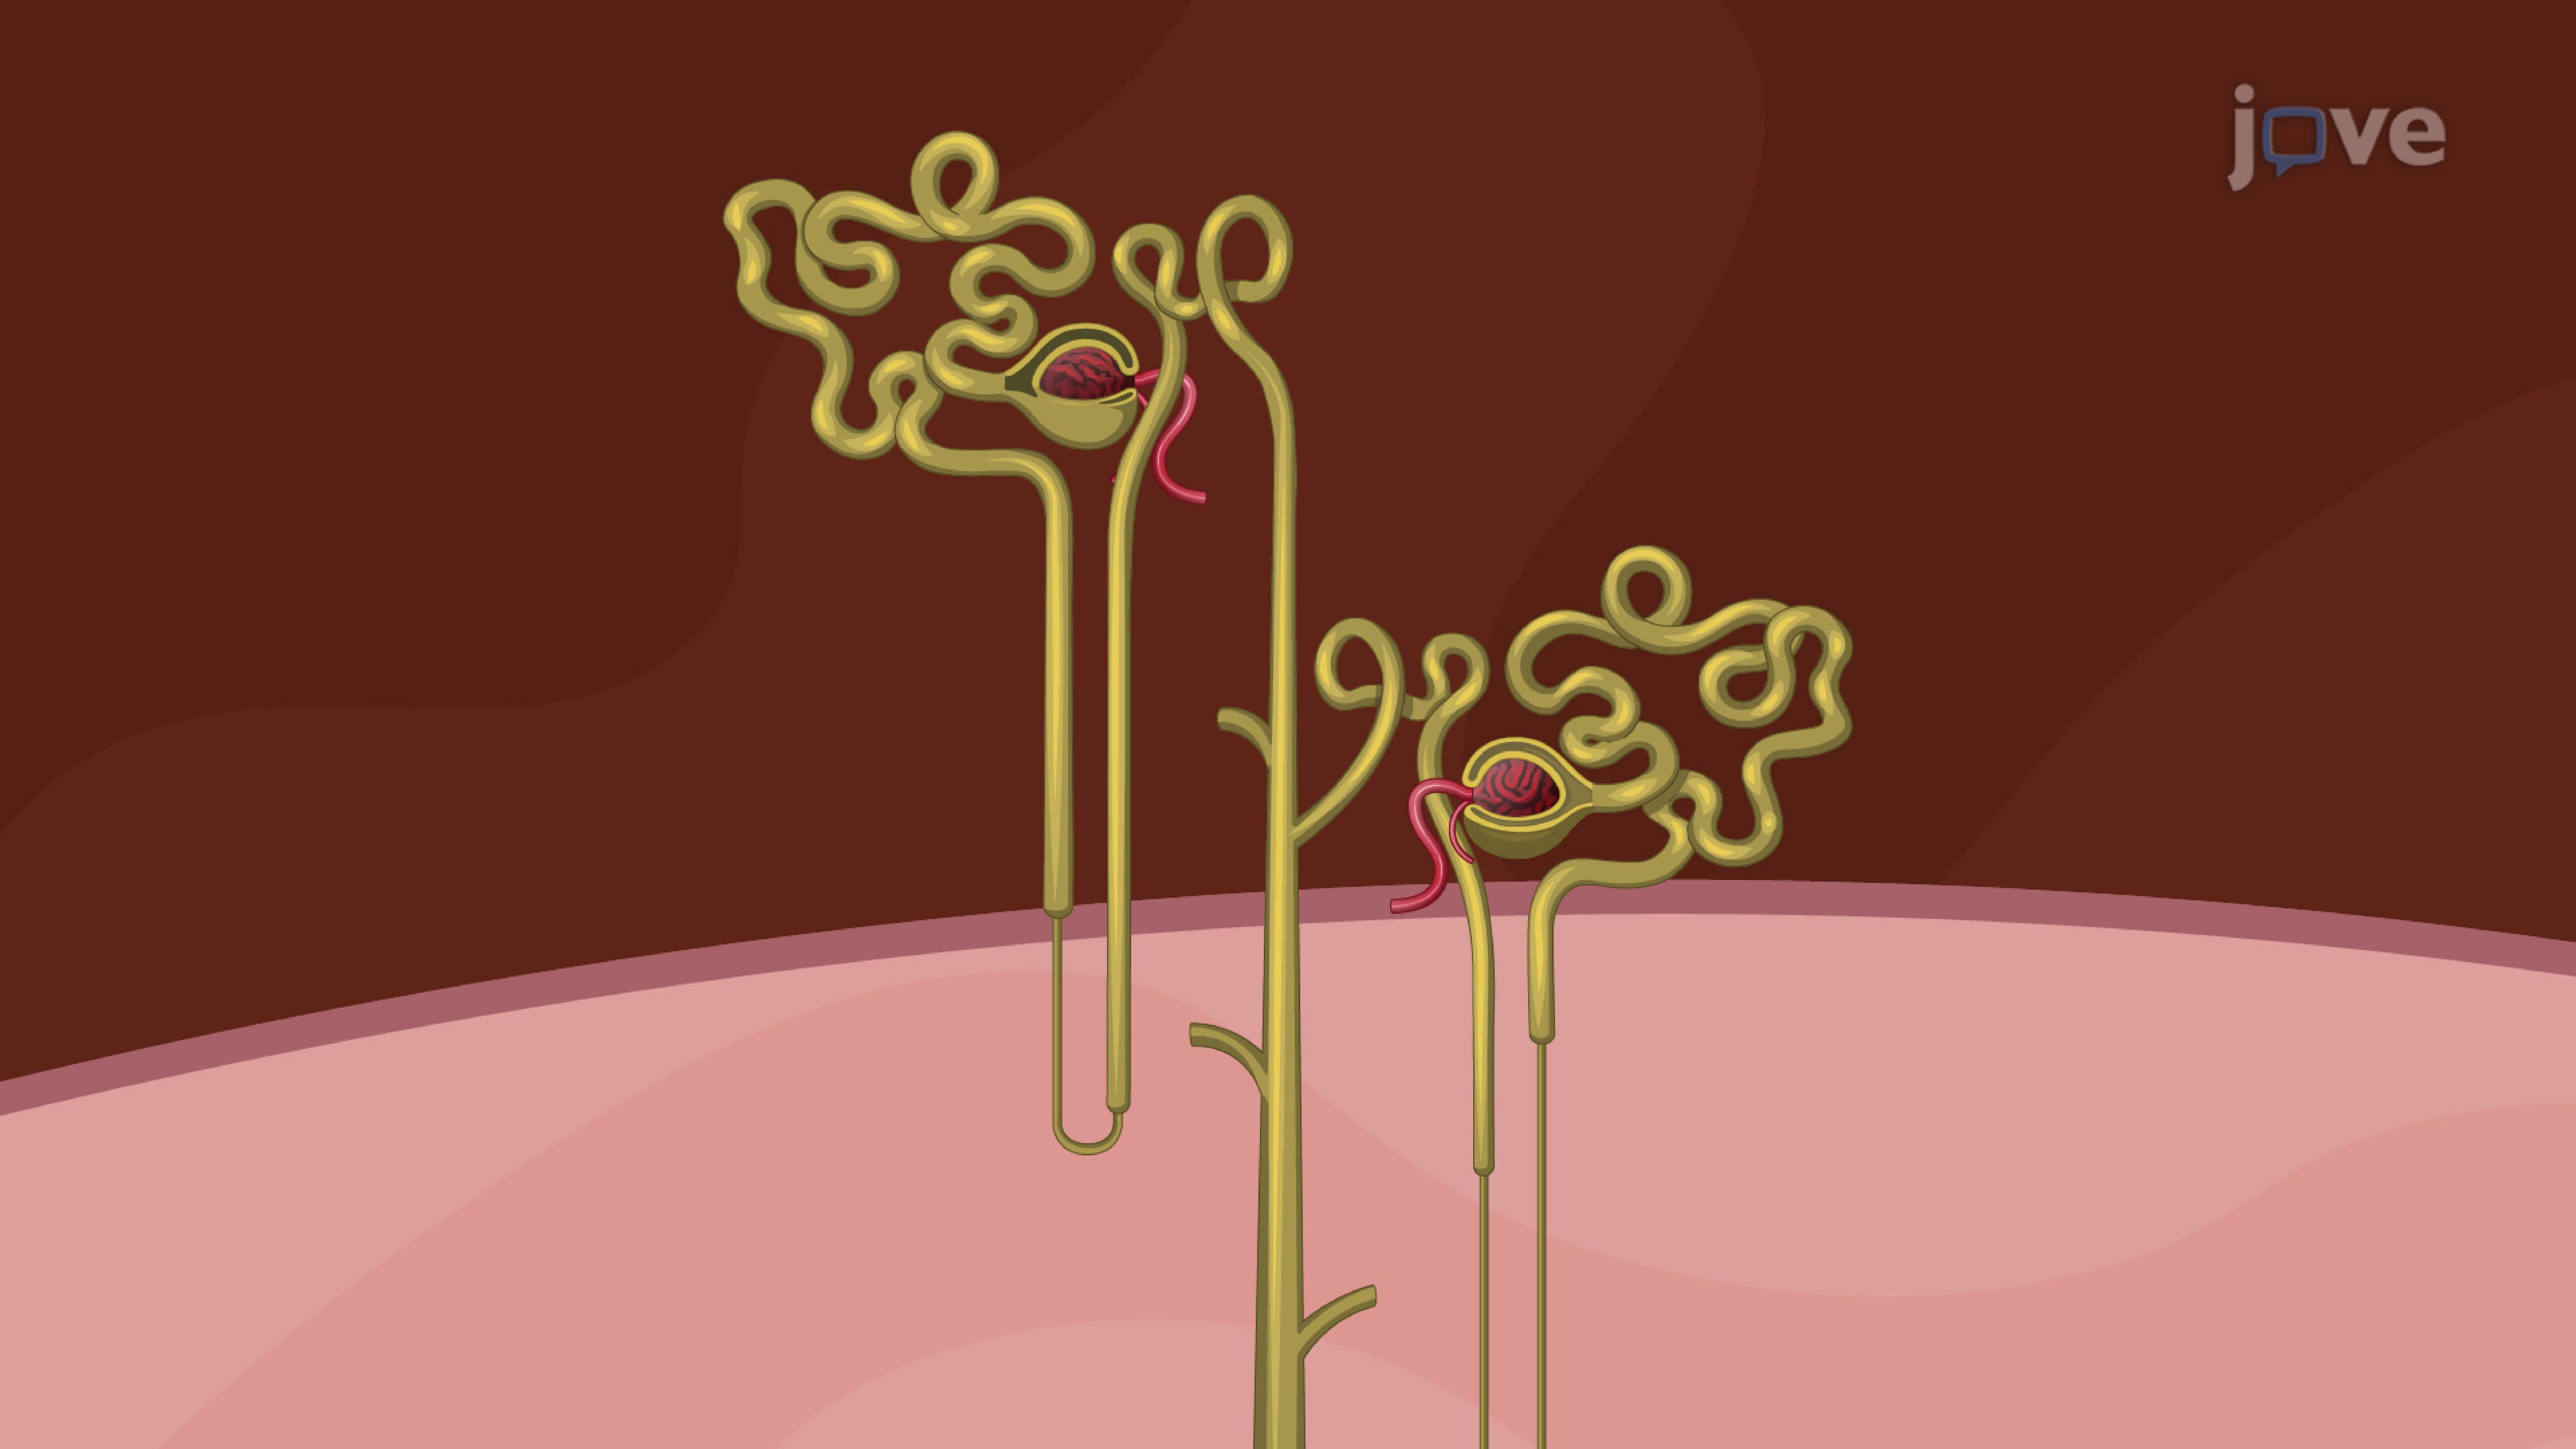
Renal Drug Excretion: Overview
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules out...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:00
Drug Toxicity: Overview
 01:24
Drug Toxicity: Risk factors
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention