Related Experiment Video
Updated: Jan 31, 2026

Direct Pressure Monitoring Accurately Predicts Pulmonary Vein Occlusion During Cryoballoon Ablation
Published on: February 26, 2013
Pulmonary vein isolation in patients with a left common pulmonary vein: Comparison between second-generation
Masao Yamaguchi1, Shinsuke Miyazaki2, Takatsugu Kajiyama1
1Cardiovascular Center, Tsuchiura Kyodo Hospital, Tsuchiura, Ibaraki, Japan.

Background:
Adaptability of cryoballoons to anatomic pulmonary vein (PV) variations is limited due to the fixed geometrical shape, and use for left common PVs (LCPVs) is controversial. We compared the procedural and clinical outcomes in patients with LCPVs after cryoballoon and radiofrequency ablation, and explored the morphological parameters associated with procedural difficulty in LCPV isolations using cryoballoons.
Methods And Results:
Eighty-nine consecutive atrial fibrillation patients with LCPVs undergoing PV isolation using either 28-mm second-generation cryoballoons (n=30) or irrigated-tip catheters (n=59) were included. The patient characteristics except for the left atrial diameter (p=0.05) or morphological parameters obtained from cardiac computed tomography were similar between the two groups. The number needed to disconnect the LCPVs (NND) in the cryoballoon-group was ≦3 applications in 22 patients, but ≧4 in the remaining 8, including 1 requiring touch-up ablation. The PV isolation procedure time was significantly shorter in the cryoballoon-group than radiofrequency-group (43.0±19.5min vs. 68.2±31.4min, p<0.001), whereas the single procedure 1-year atrial fibrillation freedom was similar between the groups (74% vs. 67%, p=0.73). A multivariate logistic regression analysis revealed that the ovality index in the cryoballoon-group (odds ratio=1.474; 95%confidence interval=1.020-2.128; p=0.039) and orientation difference between the LCPV and lower branch in the frontal plane (odds ratio=1.071; 95%confidence interval=1.008-1.137; p=0.026) were independent predictors of an NND≧4. The incidence of LCPV reconnections was similar between the cryoballoon- and radiofrequency-groups during the second procedure (50.0% vs. 58.3%, p=0.73).
Conclusions:
Cryoballoon ablation was similarly as effective as radiofrequency ablation in patients with LCPVs, and morphological evaluations aided in predicting procedural difficulty in LCPV isolations.

Related Concept Videos
 01:17
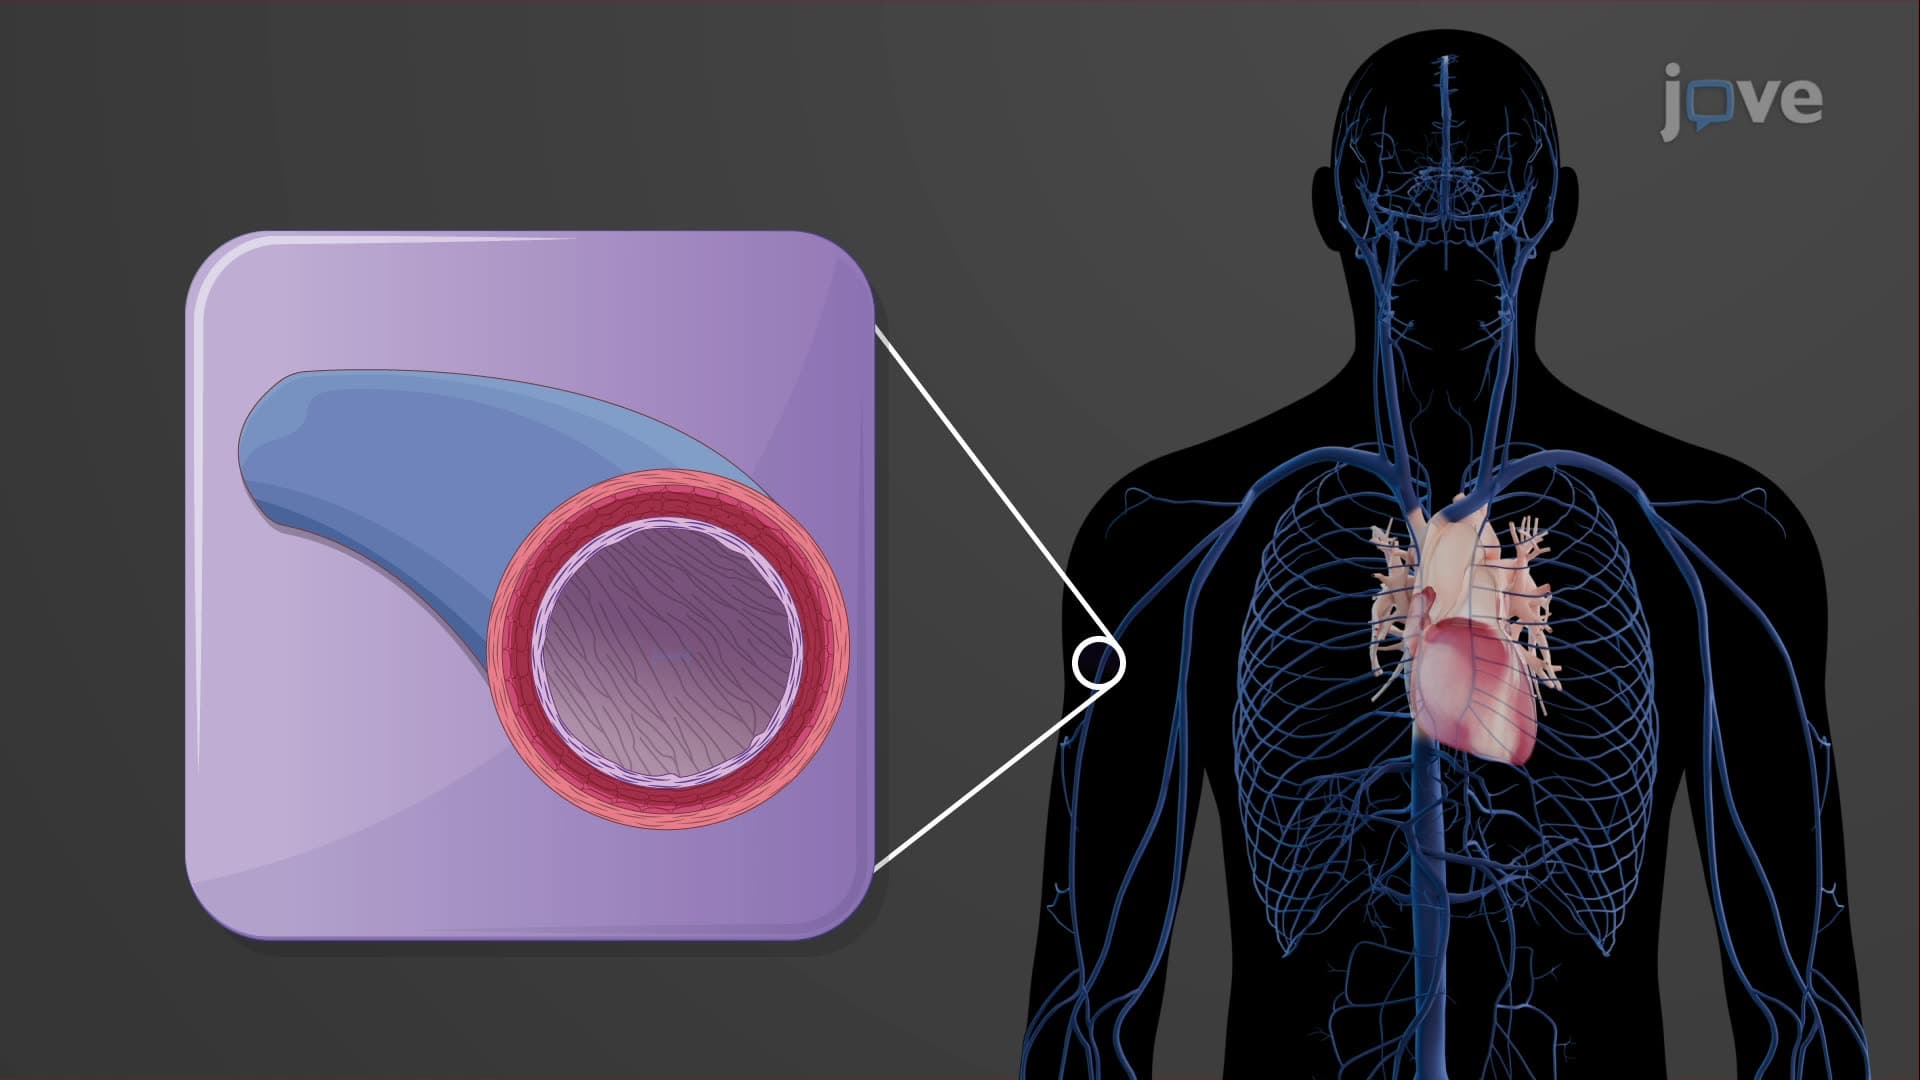
Veins
Structure of Veins:
The structure of veins is specifically designed to assist in the low-pressure transportation of...
 01:19
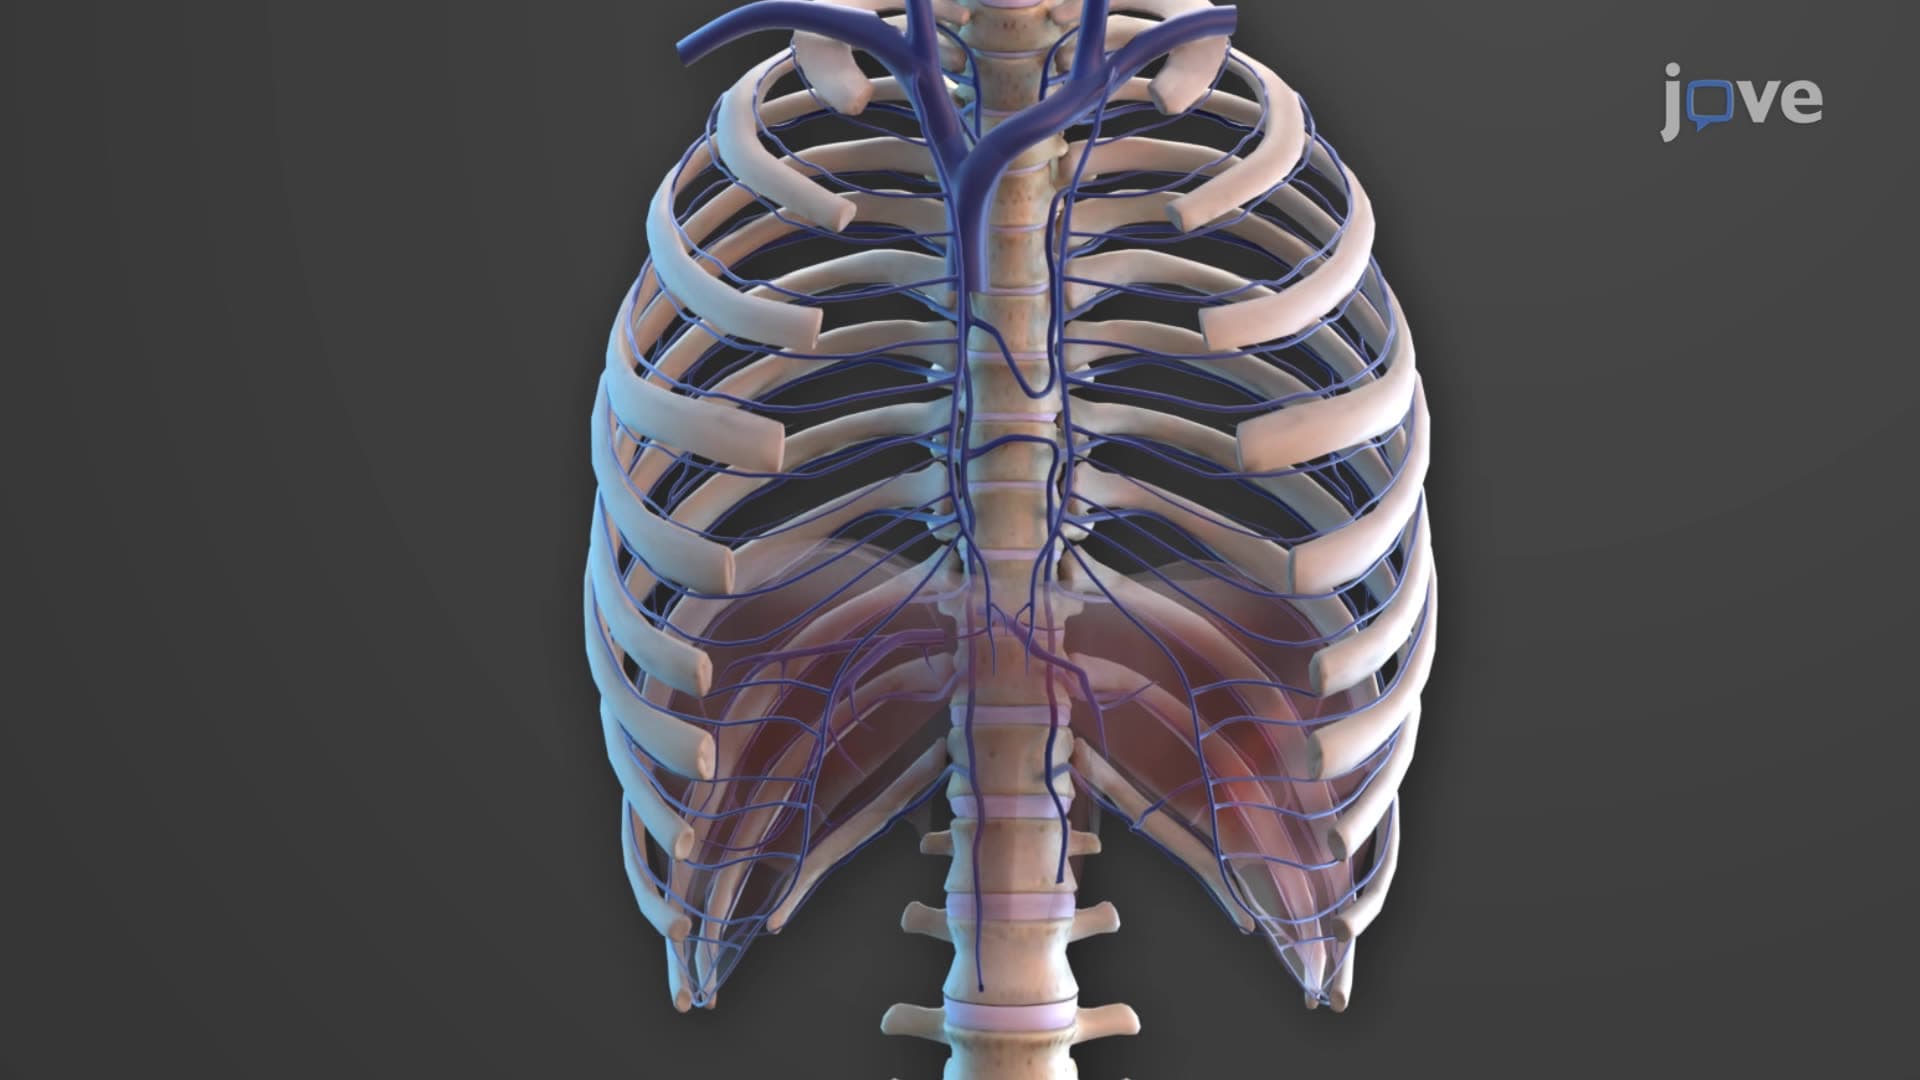
Veins of Thorax
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...
 01:15
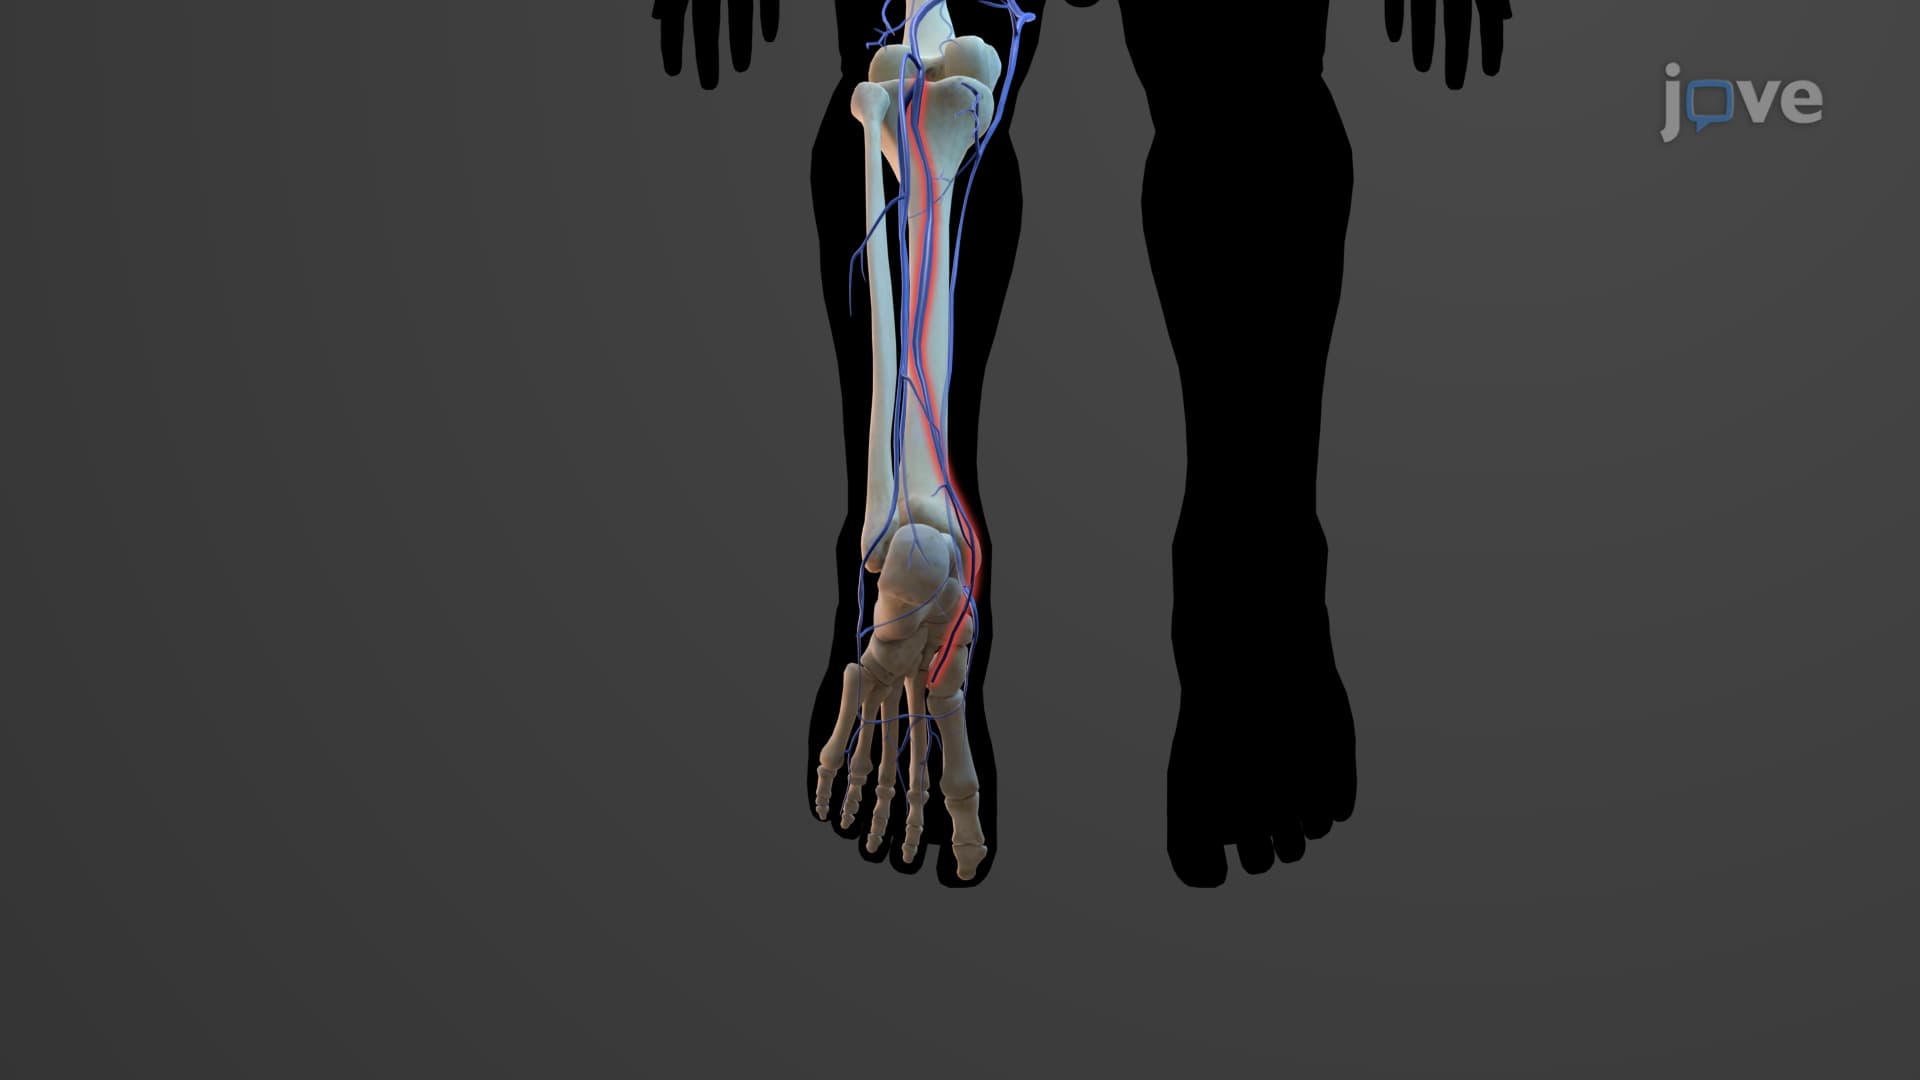
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...