Related Experiment Video
Updated: Aug 12, 2026
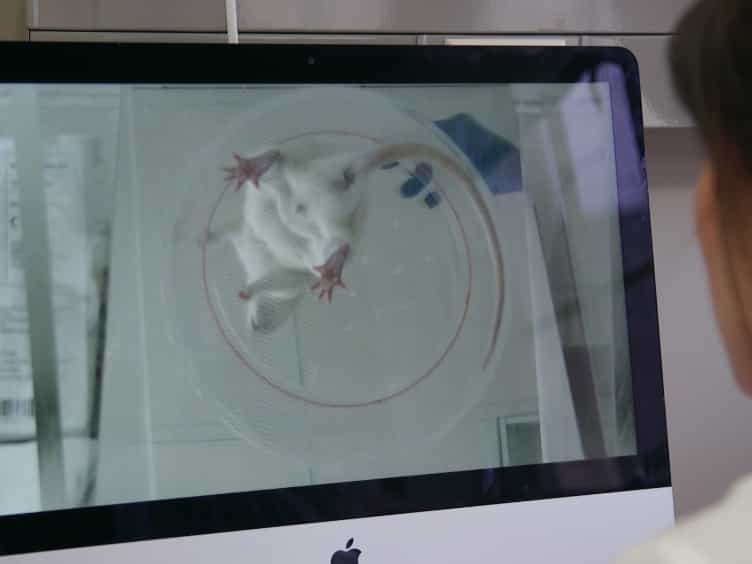

Motor and Hippocampal Dependent Spatial Learning and Reference Memory Assessment in a Transgenic Rat Model of Alzheimer's Disease with Stroke
Published on: March 22, 2016
Dementia following stroke
1University of Minnesota, Minneapolis.

Strokes can be due to ischemic or hemorrhagic vascular disorders. Ischemic strokes outnumber hemorrhagic strokes approximately 4:1. Although the mode of presentation and pathophysiology are different in the two conditions, the outcome is really dependent on the extent and location of brain injury. A CT scan helps in this regard and reveals surgically correctable lesions such as a subdural hematoma or normal pressure hydrocephalus. Effective rehabilitation of the stroke patient is dependent on motivation and cognitive ability even more than on remaining motor or sensory function. A team approach to assessment provides the opportunity to make an accurate appraisal of a patient's current level of functioning and an estimate of premorbid capabilities. A thorough review of the history, complete neurologic examination, mental status testing, and laboratory and radiographic data should be obtained by the treating physician. Neuropsychologic testing, speech and language evaluation, ADL assessment, nursing observations, and psychiatric consultation round off the attempts to fully learn the limitations and strengths that characterize the patient. The value in assessing cognitive abilities after a stroke should be obvious. Not only is motivation necessary, but the patient must comprehend the purpose of the rehabilitation process. Goal-setting is a combined effort of the patient and the rehabilitation team. If a patient has limited understanding and faulty memory, the efforts may be wasted. The presence of acute confusion or delirium may delay rehabilitation efforts, but the etiology may be readily treatable. When there is strong suspicion of a degenerative dementia such as Alzheimer's disease, the expectations are lowered. Occasionally, the problem is a mixed dementia in which instance the prognosis is poor. When there is evidence for multi-infarct dementia, there is a possibility for cognitive improvement when medical problems such as hypertension and embolization are treated. Much can be done for one who has limited and focal cerebral damage provided there is adequate comprehension and ability to compensate for disability.
Strokes can be due to ischemic or hemorrhagic vascular disorders. Ischemic strokes outnumber hemorrhagic strokes approximately 4:1. Although the mode of presentation and pathophysiology are different in the two conditions, the outcome is really dependent on the extent and location of brain injury. A CT scan helps in this regard and reveals surgically correctable lesions such as a subdural hematoma or normal pressure hydrocephalus. Effective rehabilitation of the stroke patient is dependent on motivation and cognitive ability even more than on remaining motor or sensory function. A team approach to assessment provides the opportunity to make an accurate appraisal of a patient's current level of functioning and an estimate of premorbid capabilities. A thorough review of the history, complete neurologic examination, mental status testing, and laboratory and radiographic data should be obtained by the treating physician. Neuropsychologic testing, speech and language evaluation, ADL assessment, nursing observations, and psychiatric consultation round off the attempts to fully learn the limitations and strengths that characterize the patient. The value in assessing cognitive abilities after a stroke should be obvious. Not only is motivation necessary, but the patient must comprehend the purpose of the rehabilitation process. Goal-setting is a combined effort of the patient and the rehabilitation team. If a patient has limited understanding and faulty memory, the efforts may be wasted. The presence of acute confusion or delirium may delay rehabilitation efforts, but the etiology may be readily treatable. When there is strong suspicion of a degenerative dementia such as Alzheimer's disease, the expectations are lowered. Occasionally, the problem is a mixed dementia in which instance the prognosis is poor. When there is evidence for multi-infarct dementia, there is a possibility for cognitive improvement when medical problems such as hypertension and embolization are treated. Much can be done for one who has limited and focal cerebral damage provided there is adequate comprehension and ability to compensate for disability.


Related Concept Videos
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
 01:30
Dementia
The progression of dementia is generally gradual.
 01:29
Stroke: Introduction and Types
 01:15
Ischemic Stroke ll: Pathophysiology
 01:29
Alzheimer Disease l: Introduction
 01:22
Dementia l: Introduction