Related Experiment Video
Updated: Jan 29, 2026
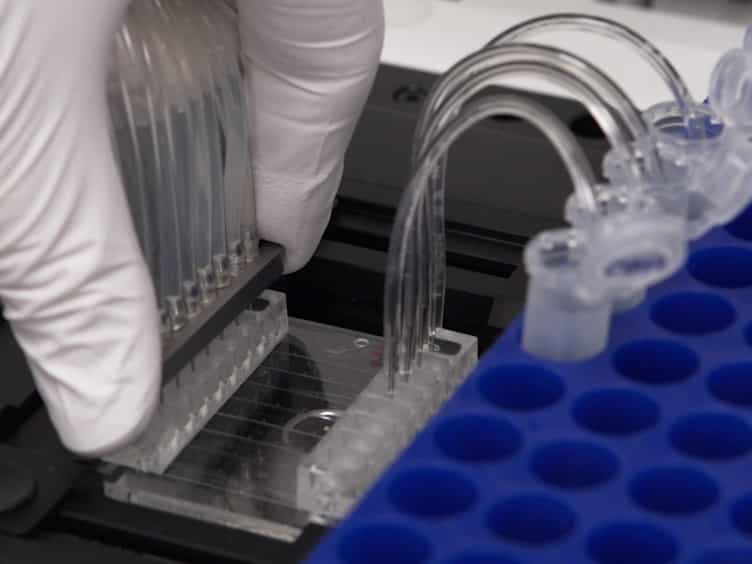

Microfluidic Flow Chambers Using Reconstituted Blood to Model Hemostasis and Platelet Transfusion In Vitro
Published on: March 19, 2016
Why does a point of care guided transfusion algorithm not improve blood loss and transfusion practice in patients
F Lehmann1, J Rau2, B Malcolm3
1Department of Anaesthesiology and Intensive Care Medicine, Charité - Universitätsmedizin Berlin, Campus Virchow-Klinikum and Campus Charité Mitte, Berlin, Germany. ferdinand.lehmann@charite.de.

Background:
Adult cardiac surgery is often complicated by elevated blood losses that account for elevated transfusion requirements. Perioperative bleeding and transfusion of blood products are major risk factors for morbidity and mortality. Timely diagnostic and goal-directed therapies aim at the reduction of bleeding and need for allogeneic transfusions.
Methods:
Single-centre, prospective, randomized trial assessing blood loss and transfusion requirements of 26 adult patients undergoing elective cardiac surgery at high risk for perioperative bleeding. Primary endpoint was blood loss at 24 h postoperatively. Random assignment to intra- and postoperative haemostatic management following either an algorithm based on conventional coagulation assays (conventional group: platelet count, aPTT, PT, fibrinogen) or based on point-of-care (PoC-group) monitoring, i.e. activated rotational thromboelastometry (ROTEM®) combined with multiple aggregometry (Multiplate®). Differences between groups were analysed using nonparametric tests for independent samples.
Results:
The study was terminated after interim analysis (n = 26). Chest tube drainage volume was 360 ml (IQR 229-599 ml) in the conventional group, and 380 ml (IQR 310-590 ml) in the PoC-group (p = 0.767) after 24 h. Basic patient characteristics, results of PoC coagulation assays, and transfusion requirements of red blood cells and fresh frozen plasma did not differ between groups. Coagulation results were comparable. Platelets were transfused in the PoC group only.
Conclusion:
Blood loss via chest tube drainage and transfusion amounts were not different comparing PoC- and central lab-driven transfusion algorithms in subjects that underwent high-risk cardiac surgery. Routine PoC coagulation diagnostics do not seem to be beneficial when actual blood loss is low. High risk procedures might not suffice as a sole risk factor for increased blood loss.
Trial Registration:
NCT01402739 , Date of registration July 26, 2011.


Related Concept Videos
 01:15
Blood Transfusion
Blood Transfusion Overview
A blood transfusion is a medical procedure used to replace blood lost due to injury, surgery, or to treat conditions such as anemia or cancer. During a transfusion, donor blood is...
 02:45
Blood Transfusion and Agglutination
History
The history of blood transfusion dates back to the 17th century, when early attempts were made in animals. In 1818 James Blundell, a British doctor, performed the first successful human blood transfusion. Later in 1900, Karl...
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:13
Patient-centered Care
 01:20
Bioequivalence Experimental Study Designs: Completely Randomized and Randomized Block Designs
 01:19
Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers
These markers indicate stress or strain on the heart muscle:
Natriuretic Peptides (BNP)
Cardiac myocytes produce these hormones in response to ventricular stretching...