Related Experiment Video
Updated: Jan 28, 2026
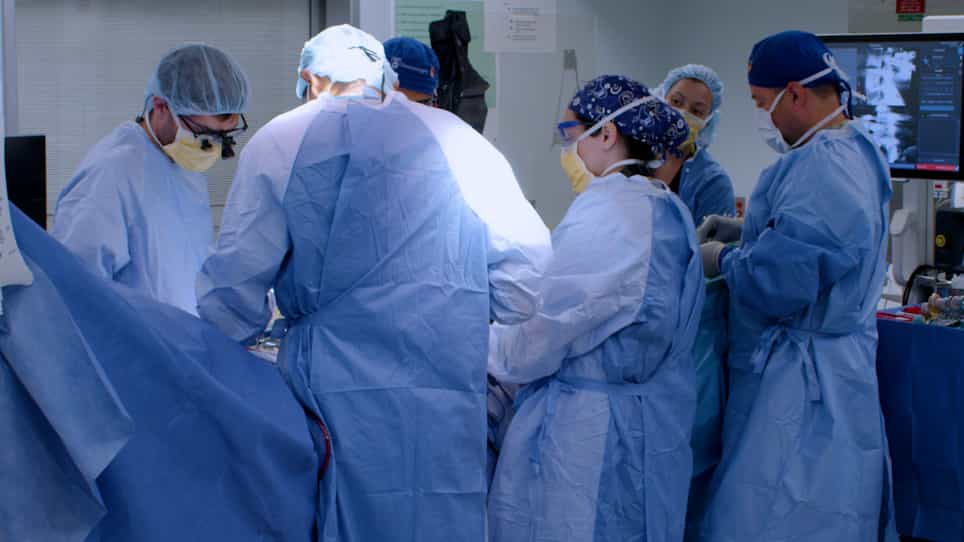

Three-dimensional Navigation-guided, Prone, Single-position, Lateral Lumbar Interbody Fusion Technique
Published on: July 15, 2021
Acute rib fracture caused by preoperative positioning for direct lateral interbody fusion: A case report
Chang Hwa Hong1, Ki Jin Jung1, Jae Wan Soh1
1Department of Orthopaedic Surgery, Soonchunhyang University Hospital Cheonan, Dongam-gu, Cheonan.

Rationale:
Degenerative spondylolisthesis is defined as forward slippage of a vertebra with respect to the underlying vertebra and is associated with the induction of lumbar canal stenosis. The use of anterior column support for degenerative lumbar conditions has been well documented. Direct lateral interbody fusion (DLIF) gains access via a lateral approach through the retroperitoneal fat and psoas muscle. It avoids many of the access-related complications yet comes with its own risks and limitations. The location of the iliac wing precludes exposure of the L5-S1 disc space and may make L4-5 surgery difficult. Therefore, accurate preoperative patient positioning is essential.
Patient Concerns:
A 71-year-old female with a body mass index (BMI) of 39.2 kg/m (height 155.9 cm, weight 79.5 kg) presented with lumbar pain radiating to the left lower limb. She complained of neurologic claudication with more than 100 m ambulation.
Diagnosis:
Plain standing view on spine radiography revealed L4-5 spondylolisthesis and disc-space narrowing. Magnetic resonance imaging (MRI) revealed severe L4-5 bilateral foraminal stenosis. After the first surgery, simple rib cage radiography was performed to examine the source of her right-sided flank pain and it revealed acute fracture of the right ninth and tenth ribs.
Interventions:
The patient was laterally positioned on the table in an extreme bending position. The intervertebral cage was inserted in the L4-5 disc space and disc height was restored. With respect to the rib fracture, treatment was conservative.
Outcomes:
The patient's radiating pain was immediately relieved and her lower back pain disappeared at 3 months after surgery. The patient reported right-sided flank pain after the first surgery. Simple rib cage radiography was performed and revealed fracture of the right ninth and tenth ribs. Follow-up assessments conducted 2 months later revealed complete bony union.
Lessons:
DLIF avoids many access-related complications. However, it is associated with other intraoperative complications, including injury to the lumbar nerve root and plexus. In addition, there are preoperative complications associated with improper patient placement on the table. In this case, the patient's obesity and strict positional requirements resulted in rib fracture. We suggest that surgeons consider this complication and exercise care in preoperative positioning.

Related Concept Videos
 02:45
Nuclear Fusion
A helium nucleus has a mass that is 0.7% less than that of four hydrogen nuclei; this lost mass is converted into energy during the fusion. This reaction produces about...
 01:20
The Thoracic Cage: Ribs
Parts of a Typical Rib
A typical rib has a head, neck, and body. The posterior end of the rib is called the head, followed by a narrow neck. The head articulates primarily with the costal...
 02:32
Position-effect Variegation
 01:28
Lateralization
 01:24
Data Reporting and Recording
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...