Related Experiment Video
Updated: Jan 28, 2026
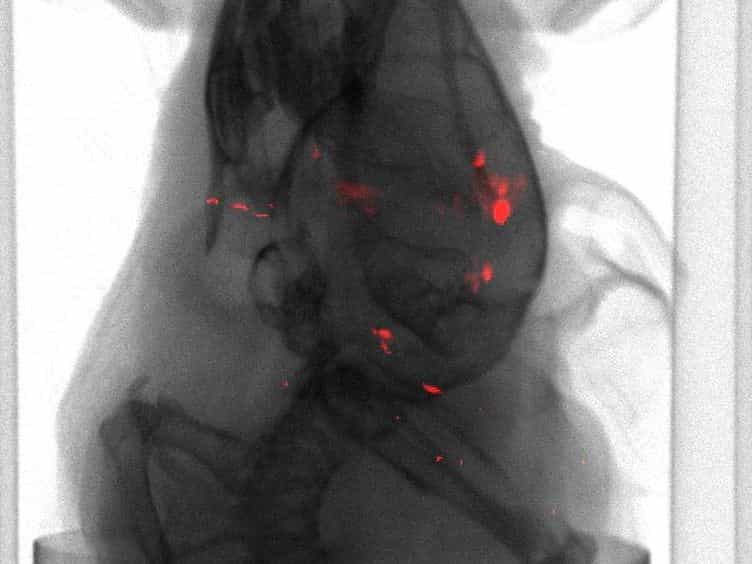

In Vivo Optical Imaging of Brain Tumors and Arthritis Using Fluorescent SapC-DOPS Nanovesicles
Published on: May 2, 2014
Intraarticular Glucocorticoid Injection as Second-line Treatment for Lyme Arthritis in Children
Daniel B Horton1,2, Alysha J Taxter3,4, Amy L Davidow3,4
1From the Division of Pediatric Rheumatology, Rutgers Robert Wood Johnson Medical School, New Brunswick; Rutgers Center for Pharmacoepidemiology and Treatment Science, Institute for Health, Health Care Policy and Aging Research, New Brunswick; Rutgers School of Public Health, Piscataway; Rutgers School of Public Health, Newark, New Jersey; Brenner Children's Hospital, Wake Forest Baptist Medical Center, Winston-Salem, North Carolina; Penn State Milton S. Hershey Medical Center, Hershey; Children's Hospital of Philadelphia, Division of Pediatric Rheumatology, Perelman School of Medicine, University of Pennsylvania, Philadelphia, Pennsylvania; Division of Rheumatology, Nemours/A.I. duPont Hospital for Children, Thomas Jefferson University, Wilmington, Delaware, USA. daniel.horton@rutgers.edu.

Objective:
To determine whether second-line intraarticular glucocorticoid (IAGC) injection improves outcomes in children with persistently active Lyme arthritis after initial antibiotics.
Methods:
We conducted an observational comparative effectiveness study through chart review within 3 pediatric rheumatology centers with distinct clinical approaches to second-line treatment of Lyme arthritis. We primarily compared children receiving second-line IAGC to children receiving a second course of antibiotics alone. We evaluated the risk of developing antibiotic-refractory Lyme arthritis (ARLA) using logistic regression and the time to clinical resolution of Lyme arthritis using Cox regression.
Results:
Of 112 children with persistently active Lyme arthritis after first-line antibiotics, 18 children received second-line IAGC (13 with concomitant oral antibiotics). Compared to children receiving second-line oral antibiotics alone, children treated with IAGC had similar baseline characteristics but lower rates of ARLA (17% vs 44%; OR 0.3, 95% CI 0.1-0.95; p = 0.04) and faster rates of clinical resolution (HR 2.2, 95% CI 1.2-3.9; p = 0.01). Children in IAGC and oral antibiotic cohorts did not differ in treatment-associated adverse events. Among children receiving second-line IAGC, outcomes appeared similar irrespective of use of concomitant antibiotics. Outcomes were also similar between intravenous (IV) and oral antibiotic-treated cohorts, but older children seemed to respond more favorably to IV therapy. IV antibiotics were also associated with higher rates of toxicity.
Conclusion:
IAGC injection appears to be an effective and safe second-line strategy for persistent Lyme arthritis in children, associated with rapid clinical resolution and reduced need for additional treatment.

Related Concept Videos
 01:21
Drugs for Treatment of Crohn's Disease in IBD Using Glucocorticoids
 01:25
Antiasthma Drugs: Inhaled Corticosteroids and Glucocorticoids
ICS work through a multifaceted mechanism of action. They suppress the inflammatory response caused by the proliferation of TH cells. They also reduce the transcription of the IL-2 gene, which is involved in the...
 01:29
Drug Dosing: Infants and Children
 01:24
Parkinson's Disease: Treatment
Parkinson's Disease is primarily a result of the loss of dopaminergic neurons in the substantia nigra pars compacta. The cornerstone of...
 01:22
Alzheimer's Disease: Treatment
 01:27
Open Angle Glaucoma: Treatment
Drugs such as carbonic anhydrase inhibitors, α2- and...