Related Experiment Video
Updated: Jan 28, 2026


Myocardial Infarction and Functional Outcome Assessment in Pigs
Published on: April 25, 2014
Procedural and Clinical Outcomes in Management of Bifurcational Lesions in ST Elevation Myocardial Infarction
Vimalraj Bogana Shanmugam1, Peter J Psaltis1, Leslie Tay1
1Monash Heart, Monash Medical Centre, Melbourne, Vic, Australia.

Insights
Bifurcation percutaneous coronary intervention (PCI) during ST-elevation myocardial infarction (STEMI) shows good acute results. However, it leads to higher rates of target lesion revascularization, stent thrombosis, and mortality within 12 months.
Area of Science:
- Interventional Cardiology
- Cardiovascular Research
- Medical Device Technology
Background:
- Bifurcation percutaneous coronary intervention (PCI) is a complex procedure in interventional cardiology.
- ST-elevation myocardial infarction (STEMI) presents unique challenges for bifurcation PCI.
- This study evaluates the outcomes of bifurcation PCI in STEMI patients.
Purpose of the Study:
- To compare procedural and 12-month clinical outcomes of bifurcation PCI versus non-bifurcation PCI in STEMI patients.
- To identify potential risks and benefits associated with bifurcation PCI in the acute STEMI setting.
Main Methods:
- Retrospective case-control study of 129 STEMI patients undergoing bifurcation PCI and 129 matched controls.
- Exclusion criteria included cardiac arrest, cardiogenic shock, or mechanical ventilation.
- 12-month follow-up data collected via phone calls and medical records.
Main Results:
- No significant differences in procedural failure (TIMI 0 flow) between groups (1.5% vs. 0%).
- Bifurcation PCI group showed higher 12-month incidence of target lesion revascularization (TLR) (10.9% vs. 3.9%).
- Increased 12-month mortality (10.1% vs. 2.3%) and stent thrombosis (9.3% vs. 1.6%) in the bifurcation PCI group.
Conclusions:
- Bifurcation PCI in acute STEMI demonstrates favorable acute procedural success.
- However, bifurcation PCI is associated with significantly higher rates of TLR, stent thrombosis, and mortality at 12 months.
- These findings highlight the need for careful consideration and potentially optimized strategies for bifurcation PCI in STEMI.
Background:
Bifurcation percutaneous coronary intervention (PCI) remains a challenging frontier in interventional cardiology, especially in the setting of ST-elevation myocardial infarction (STEMI). We examined the procedural and clinical outcomes of this patient subset.
Methods:
We conducted a retrospective case-control study. Between February 2006 and March 2011, 129 patients with STEMI underwent bifurcation PCI at our institution. One hundred and twenty-nine (129) control STEMI patients with non-bifurcation PCI were selected from the institutional database, matched for age, gender, culprit vessel, and lesion location. Patients with cardiac arrest, cardiogenic shock, or who required mechanical ventilation were excluded. Twelve (12)-month follow-up data were collected by telephone calls and examination of the medical records.
Results:
The average age of patients presenting with STEMI was 61.6 ± 13.1 in the bifurcation group and 61.5 + 31.1 in the non-bifurcation group. There was no difference in lesion type, use of thrombus aspiration catheters, or glycoprotein inhibitors (GPI) among them. Also, the use of drug eluting stent (DES), total cumulative length of stent used, and diameter of the post-dilation balloon were similar. Final kissing balloon post-dilation was performed in 40.3% of bifurcation PCI cases. The incidence of procedural failure (TIMI 0 flow) was 1.5% vs. 0%; p = 0.478. At 12-months follow-up, the bifurcation PCI group had higher incidence of target lesion revascularisation (TLR) (10.9% vs. 3.9%, p = 0.050), mortality (10.1% vs. 2.3%, p = 0.020), and stent thrombosis (9.3% vs. 1.6%; p = 0.013); comprising one acute, nine subacute, and two late vs. two subacute stent thromboses.
Conclusions:
During acute STEMI, bifurcation PCI has excellent acute procedural outcomes, but significantly increased incidence of TLR, stent thrombosis and mortality at 12 months.


Related Concept Videos
 03:12
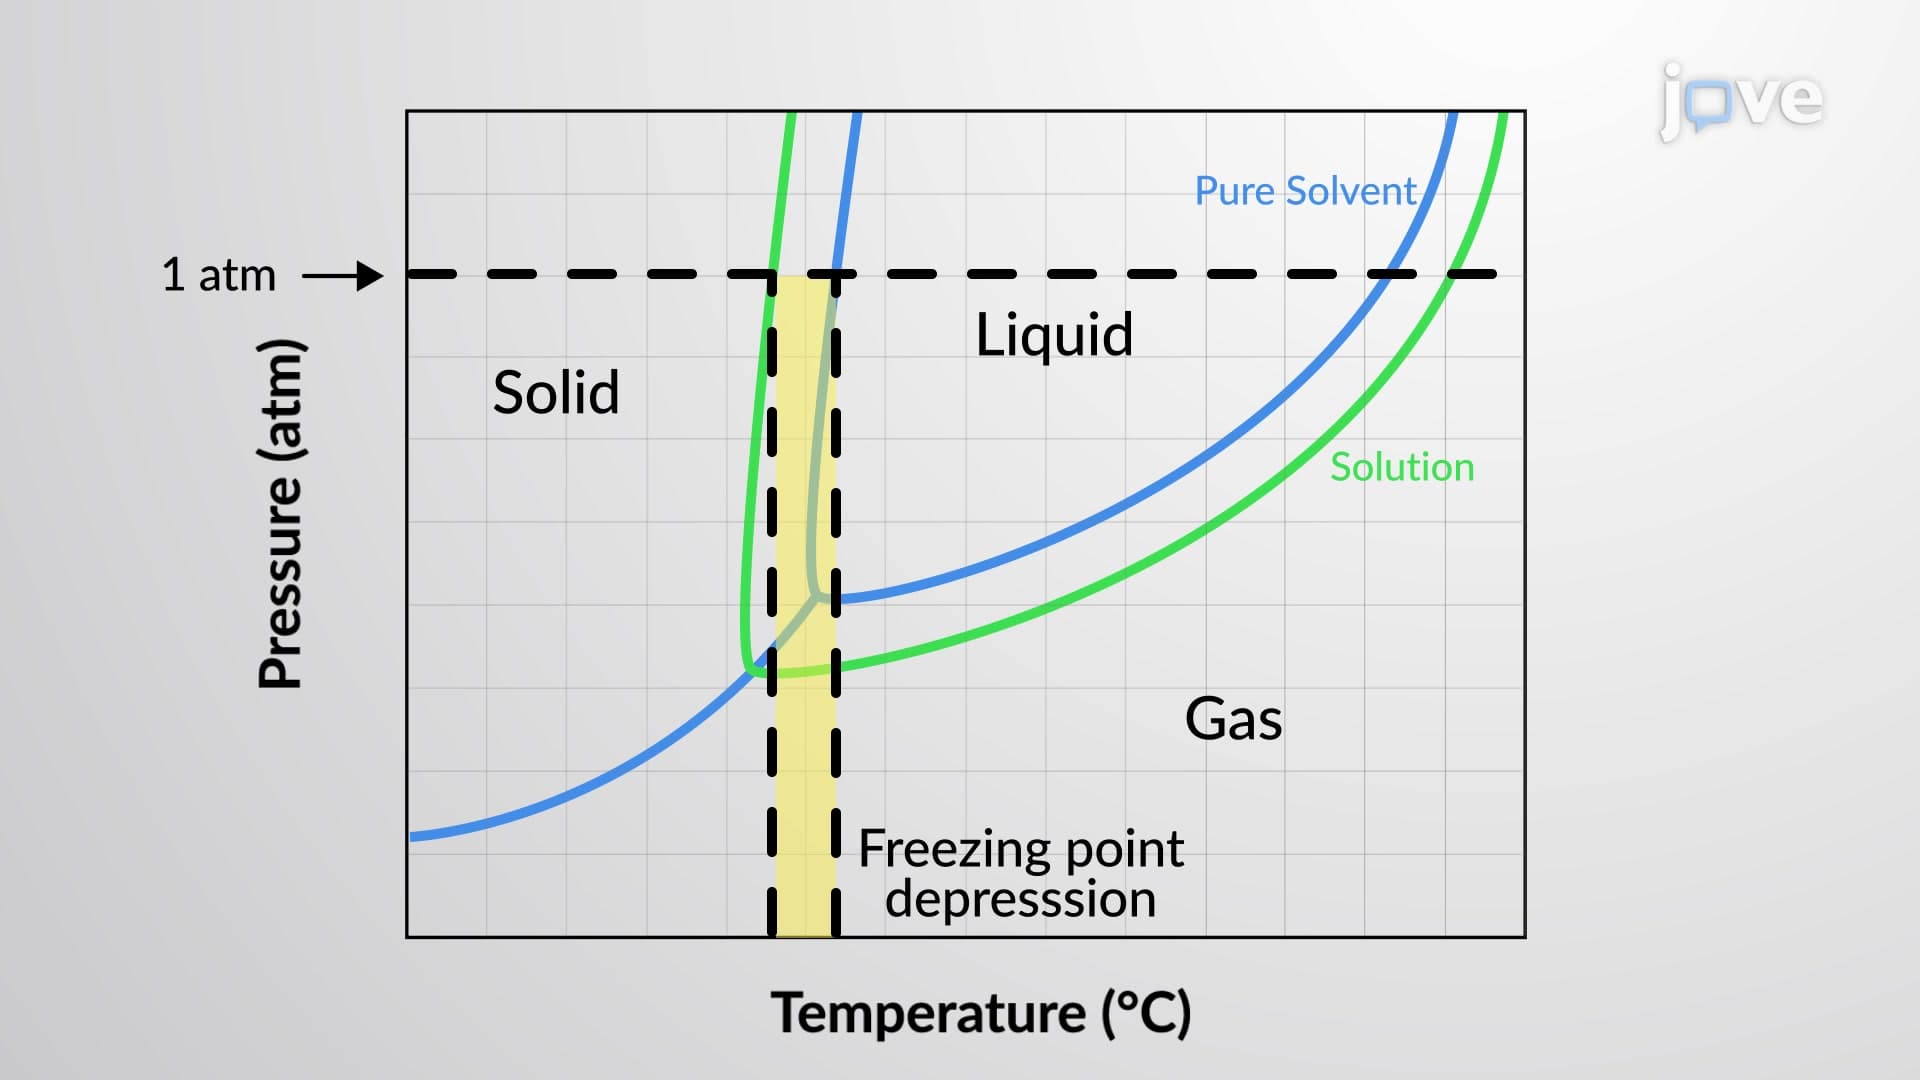
Freezing Point Depression and Boiling Point Elevation
The boiling point of a liquid is the temperature at which its vapor pressure is equal to ambient atmospheric pressure. Since the vapor pressure of a solution is lowered due to the presence of nonvolatile solutes, it stands to reason that the solution’s boiling point will subsequently be increased. Vapor pressure increases with temperature, and so a solution will require a higher temperature than will pure solvent to achieve any given vapor pressure, including one...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...